

Review Article | DOI: https://doi.org/10.31579/2641-0419/578
1Department of Cardiology, Mody Harvard Cardiac Institute & Research Centre- Krishna Super Specialty Hospital, Bathinda, Punjab, India.
2Department of Orthopaedics, Krishna Super Specialty Hospital, Bathinda, Punjab, India; 3Department of Cardiology, Aster Hospital, Mankhool, Dubai, Al Quasis, UAE.
4Department of Internal Medicine, Resident Doctor, Trinity Health Hospital, 36475 Five Mile Rd, Livonia, Michigan, 48335, USA.
5Department of Cardiology, Mody Harvard Cardiac Institute & Research Centre- Krishna Super Specialty Hospital, Bathinda, Punjab, India
6Department of Cardiology, Spectrum Medical Center and Burjeel Royal Hospital, Al Ain, UAE.
*Corresponding Author: Rohit Mody, Department of Cardiology, Mody Harvard Cardiac Institute & Research Centre- Krishna Super Specialty Hospital, Bathinda, Punjab, India.
Citation: Rohit Mody, Harpreet Singh, Debabrata Dash, Bhavya Mody, Umanshi Dash, et al, (2026), Young-Onset Coronary Artery Disease: Clinical Insights, Epidemiology, And Evolving Management Strategies, J Clinical Cardiology and Cardiovascular Interventions, 9(8); DOI:10.31579/2641-0419/578
Copyright: © 2026, Rohit Mody. This is an open-access article distributed under the terms of the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original author and source are credited.
Received: 13 April 2026 | Accepted: 30 April 2026 | Published: 05 June 2026
Keywords: coronary artery disease; myocardial infarction; acute coronary syndrome; heart failure
Despite remarkable advancements in cardiovascular medicine, coronary heart disease (CHD) continues to exert a devastating global impact. Atherosclerotic Coronary Artery Disease (ACAD) often begins silently at a young age and progresses unnoticed until manifesting as acute events- myocardial infarction (MI) or sudden cardiac death (SCD). Traditional ischemia-centric approaches to CHD diagnosis and management intervene too late. Therefore, a paradigm shift is urgently needed- reframing CHD as ACAD, a lifelong, progressive condition. SCD remains a major concern in this population. Early identification through advanced imaging modalities (invasive and non-invasive) and novel biomarkers is key to implementing timely, personalized interventions. This review emphasizes the need for global health systems to adopt prevention-focused, equity-driven strategies and calls for increased research investment in early-stage atherosclerosis, especially in diverse and underserved populations. We explore the epidemiology, pathophysiology, risk factors diagnostic advancements, and preventive treatments and management strategies aimed at reducing CHD burden among young adults.
Cardiovascular disease (CVD) in young adults is an emerging public health concern, comprising both congenital and acquired conditions. The incidence has risen globally, particularly in Asian populations. Coronary artery disease (CAD), a major subset of CVD, now contributes significantly to morbidity and economic burden in younger individuals, often presenting with severe outcomes [1]. Histological evidence shows subclinical atheromatous plaques developing early in life, indicating that atherosclerosis begins much earlier than previously thought [2].
In 2022, there were an estimated 315 million global CAD cases, with a prevalence of 3,605 (2,892–4,454) per 100,000. Among young individuals, CAD accounts for 1-16% of cases, with acute coronary syndrome (ACS) being the predominant presentation [3]. Urbanization influences CAD rates, with urban prevalence ranging from 6.5% to 13.2%, versus 1.6% to 7.4% in rural areas. Non-atherosclerotic causes, including autoimmune and connective tissue disorders, account for nearly 20% of cases.
Modifiable risk factors such as smoking, hypertension, dyslipidemia, and obesity, alongside genetic predisposition, play central roles [4]. Advances in imaging- coronary computed tomography angiography (CCTA), cardiovascular magnetic resonance, single-photon emission computed tomography— now allow early detection of subclinical CAD. This review discusses epidemiology, risk factors, and evolving diagnostic tools in young-onset CAD to support proactive, personalized care.
Key points:
Epidemiology Of Coronary Heart Disease (Chd)
Defining “young” patients varies across studies, typically ranging from 35 to 55 years. For this review, young adults are considered those under 40 years of age [6]. Although CAD is more prevalent in individuals over 40, approximately 3% of cases occur in patients younger than 40. This may be an underestimate, as asymptomatic young adults rarely undergo diagnostic evaluation.
CVDs have become leading causes of global mortality [7] and disability-adjusted life years (DALYs), accounting for 7 million deaths and 129 million DALYs annually in LMIC. In 2015, CAD contributed to 164 million DALYs and 8.9 million deaths worldwide [8]. Regions like Latin America and the Middle East have seen sharp increases in cardiac events, primarily due to lifestyle-related risk factors like smoking and obesity.
In India, CVD often manifests a decade earlier than in Western populations, affecting individuals during their most productive years. Notably, 52% of CVD deaths in Indians occur before age 70, compared to 23% in Western countries [9]. This disparity is attributed to both social and biological determinants.
South Asia—especially India, Pakistan, Bangladesh, Sri Lanka, and Nepal—bears a disproportionate CVD burden. Even in the absence of classic risk factors, South Asian migrants experience higher CHD mortality at younger ages.
Meanwhile, high-income nations have witnessed a decline in CVD mortality due to improved acute care and preventive strategies. Major contributors to early CAD include smoking, dyslipidemia, obesity, dysglycemia, and family history. Early identification and intervention are critical to reducing the burden in young adults.
Pathogenesis And Risk Factors of Cad in Young Adults
Although traditionally viewed as a disease of older adults, CAD is increasingly seen in younger populations, with significant clinical and socioeconomic implications. ACAD, the primary mechanism underlying CAD, begins early in life and progresses silently over decades [10]. This slow progression, paired with the rising prevalence of risk factors like obesity, smoking, diabetes, and dyslipidemia, highlights the urgent need to understand early atherogenesis.
1. Pathogenesis of Early CAD: From Endothelial Dysfunction to Plaque Rupture
The process starts with endothelial dysfunction, impairing vasodilation and promoting leukocyte migration into the sub-endothelial space. Monocytes differentiate into macrophages and engulf oxidized low-density lipoprotein (LDL), forming foam cells— early markers of fatty streaks. Persistent risk factor exposure leads to fibrous plaque development with a necrotic lipid core and fibromuscular cap. Inflammatory cytokines and proteolytic enzymes destabilize plaques, predisposing them to rupture. Plaque rupture or erosion exposes thrombogenic material, triggering thrombus formation and acute coronary events— often the first presentation of CAD in young adults [11].
2. Histopathological Evidence of Early Atherosclerosis
Autopsy and electron microscopy studies in young individuals show fatty streaks, foam cells, extracellular lipid, and early fibrous caps in coronary arteries [12]. These features closely resemble early-stage plaques in symptomatic adults and are more common in individuals with modifiable risk factors. Such findings stress the need for early risk assessment and preventive interventions to halt disease progression before clinical onset.
• Development of ACAD occur through multiple steps:
• Expression of adhesion molecules, increased permeability and impaired vasodilation attract leukocytes and initiate formation of plaque [13].
• Inflammation, recruitment of macrophages and development of foam cells is triggered by the retention of ApoB-containing lipoproteins (LDL, VLDL) in the vessel wall [14].
• Oxidized LDL forming foam cells are engulfed by macrophages → cell death → necrotic debris → amplification of inflammation within plaques.
• Extracellular matrix (collagen, proteoglycans), is produced by migration of vascular smooth muscle cells which further produce the fibrous cap over the lipid-rich necrotic core.
• Various factors such as huge concentration of inflammatory cells (specifically at plaque region), large lipid core potentiate the risk of thrombus and plaque rupture [15].
• Positive remodeling (vessel expansion) can preserve lumen despite plaque growth, delaying identification but modulating risk.
• Traditional risk factors: hypertension, smoking, obesity, dyslipidemia.
• Emerging risk factors: Pregnancy hypertensive disorders, air pollution, sleep problems, changes in gut microbiome, social determinants, stress.
• Rupturing of plaque can occur irrespective of severity; even acute event may be triggered by mild lesions; symptoms do not always associate with disease severity.
• Clinical focus must be provided to early assessment of lipid deposition, inflammation and endothelial-wall dysfunctioning instead of treatment of late-stage ischemia-enabling regression, prevention and potential treatment of ACAD in early stage.
Risk Factors Of ACAD
Atherosclerosis begins early, even in childhood, highlighting the need for timely prevention. ACAD arises from metabolic (hypertension, diabetes), behavioral (smoking, diet), genetic (family history), and environmental (pollution, stress) factors. Novel risks include microbiome imbalance, sleep disorders, and hypertensive pregnancy complications. Age-related cellular senescence increases vulnerability [16].
By 2070, ≥65-year-olds will outnumber children globally, emphasizing preventive needs in aging societies [16]. Although ACAD manifests later in females, risk rises post-menopause due to estrogen decline; testosterone extremes raise risk in males [17,18]. Female-specific factors include gestational diabetes, PCOS, and pregnancy hypertension [17].
Family history, including polygenic and monogenic patterns, raises risk. Ethnic and regional genetic variations necessitate inclusive risk tools [19]. Rising hypertension rates in youth (e.g., 32% in Zimbabwe, age 18–24) reflect urgent needs in LMICs. Major atherosclerotic and non-atherosclerotic risk factors responsible for CAD in young adults are summarized in table 1.
| Atherosclerotic Risk Factors | Non-Atherosclerotic Risk Factors |
| Family history of premature CHD. | Congenital coronary artery anomalies. |
| Dyslipidemia (elevated LDL, reduced HDL, hypertriglyceridemia). | Myocardial bridging. |
| Obesity and central adiposity. | Connective tissue disorders (e.g., Marfan syndrome, Takayasu’s arteritis, giant cell arteritis). |
| Hypertension. | SCAD, especially in pregnancy. |
| Type-2 diabetes mellitus or insulin resistance. | Drug abuse (cocaine, amphetamines). |
| Cigarette smoking/tobacco use. | Use of oral contraceptives. |
| Sedentary lifestyle/lack of physical activity. | Inflammatory or autoimmune diseases (e.g., lupus, vasculitis). |
| Psychosocial stress/depression. | Coagulation disorders (e.g., antiphospholipid syndrome, Factor V Leiden mutation). |
| Metabolic syndrome. | Infectious agents (e.g., Mycoplasma pneumoniae, Helicobacter pylori, HIV). |
| Male sex. | Radiation-induced coronary injury (post-chemotherapy/radiotherapy). |
Table 1: Invasive and Non-Invasive Risk Factors Responsible for CAD in Young Adults [19-23].
†CHD: Coronary Heart Disease; CAD: Coronary Artery Disease; LDL: Low-Density Lipoprotein; HDL: High-Density Lipoprotein; SCAD: Spontaneous Coronary Artery Dissection; HIV: Human Immunodeficiency Virus.
Key Modifiable Risk Factors
NOVEL RISK FACTORS FOR ACAD
1.Inflammation
2.Hyperhomocysteinaemia
3.Gut Microbiome
4.Physical inactivity
5.Diet
6. Stress & Psychosocial Factors
7.Sleep Disorders & Obstructive Sleep Apnea (OSA)
8. Cancer Survivors
9.Emerging risk factors
10.Opportunity for Integrated Prevention
Diagnosis Of Atherosclerosis By Non-Invasive Imaging Methods
It is clear that in patients present with autoimmune or coagulation disorders, as well as with cocaine consumers and cigarette smokers are at very high risk of developing CHD as young adults. Subclinical disease assessment in such patients could provide insights about early therapeutic intervention to prevent the risk of acute coronary events [30].
Incorporation of various traditional CHD risk factors is carried out in various population-based screening algorithms, which are quite helpful in the prediction of adverse cardiovascular event risk even in young adults [31]. However, the absence of arteriosclerosis is not guaranteed by the absence of these conventional risk factors, and several adverse cardiovascular events are reported in patients who are at their LDL cholesterol goals [32]. Considering this, study of various additional cerebrovascular screening biomarkers is carried out to assess for their residual risk.
From various years, diagnosis and risk stratification in CHD patients have been carried out by various exercise stress testing modalities, including stress echocardiography and stress electrocardiography [33]. However, findings of the various studies in young adults demonstrated that stress assessment generates a huge number of false-negative results, due to which its clinical use is specifically limited in screening young asymptomatic populations [34].
Further, for the early assessment of asymptomatic SCA in patients, various non-invasive imaging modalities like computed tomography angiography (CTA) computed tomography coronary artery calcium (CAC), and CCTA have extensively been studied [35]. These methods facilitate vital diagnostic insights into ACS, cardiovascular outcomes, ischemia and risk stratification in CAD. Progression of atherosclerotic lesions may occur from non-atherosclerotic intimal lesions to high-risk, thin cap fibroatheromas (TCFA) susceptible to rupture or vulnerable plaques. CCTA play quite significant role in the assessment of these plaques and the overall coronary artery state. CCTA used for combined illustration of SCA by groups is demonstrated in figure 1.
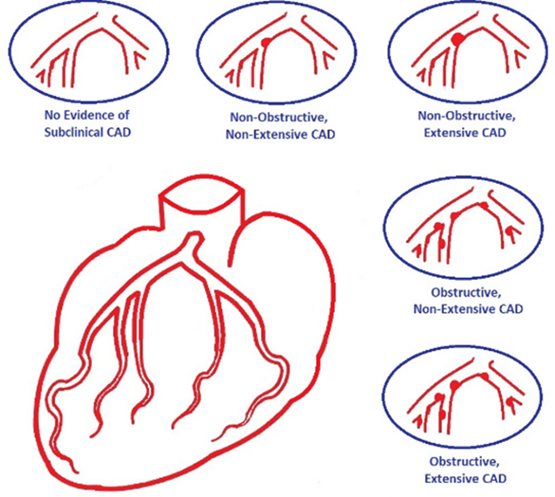
Figure 1: CCTA used for illustration of combined subclinical coronary atherosclerosis by groups. Major two categories were Obstructive (<50>50% stenosis) in which classification of coronary luminal diameter stenosis was done. Patients were categorized as absence of atherosclerosis, non-obstructive stenosis, obstructive extensive, and non-obstructive non-extensive.
†CCTA: Coronary Computed Tomography Angiography.
A strong association exists between CAC and atherosclerotic plaque burden. Findings of the CARDIA study suggested that elevated levels of CAC lead to a marked rise in the risk of CVD and CHD events, even a minimal rise in CAC increases the risk [36]. However, only non-calcified plaques have been observed in a huge proportion of young patients present with CHD, CAC may under-diagnose CHD in young adults to a great extent in comparison to older individuals.
Carotid plaque burden and Carotid intima-media thickness (CIMT) are characterized as predictors of cardiovascular risk. Ultrasound assessment of CIMT is a well-developed biomarker to detect atherosclerotic load in CAD and cardiovascular therapeutic interventions effectiveness [37]. Findings of a recent study demonstrate the 75% specificity and 78% diagnostic sensitivity of CIMT however its precision increase if it is coupled with other inflammatory biomarkers like hs-CRP [38].
CCTA has evolved into a mature non-invasive imaging modality that facilitate precise imaging of coronary arteries, ensuring accurate assessment of obstructive CAD. It is also associated with the significant potential to assess components of atherosclerotic plaque and to detect high-risk plaque features. IVUS and CCTA used to demonstrate characteristics of coronary artery plaque is demonstrated in figure 2. CCTA derived imaging methods are demonstrated in figure 3.
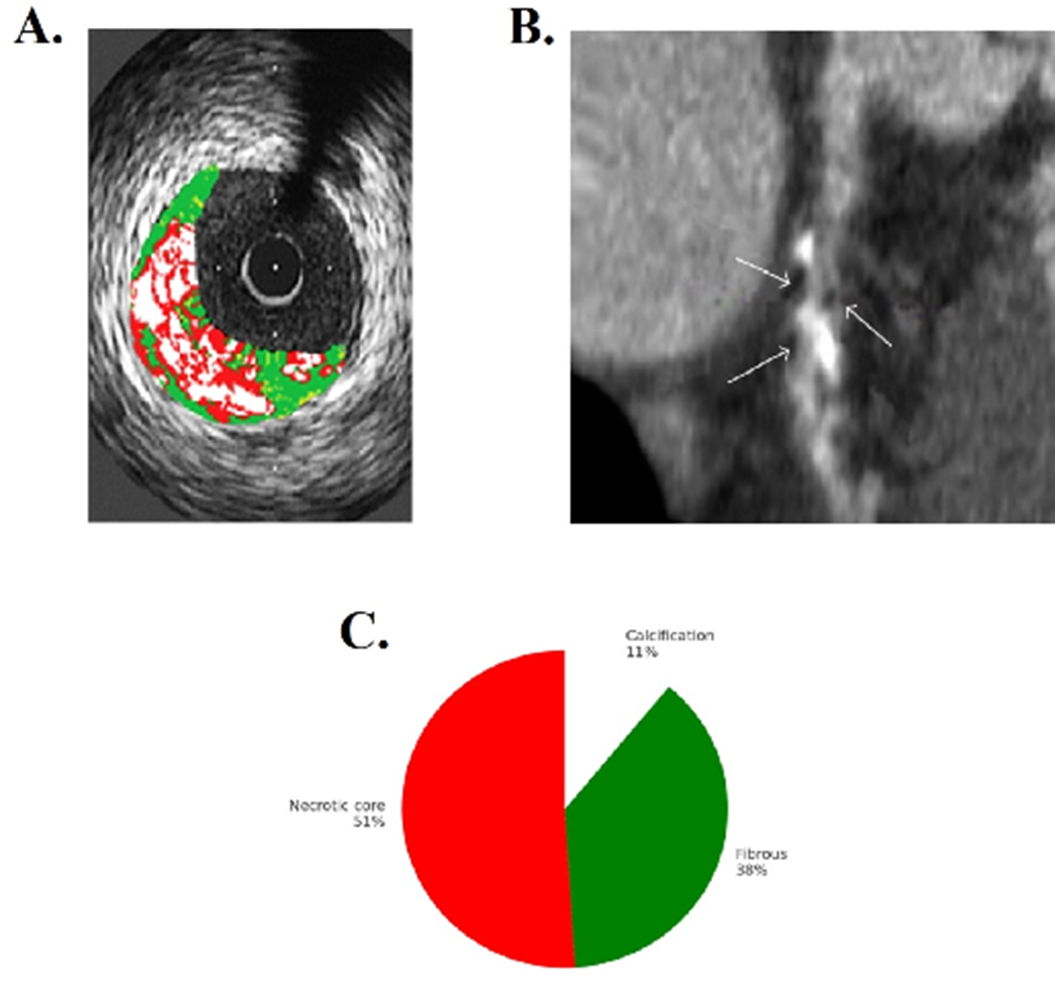
Figure 2: IVUS and CCTA utilized to investigate the features of coronary artery plaque. On CCTA, a high clinical risk of vulnerability was seen in various morphological features of coronary plaque, including (A) positive remodeling (B) low-attenuation plaque (C) spotty calcification.
†IVUS: Intravascular Ultrasound; CCTA: Coronary Computed Tomography Angiography.
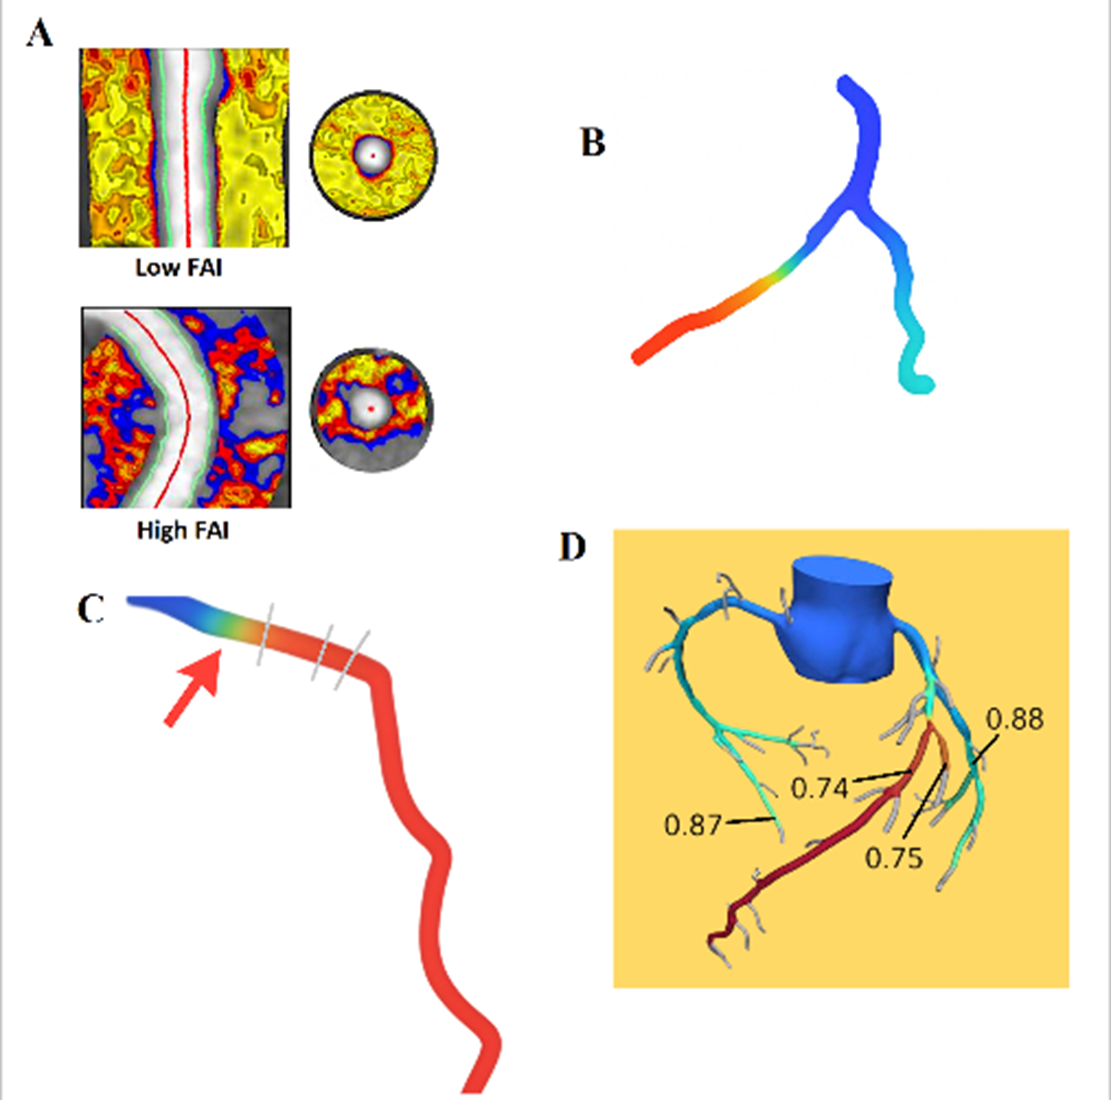
Figure 3: CCTA derived emerging technologies. (A) CCTA was utilized for investigation of two patients present with high and low perivascular fat attenuation index (B) Right and left coronary arteries three-dimensional view is demonstrated using vascuCAP (Elucid Bioimaging, Boston, Massachusetts, USA) from CCTA utilized for the plaque quantification and characterization. (C) Example of CCTA utilized for demonstration of superimposed profile of wall shear stress on a coronary artery tree (D) CCTA utilized for fractional flow reserve-computed tomography calculations extractions.
†CCTA: Coronary Computed Tomography Angiography.
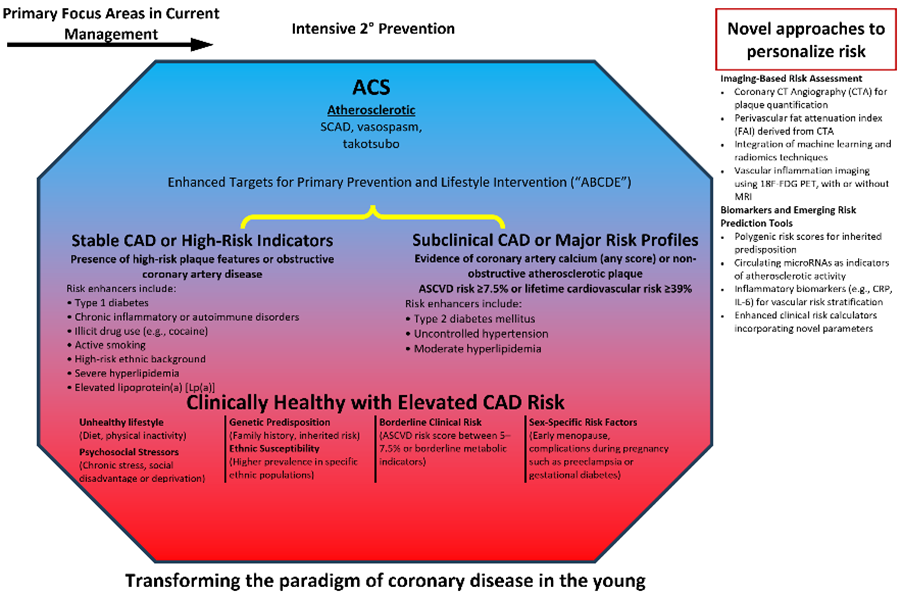
Figure 4: Multipronged approach utilized to break the coronary artery disease cycle in young adults. A multipronged strategy is needed to break the CAD cycle in young adults present at high risk of acute coronary syndrome. Patients screening for risk of conventional atherosclerotic cardiovascular disease should be carried out and patients should be managed by using “ABCDE” approach, Various novel biomarkers, various scoring methods can be utilized to assess the personalized risk assessment.
†ACS: acute coronary syndrome; SCAD: spontaneous coronary artery dissection; CAD: coronary artery disease; Lp(a): lipoprotein (a); ASCVD: atherosclerotic cardiovascular disease; CTA: computed tomography angiography; FDG: fluorodeoxyglucose; PET: positron emission tomography; MRI: magnetic resonance imaging.
Findings of a study conducted by Hoffmann et al [39] and Motoyama et al [40] suggested that distinct features including low-attenuation components (typically spotty calcification, napkin-ring sign and positive remodeling are observed in coronary plaques in patients present with the ACS.
A useful clinical insight about the development of CAD is provided by various proteins and biomarkers associated with inflammation, metabolic syndrome and oxidation. Combining these with conventional risk factors potentiates the accuracy of the prediction of CAD risk. The risk of CAD in young adults is highlighted by various emerging biomarkers like lipoprotein-associated phospholipase-A2 [41].
Polygenic risk score (PRS) quantitative metrics which has emerged as useful diagnostic tools for genetic risk stratification of CAD specifically for those with a familial history of CAD. The role of PRS in prediction of risk of CAD in young adults is emphasized by Khera et al [42]. Furthermore, deep clinical insights into the progression of atherosclerotic plaque and stable CAD is provided by quantitative plaque imaging. Quantification of CTA plaque, by CCTA, predicts the severity of coronary artery plaque, and assessment of traditional risk in the prediction of adverse cardiovascular events [43].
Fat attenuation index (FAI) is another novel imaging metrics, which was validated against 18-F fluorodeoxyglucose (FDG) positron emission tomography (PET) imaging. CT attenuation of perivascular tissues around the arterial wall and pericoronary inflammation in CAD patients is quantified by FAI. Magnetic Resonance Imaging (MRI) has emerged as an ideal imaging technique for the repeated assessment of the progression of atherosclerotic plaque. MRI not only provides accurate detection of plaque thickness and size but it also facilitates differentiation between vessel wall and vessel lumen [44].
Coronary microvascular dysfunction, an advanced imaging biomarker, facilitates the microvascular impairment early assessment, a key factor in understanding the pathological mechanism of CAD behind the epicardial coronary arteries. A quite significant role is played by MV in the development of CAD and its assessment through various non-invasive imaging methods provide useful information for the identification of patients who are at huge risk for adverse cardiovascular outcomes.
Personalized risk profiling, which includes assessment of advanced risk tools and genetic testing, has gained significant importance in an era of precision medicine in the management of CAD. Understanding genetic variants that potentiate the risk of CAD facilitates tailored therapeutic options that cater to the needs of individual patients. Moreover, various risk prediction methods that integrate lifestyle, genetic and clinical factors have played a potential role in the identification of patients present with a huge risk of CAD, thereby facilitating the implementation of timely preventive and therapeutics strategies.
In recent era, developments in artificial intelligence (AI) and (ML) technologies not only improve diagnostic accuracy but also provide useful diagnostic insights that are difficult to predict. Deep learning system are utilized in ML which are associated with the strong potential to accurately detect plaque stenosis and severity from CCTA scans. 5-year Machine learning all-cause mortality was detected better with CCTA data and ML combining data in comparison to existing clinical or CCTA metrics alone [45]. Emerging imaging modalities and biomarker-based tools that may personalize risk prediction in young individuals are summarized in table 2.
| Advanced Imaging Modalities | Novel Biomarkers / Risk Prediction Tools |
| CCTA with plaque morphology analysis. | HS-CRP. |
| CTA-based perivascular FAI. | PRS. |
| CAC scoring. | MicroRNAs (e.g., miR-126, miR-155). |
| Machine learning-based radiomics and predictive modeling. | Circulating inflammatory cytokines (e.g., IL-6, TNF-alpha). |
| 18F-FDG PET/CT or PET/MRI for vascular inflammation imaging. | Genetic markers for familial hypercholesterolemia. |
| IVUS and OCT. | Lipoprotein(a) levels. |
| MRI-based plaque characterization. | Advanced clinical risk calculators integrating lifestyle and genomic data. |
| AI-enabled multimodal risk scoring platforms. | Epigenetic markers (e.g., DNA methylation signatures). |
Table 2: Emerging Imaging and Biomarker-Based Strategies to Personalize Risk Prediction in Young Individuals [36, 37, 39, 40, 42, 45].
†CCTA: Coronary Computed Tomography Angiography; HS-CRP: High-Sensitivity C-Reactive Protein; FAI: Fat Attenuation Index; PRS: Polygenic Risk Score; CAC: Coronary Artery Calcium; FDG: Fluorodeoxyglucose; PET: Positron Emission Tomography; IVUS: Intravascular Ultrasound; OCT: Optical Coherence Tomography; MRI: Magnetic Resonance Imaging; AI: Artificial Intelligence.
Instead of these recent advancements, challenges are still associated with promoting the adoption of these imaging modalities. The requirement of operating expertise, associated costs and access to advanced imaging methods, are certain issues that must be addressed. Further studies assessing the clinical application of these imaging techniques, and cost-effectiveness in the routine management of CAD is the need of hour.
I. Primary Prevention and Risk Prediction in ACAD
Primary prevention aims to halt disease before clinical onset, particularly in high-risk but asymptomatic individuals. Despite strong evidence supporting interventions like smoking cessation, BP/glucose/lipid control, and statins (effective at ≥2.5-year risk) [49][52], real-world implementation remains suboptimal.
II. Secondary Prevention Strategies IN ACAD
Secondary prevention reduces recurrence of MI, stroke, and mortality in patients with established ACAD [50]. Future care models may shift to view ACS as preventable “never events.”
1.Revascularization in Stable ACAD: Prognostic Benefit Debated
2.Revascularization in ACS: Undisputed Role
3.PCI vs CABG: Context-Specific Choices
4.Future Research Gaps in Revascularization
1.Post-PCI Angina: Unmet Need for Research
2.Limitations of Current Symptom Assessment Tools
3. Alternative Devices and Therapies for Angina
4.New Technologies in PCI
Must balance innovation with clinical evidence of cost-effectiveness and durable clinical benefit.
5.Future Focus of ACAD revascularization Strategy
Greater focus should be provided to lifestyle therapeutic interventions, pharmacotherapy and prevention to reduce the revascularization need.
I. Future Directions In Acad Management
The evolving understanding of ACAD highlights the need to move beyond traditional ischemia-based strategies. The focus now shifts to early detection, plaque biology, and system-level changes supported by precision medicine and technology integration.
1. Beyond Ischemia-Centric Models
Traditional revascularization for stable CAD offers limited prognostic benefit. Most acute coronary events stem from vulnerable, non-obstructive plaques missed by stress testing.
2. Imaging Plaque Burden and Risk
Advanced tools like CCTA, IVUS, OCT, and NIRS detect high-risk features (e.g., necrotic cores, thin-cap fibroatheroma). Trials like PROSPECT [5], CLIMA [63], and PROSPECT II [64] support imaging-guided risk stratification. A hybrid model integrating imaging, genetics, and biomarkers is likely the future.
3. Precision Therapeutics
Next-gen care includes PRS, pharmacogenetics (e.g., SLCO1B1, CYP2C19), and endotyping. Emerging therapies—colchicine, IL-1β inhibitors, RNA-based lipid-lowering agents, PCSK9 vaccines—and regenerative options like CRISPR and stem cell therapy [65] show promise.
4. AI and Digital Health
AI enables risk prediction, plaque assessment, and remote monitoring. Digital tools and wearables improve adherence and surveillance, especially in underserved regions. Rigorous validation across populations remains essential.
5. Implementation Science
Despite available therapies, adherence and access remain poor. Implementation strategies include polypills, long-acting drugs, behavioral nudges, and digital interventions.
6. Inclusive Research
Underrepresentation of women, elderly, LMIC populations limits generalizability. Future trials must be pragmatic, diverse, and enriched by surrogate endpoints like inflammation and plaque regression.
7. Cost-Effective and Scalable Solutions
New therapies must prove value with substantial risk reduction and cost-effectiveness. Basic interventions like BP control, statins, and smoking cessation remain vital in low-resource settings.
8. Toward ACAD Eradication
The ultimate goal is not control but eradication. This requires:
Future Research
1.Future ACAD Research Must Be Interdisciplinary
2.ACAD is Largely Preventable and Acquired
3.Move Beyond Primary & Secondary Prevention to Primordial Prevention
4.Genomics and Epigenetics to Revolutionize ACAD Prevention
5.Prenatal and Early Life Exposures Are Critical
6.Early Life Risk Factor Control Needed
7.Health Behaviours Must Be Targeted Early
8.Upstream Prevention Has Cumulative Lifelong Benefits
9.Implementation Science is Crucial
10.Public Health Policies and Hybrid Research Models Are the Future
1. Ischemia-Guided Strategy: Limitations
Revascularization doesn’t improve outcomes in stable CAD [69]. Vulnerable plaques evade detection via stress tests, and total atheroma burden better predicts events [70,71].
2. High-Risk Plaque Detection
CCTA, OCT, IVUS, and NIRS identify dangerous plaque characteristics. Validated by PROSPECT [5], CLIMA [72], and PROSPECT II [73], these methods support preemptive intervention. Various invasive and non-imaging methods to assess sub-clinical atherosclerosis in young adults is demonstrated in Central Illustration.
3. Limits of Plaque-Centric PCI
Local interventions ignore systemic disease. Imaging finds only 4–25% of high-risk plaques. Whole-vessel imaging is costly and impractical.
4. Future Therapeutics
Stabilization of vulnerable plaques via anti-inflammatories, PCSK9 inhibitors, and high-dose statins is under study [74].
5. Addressing Implementation Gaps
Therapy underuse remains a major challenge. Adherence, affordability, and equitable application of proven drugs must be prioritized.
6. Inequity in Access
LMICs lack infrastructure and access to guideline-based care. Global inequities limit the reach of emerging treatments.
7. Clinical Trial Inclusion
White males dominate trials, marginalizing women, elderly, and low-income populations [75]. Broader inclusion is essential.
8. Precision Therapy Approach
Future care will tailor treatment based on:
9. New Technologies
Wearables and AI tools will enhance early detection, monitor disease progression, and personalize therapy.
Research And Implementation Strategies
1.Early-Stage Focus: Shift from late-stage treatment to early prevention.
2.Long-Term Studies: Needed in young adults (18–39), with emphasis on diversity and protocol adherence.
3.Standardized Data: Global registries (e.g., Scandinavian models) will support comparative analysis [75].
4.Imaging & Biomarker Trials: Serial imaging, inflammation markers, and guided interventions.
5.New Endpoints: Beyond death and MI—include adherence, safety, and surrogate markers.
6.Improving Adherence: Leverage digital tools, depot drugs, polypills, and behavioral approaches [76].
7.Inclusive Participation: Focus on women, disadvantaged, and biomarker-enriched populations.
8.Locally Relevant Research: Align studies with regional needs and healthcare realities.
9.Safety Monitoring: Long-term data systems for adverse event tracking in new therapies.
10.Policy Integration: Embed research into health policy via coordination among governments, global health bodies, and academia
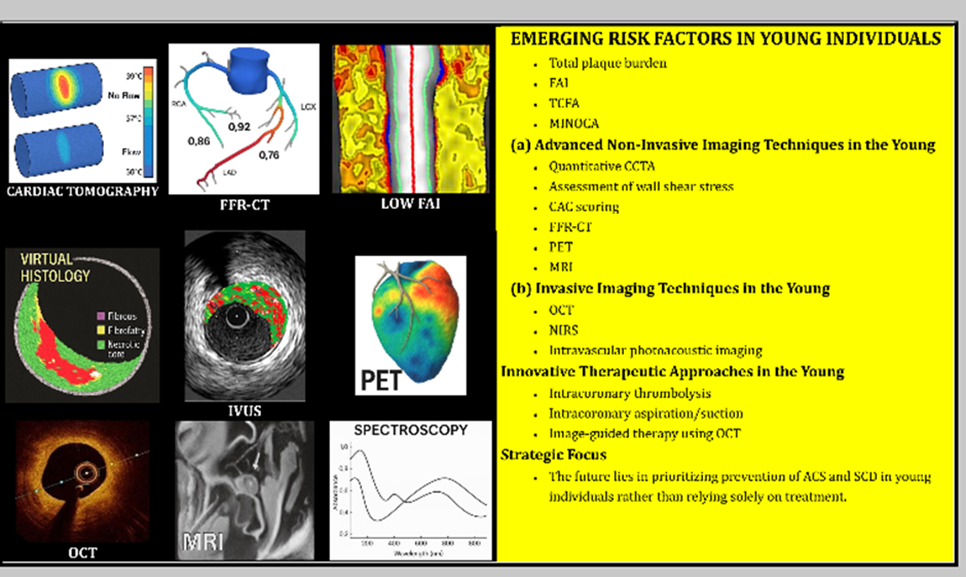
Central Illustration: Various non-invasive and invasive imaging modalities to investigate sub-clinical atherosclerosis in young patients present with coronary artery disease.
†FFR-CT: fractional flow reserve-computed tomography; FAI: Fat-Attenuation Index; TCFA: Thin-Cap Fibroatheroma; IVUS: intravascular ultrasound; PET: Positron Emission Tomography; OCT: optical coherence tomography; MRI: Magnetic Resonance Imaging; MINOCA: Myocardial Infarction with Non-Obstructive Coronary Arteries; NIRS: Near-Infrared Spectroscopy; CCTA: Coronary Computed Tomography Angiography; CAC: Coronary Artery Calcium; FFR-CT: Fraction Flow Reserve-Computed Tomography; ACS: Acute Coronary Syndrome; SCD: Sudden Cardiac Death.
Future trials should be conducted to demonstrate the significance of novel risk factors, like FAI, TCFA, plaque burden and MINOCA clinical significance in the prevention of CAD. A potential role in understanding plaque features and tools to prevent or treat these plaques in young patients is played by various invasive methods, like OCT, NIRS and intravascular photoacoustic and CCTA derived characteristics, FFR-CT, PET and MRI. Role of intracoronary suction, intracoronary lytic agents or management with OCT facilitate assessment and management of plaque in performing primary PCI. Most significantly, the future lies in prevention of SCAD and ACS for young patients rather than management.
The lead author of the review article is Dr Rohit Mody. Dr Harpreet Singh, Dr Debabrata Dash, Dr Bhavya Mody, Dr Umanshi Dash and Dr Rajeev Gupta had equal and substantial contributions in the formation of this review article. They were involved in conceptualization, data curation, formal analysis, resources, software, validation, visualization, writing - original draft, Writing, review & editing.
I thank Mr. Rohit for assisting me to finalize the review article. Figures are edited by Mr. Jiwan Singh.
Availability Of Data And Materials
The datasets used and/or analyzed during the current study are available from the corresponding author on reasonable request.
Ethics Approval And Consent To Participate
Ethical approval was not required since it is an accepted procedure
Consent For Publication
Written consent has been obtained to publish the review article from the guardian. The consent copy is available with the authors and ready to be submitted if required.
Disclosures: All authors have nothing to disclose.
Funding: There is no funding or financial conflicts of interest to disclose.
Dear Editorial Team, Clinical Medical Reviews and Reports. My experience with the journal was highly positive. The peer-review process was rigorous, constructive, and completed in a timely manner. The reviewers provided valuable comments that helped improve the quality and clarity of our manuscript. The editorial office was professional, responsive, and supportive throughout all stages of the publication process. Communication was clear and efficient, and any questions were addressed promptly. Overall, I found the journal to maintain high scientific standards and an excellent publication workflow. I would be pleased to consider submitting future work to this journal. Best wishes from, Elena Popa.

It was my pleasure to submit my testimonial concerning the Reviewer Board of our Scientific Journal “Brain and Neurological Disorders”. The Reviewers focused on some modifications and their contribution was helpful. The ladies of our Editorial Office were also supported my efforts. It was my honor to have such a co-operation and I am looking forward for more collaboration.

Dear Grace Pierce, Editorial Coordinator of Journal of Clinical Research and Reports, Thank you for the speedy and efficient peer review process. I appreciate the fact that your peer reviewers do not take months to respond like with some other journals. I would also like to thank the editorial office for responding quickly to my questions. It is an excellent journal. I plan to submit more manuscripts in the future. Best wishes from, Robert W. McGee

Dear Grace Pierce, Editorial Coordinator of Journal of Clinical Research and Reports, Working with you and your team on our recent publication in JCRR has been a truly wonderful and enjoyable experience. The responses were prompt, and the reviewers were patient, constructive, and highly professional. One reviewer in particular gave me the feeling that a professor was carefully reading and commenting on my coursework, which was deeply touching. The entire process was straightforward and hassle‑free, with no tedious online forms to complete. I highly recommend this journal. Best wishes from, DR Aibing Rao, Head of R&D

I Appreciate the Opportunity to Share my Experience with the Journal of Clinical Research and Reports. The peer review process was timely and constructive, and the feedback provided helped improve the quality of our manuscript. The editorial office was professional, responsive, and supportive throughout the process, ensuring smooth communication and efficient handling of the submission. Overall, it was a positive experience collaborating with your team.

Dear Mercy Grace, Editorial Coordinator of Obstetrics Gynecology and Reproductive Sciences, We would like to express our gratitude for your help at all stages of publishing and editing the article. The editors of the magazine answer all the necessary questions and help at every stage. We will definitely continue to cooperate and publish other works in the Obstetrics Gynecology and Reproductive Sciences! Best wishes from, Alla Konstantinovna Politova,

Dear Maria Emerson, Editorial Coordinator of International Journal of Clinical Case Reports and Reviews, What distinguishes International Journal of Clinical Case Report and Review is not only the scientific rigor of its publications, but the intellectual climate in which research is evaluated. The submission process is refreshingly free of unnecessary formal barriers and bureaucratic rituals that often complicate academic publishing without adding real value. The peer-review system is demanding yet constructive, guided by genuine scientific dialogue rather than hierarchical or authoritarian attitudes. Reviewers act as collaborators in improving the manuscript, not as gatekeepers imposing arbitrary standards. This journal offers a rare balance: high methodological standards combined with a respectful, transparent, and supportive editorial approach. In an era where publishing can feel more burdensome than research itself, this platform restores the original purpose of peer review — to refine ideas, not to obstruct them Prof. Perlat Kapisyzi, FCCP PULMONOLOGIST AND THORACIC IMAGING.

Dear Reader: We have published several articles in the Auctores Publishing, LLC, journal, Clinical Medical Reviews and Reports in recent years (CMRR). This is an ‘open access’ journal and the following are our observations. From the initial invitation to submit an article, to the final edits of galley proofs, we have found CMRR personnel to be professional, responsive, rapid and thorough. This entire process begins with Catherine Mitchell, Editorial Coordinator. She is simply outstanding, and, I believe, unparalleled in her capacity. I cannot imagine a more responsive and dedicated Editorial Coordinator. As I read the dates and timing of her correspondence with us, it seems that she never sleeps. I hope Auctores Publishing, LLC, appreciates her efforts as much as these authors do. Thank you to Auctores Publishing, LLC, to the Editorial Staff/Board, and to Catherine Mitchell from a grateful author(s).

Dear Maria Emerson, Editorial Coordinator of - Journal of Clinical Research and Reports. ''I am pleased to provide this testimonial following the publication of our recent case report in this journal. The peer review process was rigorous, constructive, thorough, and conducted in a timely manner. The reviewers’ comments were thoughtful, detailed, and highly constructive, contributing substantially to the refinement, clarity, and scientific robustness of our manuscript. The process was conducted with professionalism and academic integrity throughout. The support provided by the editorial office was exemplary. Communication was consistently prompt, clear, and courteous at all stages of the submission and publication process. The editorial team demonstrated a high level of organization and responsiveness, ensuring that all queries were addressed efficiently and that the process remained transparent and well-coordinated. The overall quality of the journal is reflected in its strong editorial standards, commitment to scientific excellence, and dedication to publishing clinically meaningful research. It has been a privilege to publish our work in this journal, and we would welcome the opportunity to contribute further in the future.'' Best wishes from, Dr. Efstratios Trogkanis, Cardiologist.

Dear Grace Pierce, Editorial Coordinator of the journal IJCCR, I had a very positive experience with Auctores - Journal throughout the publication process. The Editorial Team was highly responsive, professional, and supportive at every stage. I would like to extend my sincere thanks to the Editor: Grace Pierce, for her guidance and assistance. The peer-review process was smooth and constructive, helping improve the quality of my work. I would gladly recommend Auctores Journal to fellow researchers and authors. Dr. SABITA SINHA, Medical Oncologist, MD (Electro Homeopathy).

Dear Mayra Duenas, Editorial Coordinator of the journal IJCCR, I write here a little on my experience as an author submitting to the International Journal of Clinical Case Reports and Reviews (IJCCR). This was my first submission to IJCCR and my manuscript was inherently an outsider’s effort. It attempted to broadly identify and then make some sense of life’s under-appreciated mysteries. I initially had responded to a request for possible submissions. I then contacted IJCCR with a tentative topic for a manuscript. They quickly got back with an approval for the submission, but with a particular requirement that it be medically relevant. I then put together a manuscript and submitted it. After the usual back-and-forth over forms and formality, the manuscript was sent off for reviews. Within 2 weeks I got back 4 reviews which were both helpful and also surprising. Surprising in that the topic was somewhat foreign to medical literature. My subsequent updates in response to the reviewer comments went smoothly and in short order I had a series of proofs to evaluate. All in all, the whole publication process seemed outstanding. It was both helpful in terms of the paper’s content and also in terms of its efficient and friendly communications. Thank you all very much. Sincerely, Ted Christopher, Rochester, NY.

International Journal of Clinical Case Reports and Reviews is a high quality journal that has a clear and concise submission process. The peer review process was comprehensive and constructive. Support from the editorial office was excellent, since the administrative staff were responsive. The journal provides a fast and timely publication timeline.

Dear Cecilia Lilly, Editorial Coordinator, Endocrinology and Disorders, Thank you so much for your quick response regarding reviewing and all process till publishing our manuscript entitled: Prevalence of Pre-Diabetes and its Associated Risk Factors Among Nile College Students, Sudan. Best regards, Dr Mamoun Magzoub.

Dear Editorial Team, Clinical Cardiology and Cardiovascular Interventions. I am really grateful for the peers review; their feedback gave me the opportunity to reflect on the message and impact of my work and to ameliorate the article. The editors did a great job in addition by encouraging me to continue with the process of publishing.

Dear Mayra Duenas, Editorial Coordinator of ‘International Journal of Clinical Case Reports and Reviews Herewith I confirm an optimal peer review process and a great support of the editorial office of the present journal
Dear Maria Emerson, Editorial Coordinator of ‘International Journal of Clinical Case Reports and Reviews’, I appreciate the opportunity to publish my article with your journal. The editorial office provided clear communication during the submission and review process, and I found the overall experience professional and constructive. Best regards, Elena Salvatore.

Dear Editorial Team, Journal-Clinical Cardiology and Cardiovascular Interventions, “Publishing my article with Clinical Cardiology and Cardiovascular Interventions has been a highly positive experience. The peer-review process was rigorous yet supportive, offering valuable feedback that strengthened my work. The editorial team demonstrated exceptional professionalism, prompt communication, and a genuine commitment to maintaining the highest scientific standards. I am very pleased with the publication quality and proud to be associated with such a reputable journal.” Warm regards, Dr. Mahmoud Kamal Moustafa Ahmed

Dear Editorial Team, Clinical Cardiology and Cardiovascular Interventions. It was truly a rewarding experience to work with the journal “Clinical Cardiology and Cardiovascular Interventions”. The peer review process was insightful and encouraging, helping us refine our work to a higher standard. The editorial office offered exceptional support with prompt and thoughtful communication. I highly value the journal’s role in promoting scientific advancement and am honored to be part of it. Best regards, Meng-Jou Lee, MD, Department of Anesthesiology, National Taiwan University Hospital.

Dear Maria Emerson, Editorial Coordinator, Journal of Clinical Research and Reports. Thank you for publishing our case report: "Clinical Case of Effective Fetal Stem Cells Treatment in a Patient with Autism Spectrum Disorder" within the "Journal of Clinical Research and Reports" being submitted by the team of EmCell doctors from Kyiv, Ukraine. We much appreciate a professional and transparent peer-review process from Auctores. All research Doctors are so grateful to your Editorial Office and Auctores Publishing support! I amiably wish our article publication maintained a top quality of your International Scientific Journal. My best wishes for a prosperity of the Journal of Clinical Research and Reports. Hope our scientific relationship and cooperation will remain long lasting. Thank you very much indeed. Kind regards, Dr. Andriy Sinelnyk Cell Therapy Center EmCell

I recommend without hesitation submitting relevant papers on medical decision making to the International Journal of Clinical Case Reports and Reviews. I am very grateful to the editorial staff. Maria Emerson was a pleasure to communicate with. The time from submission to publication was an extremely short 3 weeks. The editorial staff submitted the paper to three reviewers. Two of the reviewers commented positively on the value of publishing the paper. The editorial staff quickly recognized the third reviewer’s comments as an unjust attempt to reject the paper. I revised the paper as recommended by the first two reviewers.

Dear Chrystine Mejia, Editorial Coordinator, Journal of Neurodegeneration and Neurorehabilitation. “The peer review process was efficient and constructive, and the editorial office provided excellent communication and support throughout. The journal ensures scientific rigor and high editorial standards, while also offering a smooth and timely publication process. We sincerely appreciate the work of the editorial team in facilitating the dissemination of innovative approaches such as the Bonori Method.” Best regards, Dr. Matteo Bonori.

Dear Maria Emerson, Editorial Coordinator, we have deeply appreciated the professionalism demonstrated by the International Journal of Clinical Case Reports and Reviews. The reviewers have extensive knowledge of our field and have been very efficient and fast in supporting the process. I am really looking forward to further collaboration. Thanks. Best regards, Dr. Claudio Ligresti
Dear Ms. Mayra Duenas, Editorial Coordinator, International Journal of Clinical Case Reports and Reviews. “The International Journal of Clinical Case Reports and Reviews represented the “ideal house” to share with the research community a first experience with the use of the Simeox device for speech rehabilitation. High scientific reputation and attractive website communication were first determinants for the selection of this Journal, and the following submission process exceeded expectations: fast but highly professional peer review, great support by the editorial office, elegant graphic layout. Exactly what a dynamic research team - also composed by allied professionals - needs!" From, Chiara Beccaluva, PT - Italy.

Dear Clarissa Eric, Editorial Coordinator, Journal of Clinical Case Reports and Studies, Auctores Publishing LLC, USA Office: +1-(302)-520-2644. I would like to express my sincere appreciation for the efficient and professional handling of my case report by the ‘Journal of Clinical Case Reports and Studies’. The peer review process was not only fast but also highly constructive—the reviewers’ comments were clear, relevant, and greatly helped me improve the quality and clarity of my manuscript. I also received excellent support from the editorial office throughout the process. Communication was smooth and timely, and I felt well guided at every stage, from submission to publication. The overall quality and rigor of the journal are truly commendable. I am pleased to have published my work with Journal of Clinical Case Reports and Studies, and I look forward to future opportunities for collaboration. Sincerely, Aline Tollet, UCLouvain.

Dear Chrystine Mejia, Editorial Coordinator, Journal of Neurodegeneration and Neurorehabilitation, Auctores Publishing LLC, We would like to thank the editorial team for the smooth and high-quality communication leading up to the publication of our article in the Journal of Neurodegeneration and Neurorehabilitation. The reviewers have extensive knowledge in the field, and their relevant questions helped to add value to our publication. Kind regards, Dr. Ravi Shrivastava.

Dear Clarissa Eric, Editorial Coordinator, Journal of Clinical Case Reports and Studies, I would like to express my deep admiration for the exceptional professionalism demonstrated by your journal. I am thoroughly impressed by the speed of the editorial process, the substantive and insightful reviews, and the meticulous preparation of the manuscript for publication. Additionally, I greatly appreciate the courteous and immediate responses from your editorial office to all my inquiries. Best Regards, Dariusz Ziora

Dear Ashley Rosa, Editorial Coordinator, International Journal of Clinical Case Reports and Reviews, Auctores Publishing LLC. Thank you for publishing our article, Exploring Clozapine's Efficacy in Managing Aggression: A Multiple Single-Case Study in Forensic Psychiatry in the international journal of clinical case reports and reviews. We found the peer review process very professional and efficient. The comments were constructive, and the whole process was efficient. On behalf of the co-authors, I would like to thank you for publishing this article. With regards, Dr. Jelle R. Lettinga.

Dear Jessica Magne, Editorial Coordinator, Clinical Cardiology and Cardiovascular Interventions, Auctores Publishing LLC. The peer review process of the journal of Clinical Cardiology and Cardiovascular Interventions was excellent and fast, as was the support of the editorial office and the quality of the journal. Kind regards Walter F. Riesen Prof. Dr. Dr. h.c. Walter F. Riesen.

Dear Erin Aust, Editorial Coordinator, Journal of General Medicine and Clinical Practice. We are pleased to share our experience with the “Journal of General Medicine and Clinical Practice”, following the successful publication of our article. The peer review process was thorough and constructive, helping to improve the clarity and quality of the manuscript. We are especially thankful to Ms. Erin Aust, the Editorial Coordinator, for her prompt communication and continuous support throughout the process. Her professionalism ensured a smooth and efficient publication experience. The journal upholds high editorial standards, and we highly recommend it to fellow researchers seeking a credible platform for their work. Best wishes By, Dr. Rakhi Mishra.

Dr Hala Al Shaikh This is to acknowledge that the peer review process for the article ’ A Novel Gnrh1 Gene Mutation in Four Omani Male Siblings, Presentation and Management ’ sent to the International Journal of Clinical Case Reports and Reviews was quick and smooth. The editorial office was prompt with easy communication.

Dear Agrippa Hilda, Editorial Coordinator, Journal of Neuroscience and Neurological Surgery. The entire process including article submission, review, revision, and publication was extremely easy. The journal editor was prompt and helpful, and the reviewers contributed to the quality of the paper. Thank you so much! Eric Nussbaum, MD

Dear Ashley Rosa, Editorial Coordinator, International Journal of Clinical Case Reports and Reviews. Many thanks for publishing this manuscript after I lost confidence the editors were most helpful, more than other journals Best wishes from, Susan Anne Smith, PhD. Australian Breastfeeding Association.

Dear Maria Emerson, Editorial Coordinator, International Journal of Clinical Case Reports and Reviews, Auctores Publishing LLC. I am delighted to have published our manuscript, "Acute Colonic Pseudo-Obstruction (ACPO): A rare but serious complication following caesarean section." I want to thank the editorial team, especially Maria Emerson, for their prompt review of the manuscript, quick responses to queries, and overall support. Yours sincerely Dr. Victor Olagundoye.

Dear Jessica Magne, Editorial Coordinator, Clinical Cardiology and Cardiovascular Interventions, Auctores Publishing LLC. I appreciate the journal (JCCI) editorial office support, the entire team leads were always ready to help, not only on technical front but also on thorough process. Also, I should thank dear reviewers’ attention to detail and creative approach to teach me and bring new insights by their comments. Surely, more discussions and introduction of other hemodynamic devices would provide better prevention and management of shock states. Your efforts and dedication in presenting educational materials in this journal are commendable. Best wishes from, Farahnaz Fallahian.

Dear Ashley Rosa, Editorial Coordinator of the journal - Psychology and Mental Health Care. " The process of obtaining publication of my article in the Psychology and Mental Health Journal was positive in all areas. The peer review process resulted in a number of valuable comments, the editorial process was collaborative and timely, and the quality of this journal has been quickly noticed, resulting in alternative journals contacting me to publish with them." Warm regards, Susan Anne Smith, PhD. Australian Breastfeeding Association.

Dear Jessica, and the super professional team of the ‘Clinical Cardiology and Cardiovascular Interventions’ I am sincerely grateful to the coordinated work of the journal team for the no problem with the submission of my manuscript: “Cardiometabolic Disorders in A Pregnant Woman with Severe Preeclampsia on the Background of Morbid Obesity (Case Report).” The review process by 5 experts was fast, and the comments were professional, which made it more specific and academic, and the process of publication and presentation of the article was excellent. I recommend that my colleagues publish articles in this journal, and I am interested in further scientific cooperation. Sincerely and best wishes, Dr. Oleg Golyanovskiy.

To Dear Erin Aust – Editorial Coordinator of Journal of General Medicine and Clinical Practice! I declare that I am absolutely satisfied with your work carried out with great competence in following the manuscript during the various stages from its receipt, during the revision process to the final acceptance for publication. Thank Prof. Elvira Farina

My article, titled 'No Way Out of the Smartphone Epidemic Without Considering the Insights of Brain Research,' has been republished in the International Journal of Clinical Case Reports and Reviews. The review process was seamless and professional, with the editors being both friendly and supportive. I am deeply grateful for their efforts.

We found the peer review process quick and positive in its input. The support from the editorial officer has been very agile, always with the intention of improving the article and taking into account our subsequent corrections.

Dear Jessica Magne, with gratitude for the joint work. Fast process of receiving and processing the submitted scientific materials in “Clinical Cardiology and Cardiovascular Interventions”. High level of competence of the editors with clear and correct recommendations and ideas for enriching the article.

I thank the ‘Journal of Clinical Research and Reports’ for accepting this article for publication. This is a rigorously peer reviewed journal which is on all major global scientific data bases. I note the review process was prompt, thorough and professionally critical. It gave us an insight into a number of important scientific/statistical issues. The review prompted us to review the relevant literature again and look at the limitations of the study. The peer reviewers were open, clear in the instructions and the editorial team was very prompt in their communication. This journal certainly publishes quality research articles. I would recommend the journal for any future publications.

"I am grateful for the opportunity of contributing to [International Journal of Clinical Case Reports and Reviews] and for the rigorous review process that enhances the quality of research published in your esteemed journal. I sincerely appreciate the time and effort of your team who have dedicatedly helped me in improvising changes and modifying my manuscript. The insightful comments and constructive feedback provided have been invaluable in refining and strengthening my work".

To Dear Erin Aust, I would like to express my heartfelt appreciation for the opportunity to have my work published in this esteemed journal. The entire publication process was smooth and well-organized, and I am extremely satisfied with the final result. The Editorial Team demonstrated the utmost professionalism, providing prompt and insightful feedback throughout the review process. Their clear communication and constructive suggestions were invaluable in enhancing my manuscript, and their meticulous attention to detail and dedication to quality are truly commendable. Additionally, the support from the Editorial Office was exceptional. From the initial submission to the final publication, I was guided through every step of the process with great care and professionalism. The team's responsiveness and assistance made the entire experience both easy and stress-free. I am also deeply impressed by the quality and reputation of the journal. It is an honor to have my research featured in such a respected publication, and I am confident that it will make a meaningful contribution to the field.

I would like to express my sincere gratitude for the support and efficiency provided by the editorial office throughout the publication process of my article, “Delayed Vulvar Metastases from Rectal Carcinoma: A Case Report.” I greatly appreciate the assistance and guidance I received from your team, which made the entire process smooth and efficient. The peer review process was thorough and constructive, contributing to the overall quality of the final article. I am very grateful for the high level of professionalism and commitment shown by the editorial staff, and I look forward to maintaining a long-term collaboration with the International Journal of Clinical Case Reports and Reviews.

Dear Agrippa Hilda- Editorial Coordinator of Journal of Neuroscience and Neurological Surgery, "The peer review process was very quick and of high quality, which can also be seen in the articles in the journal. The collaboration with the editorial office was very good."

I would like to offer my testimony in the support. I have received through the peer review process and support the editorial office where they are to support young authors like me, encourage them to publish their work in your esteemed journals, and globalize and share knowledge globally. I really appreciate your journal, peer review, and editorial office.

My experience publishing in International Journal of Clinical Case Reports and Reviews was exceptional. I Come forth to Provide a Testimonial Covering the Peer Review Process and the editorial office for the Professional and Impartial Evaluation of the Manuscript.

My experience publishing in Psychology and Mental Health Care was exceptional. The peer review process was rigorous and constructive, with reviewers providing valuable insights that helped enhance the quality of our work. The editorial team was highly supportive and responsive, making the submission process smooth and efficient. The journal's commitment to high standards and academic rigor makes it a respected platform for quality research. I am grateful for the opportunity to publish in such a reputable journal.

My Testimonial Covering as fellowing: Lin-Show Chin. The peer reviewers process is quick and effective, the supports from editorial office is excellent, the quality of journal is high. I would like to collabroate with Internatioanl journal of Clinical Case Reports and Reviews.

Dealing with The Journal of Neurology and Neurological Surgery was very smooth and comprehensive. The office staff took time to address my needs and the response from editors and the office was prompt and fair. I certainly hope to publish with this journal again.Their professionalism is apparent and more than satisfactory. Susan Weiner

Dear Editorial Coordinator of the Journal of Nutrition and Food Processing! "I would like to thank the Journal of Nutrition and Food Processing for including and publishing my article. The peer review process was very quick, movement and precise. The Editorial Board has done an extremely conscientious job with much help, valuable comments and advices. I find the journal very valuable from a professional point of view, thank you very much for allowing me to be part of it and I would like to participate in the future!”

Dear Monica Gissare, - Editorial Coordinator of Nutrition and Food Processing. ¨My testimony with you is truly professional, with a positive response regarding the follow-up of the article and its review, you took into account my qualities and the importance of the topic¨.

Dear Dr. Jessica Magne, Editorial Coordinator 0f Clinical Cardiology and Cardiovascular Interventions, I hope this message finds you well. I want to express my utmost gratitude for your excellent work and for the dedication and speed in the publication process of my article titled "Navigating Innovation: Qualitative Insights on Using Technology for Health Education in Acute Coronary Syndrome Patients." I am very satisfied with the peer review process, the support from the editorial office, and the quality of the journal. I hope we can maintain our scientific relationship in the long term.

Clinical Cardiology and Cardiovascular Interventions, I would like to express my sincerest gratitude for the trust placed in our team for the publication in your journal. It has been a true pleasure to collaborate with you on this project. I am pleased to inform you that both the peer review process and the attention from the editorial coordination have been excellent. Your team has worked with dedication and professionalism to ensure that your publication meets the highest standards of quality. We are confident that this collaboration will result in mutual success, and we are eager to see the fruits of this shared effort.

The peer reviewers process is quick and effective, the supports from editorial office is excellent, the quality of journal is high. I would like to collabroate with Internatioanl journal of Clinical Case Reports and Reviews journal clinically in the future time.

Clinical Cardiology and Cardiovascular Interventions, we deeply appreciate the interest shown in our work and its publication. It has been a true pleasure to collaborate with you. The peer review process, as well as the support provided by the editorial office, have been exceptional, and the quality of the journal is very high, which was a determining factor in our decision to publish with you.

Clinical Cardiology and Cardiovascular Interventions I testity the covering of the peer review process, support from the editorial office, and quality of the journal.

Dear editorial department: On behalf of our team, I hereby certify the reliability and superiority of the International Journal of Clinical Case Reports and Reviews in the peer review process, editorial support, and journal quality. Firstly, the peer review process of the International Journal of Clinical Case Reports and Reviews is rigorous, fair, transparent, fast, and of high quality. The editorial department invites experts from relevant fields as anonymous reviewers to review all submitted manuscripts. These experts have rich academic backgrounds and experience, and can accurately evaluate the academic quality, originality, and suitability of manuscripts. The editorial department is committed to ensuring the rigor of the peer review process, while also making every effort to ensure a fast review cycle to meet the needs of authors and the academic community. Secondly, the editorial team of the International Journal of Clinical Case Reports and Reviews is composed of a group of senior scholars and professionals with rich experience and professional knowledge in related fields. The editorial department is committed to assisting authors in improving their manuscripts, ensuring their academic accuracy, clarity, and completeness. Editors actively collaborate with authors, providing useful suggestions and feedback to promote the improvement and development of the manuscript. We believe that the support of the editorial department is one of the key factors in ensuring the quality of the journal. Finally, the International Journal of Clinical Case Reports and Reviews is renowned for its high- quality articles and strict academic standards. The editorial department is committed to publishing innovative and academically valuable research results to promote the development and progress of related fields. The International Journal of Clinical Case Reports and Reviews is reasonably priced and ensures excellent service and quality ratio, allowing authors to obtain high-level academic publishing opportunities in an affordable manner. I hereby solemnly declare that the International Journal of Clinical Case Reports and Reviews has a high level of credibility and superiority in terms of peer review process, editorial support, reasonable fees, and journal quality. Sincerely, Rui Tao.

“The peer review process of JPMHC is quick and effective. Authors are benefited by good and professional reviewers with huge experience in the field of psychology and mental health. The support from the editorial office is very professional. People to contact to are friendly and happy to help and assist any query authors might have. Quality of the Journal is scientific and publishes ground-breaking research on mental health that is useful for other professionals in the field”.

Dr.Tania Muñoz, My experience as researcher and author of a review article in The Journal Clinical Cardiology and Interventions has been very enriching and stimulating. The editorial team is excellent, performs its work with absolute responsibility and delivery. They are proactive, dynamic and receptive to all proposals. Supporting at all times the vast universe of authors who choose them as an option for publication. The team of review specialists, members of the editorial board, are brilliant professionals, with remarkable performance in medical research and scientific methodology. Together they form a frontline team that consolidates the JCCI as a magnificent option for the publication and review of high-level medical articles and broad collective interest. I am honored to be able to share my review article and open to receive all your comments.

I am delighted to publish our manuscript entitled "A Perspective on Cocaine Induced Stroke - Its Mechanisms and Management" in the Journal of Neuroscience and Neurological Surgery. The peer review process, support from the editorial office, and quality of the journal are excellent. The manuscripts published are of high quality and of excellent scientific value. I recommend this journal very much to colleagues.

I would like to give my testimony in the support I have got by the peer review process and to support the editorial office where they were of asset to support young author like me to be encouraged to publish their work in your respected journal and globalize and share knowledge across the globe. I really give my great gratitude to your journal and the peer review including the editorial office.

I am very pleased to serve as EBM of the journal, I hope many years of my experience in stem cells can help the journal from one way or another. As we know, stem cells hold great potential for regenerative medicine, which are mostly used to promote the repair response of diseased, dysfunctional or injured tissue using stem cells or their derivatives. I think Stem Cell Research and Therapeutics International is a great platform to publish and share the understanding towards the biology and translational or clinical application of stem cells.

We are grateful for this opportunity to provide a glowing recommendation to the Journal of Psychiatry and Psychotherapy. We found that the editorial team were very supportive, helpful, kept us abreast of timelines and over all very professional in nature. The peer review process was rigorous, efficient and constructive that really enhanced our article submission. The experience with this journal remains one of our best ever and we look forward to providing future submissions in the near future.

I would like to express my gratitude towards you process of article review and submission. I found this to be very fair and expedient. Your follow up has been excellent. I have many publications in national and international journal and your process has been one of the best so far. Keep up the great work.

"We recently published an article entitled “Influence of beta-Cyclodextrins upon the Degradation of Carbofuran Derivatives under Alkaline Conditions" in the Journal of “Pesticides and Biofertilizers” to show that the cyclodextrins protect the carbamates increasing their half-life time in the presence of basic conditions This will be very helpful to understand carbofuran behaviour in the analytical, agro-environmental and food areas. We greatly appreciated the interaction with the editor and the editorial team; we were particularly well accompanied during the course of the revision process, since all various steps towards publication were short and without delay".

I am very glad to say that the peer review process is very successful and fast and support from the Editorial Office. Therefore, I would like to continue our scientific relationship for a long time. And I especially thank you for your kindly attention towards my article. Have a good day!

Dear Erica Kelsey, Editorial Coordinator of Cancer Research and Cellular Therapeutics Our team is very satisfied with the processing of our paper by your journal. That was fast, efficient, rigorous, but without unnecessary complications. We appreciated the very short time between the submission of the paper and its publication on line on your site.

Thank you very much for publishing my Research Article titled “Comparing Treatment Outcome Of Allergic Rhinitis Patients After Using Fluticasone Nasal Spray And Nasal Douching" in the Journal of Clinical Otorhinolaryngology. As Medical Professionals we are immensely benefited from study of various informative Articles and Papers published in this high quality Journal. I look forward to enriching my knowledge by regular study of the Journal and contribute my future work in the field of ENT through the Journal for use by the medical fraternity. The support from the Editorial office was excellent and very prompt. I also welcome the comments received from the readers of my Research Article.

International Journal of Clinical Case Reports and Reviews. I strongly recommend to consider submitting your work to this high-quality journal. The support and availability of the Editorial staff is outstanding and the review process was both efficient and rigorous.

Dear Agrippa Hilda, Journal of Neuroscience and Neurological Surgery, Editorial Coordinator, I trust this message finds you well. I want to extend my appreciation for considering my article for publication in your esteemed journal. I am pleased to provide a testimonial regarding the peer review process and the support received from your editorial office. The peer review process for my paper was carried out in a highly professional and thorough manner. The feedback and comments provided by the authors were constructive and very useful in improving the quality of the manuscript. This rigorous assessment process undoubtedly contributes to the high standards maintained by your journal.

As an author who has recently published in the journal "Brain and Neurological Disorders". I am delighted to provide a testimonial on the peer review process, editorial office support, and the overall quality of the journal. The peer review process at Brain and Neurological Disorders is rigorous and meticulous, ensuring that only high-quality, evidence-based research is published. The reviewers are experts in their fields, and their comments and suggestions were constructive and helped improve the quality of my manuscript. The review process was timely and efficient, with clear communication from the editorial office at each stage. The support from the editorial office was exceptional throughout the entire process. The editorial staff was responsive, professional, and always willing to help. They provided valuable guidance on formatting, structure, and ethical considerations, making the submission process seamless. Moreover, they kept me informed about the status of my manuscript and provided timely updates, which made the process less stressful. The journal Brain and Neurological Disorders is of the highest quality, with a strong focus on publishing cutting-edge research in the field of neurology. The articles published in this journal are well-researched, rigorously peer-reviewed, and written by experts in the field. The journal maintains high standards, ensuring that readers are provided with the most up-to-date and reliable information on brain and neurological disorders. In conclusion, I had a wonderful experience publishing in Brain and Neurological Disorders. The peer review process was thorough, the editorial office provided exceptional support, and the journal's quality is second to none. I would highly recommend this journal to any researcher working in the field of neurology and brain disorders.

Dear Hao Jiang, to Journal of Nutrition and Food Processing We greatly appreciate the efficient, professional and rapid processing of our paper by your team. If there is anything else we should do, please do not hesitate to let us know. On behalf of my co-authors, we would like to express our great appreciation to editor and reviewers.

This is an acknowledgment for peer reviewers, editorial board of Journal of Clinical Research and Reports. They show a lot of consideration for us as publishers for our research article “Evaluation of the different factors associated with side effects of COVID-19 vaccination on medical students, Mutah university, Al-Karak, Jordan”, in a very professional and easy way. This journal is one of outstanding medical journal.

Dr. Bernard Terkimbi Utoo, I am happy to publish my scientific work in Journal of Women Health Care and Issues (JWHCI). The manuscript submission was seamless and peer review process was top notch. I was amazed that 4 reviewers worked on the manuscript which made it a highly technical, standard and excellent quality paper. I appreciate the format and consideration for the APC as well as the speed of publication. It is my pleasure to continue with this scientific relationship with the esteem JWHCI.

Testimony of Journal of Clinical Otorhinolaryngology: work with your Reviews has been a educational and constructive experience. The editorial office were very helpful and supportive. It was a pleasure to contribute to your Journal.

Thank you most sincerely, with regard to the support you have given in relation to the reviewing process and the processing of my article entitled "Large Cell Neuroendocrine Carcinoma of The Prostate Gland: A Review and Update" for publication in your esteemed Journal, Journal of Cancer Research and Cellular Therapeutics". The editorial team has been very supportive.

Dr. Katarzyna Byczkowska My testimonial covering: "The peer review process is quick and effective. The support from the editorial office is very professional and friendly. Quality of the Clinical Cardiology and Cardiovascular Interventions is scientific and publishes ground-breaking research on cardiology that is useful for other professionals in the field.
Journal of Neuroscience and Neurological Surgery. I had the experience of publishing a research article recently. The whole process was simple from submission to publication. The reviewers made specific and valuable recommendations and corrections that improved the quality of my publication. I strongly recommend this Journal.

The peer-review process which consisted high quality queries on the paper. I did answer six reviewers’ questions and comments before the paper was accepted. The support from the editorial office is excellent.

We would like to thank the Journal of Thoracic Disease and Cardiothoracic Surgery because of the services they provided us for our articles. The peer-review process was done in a very excellent time manner, and the opinions of the reviewers helped us to improve our manuscript further. The editorial office had an outstanding correspondence with us and guided us in many ways. During a hard time of the pandemic that is affecting every one of us tremendously, the editorial office helped us make everything easier for publishing scientific work. Hope for a more scientific relationship with your Journal.

Journal of Clinical Research and Reports I would be very delighted to submit my testimonial regarding the reviewer board and the editorial office. The reviewer board were accurate and helpful regarding any modifications for my manuscript. And the editorial office were very helpful and supportive in contacting and monitoring with any update and offering help. It was my pleasure to contribute with your promising Journal and I am looking forward for more collaboration.

Journal of Women Health Care and Issues By the present mail, I want to say thank to you and tour colleagues for facilitating my published article. Specially thank you for the peer review process, support from the editorial office. I appreciate positively the quality of your journal.

Journal of Clinical Cardiology and Cardiovascular Intervention The submission and review process was adequate. However I think that the publication total value should have been enlightened in early fases. Thank you for all.

Clearly Auctoresonline and particularly Psychology and Mental Health Care Journal is dedicated to improving health care services for individuals and populations. The editorial boards' ability to efficiently recognize and share the global importance of health literacy with a variety of stakeholders. Auctoresonline publishing platform can be used to facilitate of optimal client-based services and should be added to health care professionals' repertoire of evidence-based health care resources.
