

Review Article | DOI: https://doi.org/10.31579/2641-0419/560
1Department of Cardiology, Hitit University Erol Olçok Education and Research Hospital, Corum, Turkey.
2Department of Cardiology, Faculty of Medicine, Hitit University, Corum, Turkey.
3Department of Cardiology, Gediz State Hospital, Kütahya, Turkey.
*Corresponding Author: Abdülmelik Birgün, Department of Cardiology, Hitit University Erol Olçok Education and Research Hospital, Corum, Turkey.
Citation: Abdülmelik Birgün, Lütfü Bekar, Macit Kalçık, Abdullah Sarıhan, Mehmet M. Şahin, et al, (2026), Peripartum Cardiomyopathy: Pathophysiological Mechanisms, Clinical Spectrum, and Long-Term Outcomes, J Clinical Cardiology and Cardiovascular Interventions, 9(7); DOI:10.31579/2641-0419/560
Copyright: © 2026, Abdülmelik Birgün. This is an open-access article distributed under the terms of the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original author and source are credited.
Received: 06 March 2026 | Accepted: 17 April 2026 | Published: 23 April 2026
Keywords: peripartum cardiomyopathy; angiogenic imbalance; prolactin cleavage; left ventricular recovery; pregnancy-associated heart failure
Peripartum cardiomyopathy (PPCM) is an idiopathic systolic heart failure syndrome occurring in late pregnancy or the early postpartum period in the absence of pre-existing structural heart disease. Once considered a rare obstetric complication, PPCM is now recognized as a heterogeneous cardiomyopathy arising from the interplay of pregnancy-related vascular stress and underlying myocardial vulnerability. This narrative review summarizes current evidence on epidemiology, pathophysiology, clinical presentation, imaging, management, and long-term outcomes. Contemporary mechanistic models emphasize angiogenic imbalance, prolactin cleavage, oxidative stress, inflammation, and genetic susceptibility as central contributors to myocardial dysfunction. Clinical presentation ranges from mild heart failure symptoms to cardiogenic shock, ventricular arrhythmias, and thromboembolism. Echocardiography remains the diagnostic cornerstone, while strain imaging and cardiac magnetic resonance provide additional phenotypic and prognostic insight. Recovery is highly variable; although many women demonstrate substantial improvement within 6–12 months, a significant proportion develop persistent left ventricular dysfunction with long-term implications. Baseline ventricular function and early recovery trajectory are key determinants of outcome. Management requires pregnancy-adapted heart failure therapy, structured follow-up, and multidisciplinary cardio-obstetric care. Future efforts should prioritize phenotype-driven strategies, optimized risk stratification, and large collaborative registries to refine precision management in PPCM.
Peripartum cardiomyopathy (PPCM) is an idiopathic form of systolic heart failure (HF) that develops toward the end of pregnancy or in the months following delivery, in the absence of another identifiable cause of cardiac dysfunction (1). It is characterized by left ventricular systolic impairment, typically defined by a left ventricular ejection fraction (LVEF) below 45%, with or without ventricular dilatation, and no pre-existing structural heart disease (2). Despite advances in cardiovascular medicine, PPCM remains a clinically challenging entity due to its unpredictable course and heterogeneous presentation.
Although descriptions of pregnancy-associated HF date back to the 19th century, PPCM has evolved into a well-defined clinical entity through contemporary consensus statements and state-of-the-art reviews (3,4). Modern definitions emphasize a diagnosis based on clinical context and exclusion of alternative causes rather than strict temporal boundaries alone.
Traditionally, PPCM has been defined as occurring during the last month of pregnancy and up to five months postpartum. However, more recent evidence indicates that left ventricular dysfunction may manifest earlier during gestation or extend beyond the classical postpartum window. Accordingly, current expert recommendations advocate for a flexible, clinically oriented diagnostic framework that integrates imaging findings and exclusion of competing etiologies (2–4).
The clinical significance of PPCM lies in its substantial contribution to maternal morbidity and mortality worldwide. Patients may present with acute decompensated HF, cardiogenic shock, ventricular arrhythmias, or thromboembolic complications. In severe cases, advanced HF therapies including mechanical circulatory support or cardiac transplantation may be required (3,4). The incidence of PPCM varies considerably across geographic regions, with disproportionately higher rates reported in parts of sub-Saharan Africa, underscoring potential environmental, genetic, and socioeconomic influences (5).
Distinguishing PPCM from other pregnancy-associated cardiomyopathies is essential for accurate diagnosis and management. Differential considerations include previously unrecognized dilated cardiomyopathy unmasked by pregnancy, hypertensive heart disease related to preeclampsia, and genetically mediated cardiomyopathies presenting during gestation (2,4). Emerging genetic data suggest that a subset of women with PPCM harbor pathogenic variants similar to those identified in familial dilated cardiomyopathy, supporting the concept that PPCM represents a multifactorial and partially genetically predisposed condition (3,4).
The objective of this narrative review is to provide a comprehensive synthesis of the current understanding of PPCM, focusing on its pathophysiological mechanisms including prolactin cleavage, angiogenic imbalance, inflammatory activation, and genetic susceptibility while also summarizing the clinical spectrum, diagnostic strategies, and short- and long-term outcomes.
The global incidence of PPCM varies considerably across regions, reflecting differences in genetic background, socioeconomic conditions, healthcare infrastructure, and diagnostic awareness. In high-income countries, incidence is generally estimated between 1 in 1,000 and 1 in 4,000 live births (3,6). However, these figures likely underestimate the true burden due to diagnostic challenges and variability in reporting systems.
Geographic heterogeneity is particularly pronounced. In the United States, contemporary population-based analyses estimate an incidence of approximately 1 in 1,000 to 1 in 4,000 live births, with disproportionately higher rates among women of African ancestry (6,7). In contrast, substantially higher incidences have been reported in parts of sub-Saharan Africa, especially Nigeria and South Africa, where rates may approach 1 in 100 to 1 in 1,000 live births (8). European countries generally report lower incidence rates, although comprehensive national registry data remain limited (4,6). Data from Asian populations are less robust; available studies suggest lower reported incidence, but under-recognition and limited registry infrastructure may contribute to this observation (6).
PPCM represents a significant contributor to maternal morbidity and mortality. In the United States, cardiomyopathy has emerged as one of the leading causes of pregnancy-related death, particularly in the late postpartum period (7). Similar patterns have been observed in European surveillance systems, where cardiovascular disease constitutes a major non-obstetric cause of maternal mortality (4). Mortality rates vary substantially by region, ranging from below 5% in high-resource settings to considerably higher rates in parts of Africa, where delayed diagnosis and limited access to advanced HF therapies remain critical barriers (6,8).
Temporal trends suggest increasing recognition of PPCM over the past two decades. Nationwide analyses from the United States demonstrate a rise in reported incidence, which may reflect improved awareness, changing maternal demographics (including advanced maternal age), higher prevalence of hypertensive disorders of pregnancy, and enhanced coding practices (6). Whether this represents a true increase in disease occurrence or improved detection remains uncertain.
Underdiagnosis continues to represent a major limitation in accurately defining disease burden. Symptoms such as dyspnea, fatigue, and peripheral edema overlap with physiological changes of late pregnancy and the postpartum period, potentially delaying imaging and definitive diagnosis (3,6). Furthermore, many epidemiological estimates rely on administrative databases rather than prospective registries, introducing risks of misclassification and incomplete longitudinal follow-up (6). Even multinational registries may be influenced by referral bias toward more severe cases.
Collectively, current epidemiological data underscore that PPCM is a globally relevant yet heterogeneously distributed condition. Improved multinational registry collaboration and standardized diagnostic frameworks are essential to better quantify incidence, identify high-risk populations, and refine preventive strategies.
3.1 Classic Diagnostic Criteria
The classic diagnostic criteria for PPCM are based on the development of new-onset HF toward the end of pregnancy or in the early postpartum period, in the absence of another identifiable cause (9,10). Although historically confined to the last month of pregnancy through five months postpartum, contemporary scientific statements emphasize that the diagnosis should be guided primarily by clinical context and exclusion of alternative etiologies rather than rigid temporal boundaries (9).
A fundamental diagnostic requirement is left ventricular systolic dysfunction, typically defined as a LVEF below 45%, with or without left ventricular dilatation (9,10). Left ventricular enlargement is not mandatory for diagnosis, which distinguishes PPCM from classical dilated cardiomyopathy phenotypes. Transthoracic echocardiography (TTE) remains the first-line imaging modality, most commonly demonstrating global hypokinesia and variable degrees of functional mitral regurgitation.
Equally essential is the documented absence of pre-existing structural heart disease prior to late pregnancy (9,10). PPCM therefore remains a diagnosis of exclusion. Careful assessment is required to rule out ischemic cardiomyopathy, hypertensive heart disease related to preeclampsia, myocarditis, tachycardia-induced cardiomyopathy, and previously unrecognized familial dilated cardiomyopathy.
Despite expanding mechanistic insights and recognition of genetic overlap with dilated cardiomyopathy, the triad of temporal association, LVEF <45>
3.2 Expanded Contemporary Definitions
Although PPCM has traditionally been defined as occurring in the last month of pregnancy or within five months postpartum, growing evidence suggests that LV systolic dysfunction may develop earlier during gestation (9,11). Contemporary cohort analyses and expert reviews acknowledge that cases presenting in the second or early third trimester without an alternative explanation may fall within the same disease spectrum rather than representing a separate entity (9,11). This broader interpretation reflects improved imaging accessibility and increased clinical awareness.
Recognition of earlier gestational onset carries important clinical implications. Women presenting with otherwise unexplained LV systolic dysfunction during mid-to-late pregnancy should prompt consideration of PPCM within an expanded diagnostic framework (9). Strict reliance on historical temporal cutoffs may therefore delay appropriate recognition and management.
An additional evolving concept is the identification of subclinical LV dysfunction. Advances in myocardial deformation imaging, particularly global longitudinal strain (GLS), have demonstrated that impaired myocardial mechanics may precede overt reductions in LVEF (12). Abnormal GLS profiles have been associated with disease severity and outcomes in PPCM, even when conventional ejection fraction measurements are only mildly reduced. These findings support the concept that PPCM may represent a continuum of myocardial injury rather than a binary diagnosis based solely on LVEF thresholds.
Cardiac magnetic resonance imaging (CMR) further contributes to refined phenotyping by allowing tissue characterization and detection of myocardial edema or fibrosis in selected cases (9). Although not required for diagnosis, advanced imaging modalities support the contemporary view that PPCM encompasses a broader spectrum of myocardial involvement than initially recognized.
Collectively, contemporary data support a more flexible and pathophysiology-informed definition of PPCM one that accommodates earlier gestational presentation and recognizes subclinical myocardial dysfunction. While traditional criteria remain clinically practical, the modern conceptual framework increasingly views PPCM as a dynamic and heterogeneous spectrum.
3.3 Differential Diagnosis
PPCM remains fundamentally a diagnosis of exclusion. Several cardiac conditions may mimic its clinical and echocardiographic presentation, particularly during late pregnancy and the early postpartum period. Accurate differentiation is essential, as prognosis and management strategies may differ substantially.
One major consideration is previously unrecognized dilated cardiomyopathy (DCM). Pregnancy imposes significant hemodynamic stress, which may unmask subclinical or genetically mediated DCM (9,13). The presence of a family history of cardiomyopathy, persistent LV dysfunction beyond the expected recovery window, or identification of pathogenic variants associated with DCM may support this alternative diagnosis. Contemporary genetic data demonstrate overlap between PPCM and familial DCM, further complicating the distinction (13).
Hypertensive heart disease represents another important differential diagnosis. Chronic hypertension or severe gestational hypertension can lead to left ventricular hypertrophy, diastolic dysfunction, and, in advanced cases, systolic impairment (14). Unlike PPCM, hypertensive cardiomyopathy typically demonstrates concentric remodeling rather than global dilatation and is often accompanied by longstanding blood pressure elevation.
Closely related is preeclampsia-associated cardiac dysfunction. Preeclampsia is characterized by systemic endothelial dysfunction and increased afterload, which may result in transient LV systolic or diastolic abnormalities (14,15). In some cases, systolic dysfunction overlaps phenotypically with PPCM. However, preeclampsia-related cardiac dysfunction often improves rapidly following delivery and blood pressure control, whereas PPCM may demonstrate a more protracted or incomplete recovery. Biomarker patterns and imaging findings may assist in differentiation but are not definitive.
Myocarditis must also be considered, particularly in patients presenting with chest pain, elevated troponin levels, or regional wall motion abnormalities. CMR may reveal myocardial edema or late gadolinium enhancement (LGE) patterns suggestive of inflammatory myocardial injury (16). Although inflammatory mechanisms have been implicated in PPCM pathophysiology, classic viral myocarditis represents a distinct entity with different histopathological features.
Finally, Takotsubo cardiomyopathy (stress-induced cardiomyopathy) may mimic PPCM in the peripartum period. Emotional and physical stress related to labor and delivery may trigger transient LV systolic dysfunction with characteristic regional wall motion abnormalities, most commonly apical ballooning (17). In contrast to PPCM, Takotsubo cardiomyopathy typically demonstrates rapid recovery of systolic function and distinct imaging patterns on echocardiography and CMR.
In summary, differentiation between PPCM and other pregnancy-associated cardiac disorders requires a systematic approach integrating clinical history, imaging findings, biomarker profiles, and, when appropriate, genetic evaluation. Recognition of these alternative diagnoses ensures accurate prognostication and tailored management.
4.1 Maternal Factors
Several maternal characteristics have consistently been associated with an increased risk of developing PPCM. Although these factors do not establish causality, epidemiological data suggest that they contribute to disease susceptibility within a multifactorial framework.
Advanced maternal age is one of the most reproducible risk factors. Population-based analyses from the United States demonstrate that women over 30–35 years of age exhibit a significantly higher incidence of PPCM compared with younger mothers (18). Increasing maternal age may amplify vulnerability through cumulative cardiovascular stress, higher prevalence of hypertensive disorders, and reduced myocardial reserve.
Multiparity has also been repeatedly linked to PPCM. Earlier observational studies and registry data indicate that women with multiple prior pregnancies carry an elevated risk (19). The proposed mechanisms include repeated exposure to pregnancy-related hemodynamic load, hormonal fluctuations, and angiogenic stress. However, it remains unclear whether multiparity itself is causal or whether it reflects coexisting socioeconomic and healthcare-related variables.
African ancestry represents one of the strongest epidemiological associations. Women of African descent have a disproportionately higher incidence and often more severe disease presentation compared with other ethnic groups (18,20). Data from both U.S. cohorts and African registries support this observation. The underlying explanation is likely multifactorial, involving genetic susceptibility, differences in hypertension prevalence, environmental influences, and disparities in healthcare access. Importantly, genetic studies have identified pathogenic variants shared between PPCM and dilated cardiomyopathy, suggesting that ancestry-related genetic architecture may partially explain observed risk differences (13).
A family history of cardiomyopathy further strengthens the concept that PPCM is not purely pregnancy-induced but may unmask latent myocardial vulnerability. In genomic analyses, truncating variants in genes commonly implicated in dilated cardiomyopathy such as TTN have been identified in a subset of women with PPCM (13). These findings suggest that pregnancy may function as a physiological “stress test,” revealing previously silent genetic cardiomyopathy.
Collectively, maternal risk factors underscore that PPCM emerges from the intersection of hemodynamic stress, hormonal and angiogenic shifts, and underlying myocardial susceptibility. Advanced age, multiparity, African ancestry, and family history should therefore prompt heightened clinical vigilance, although none alone is sufficient for diagnosis.
4.2 Obstetric Factors
Multiple obstetric conditions are consistently enriched among women who develop PPCM, supporting the concept that pregnancy-specific “vascular/angiogenic stressors” can precipitate clinically overt HF in susceptible myocardium (10,24). Among these, multiple gestation is a reproducible association: a recent systematic review and meta-analysis found that twin/multiple pregnancies were linked to a significantly higher odds of PPCM compared with singleton pregnancies (21). This association is biologically plausible, as placental mass and circulating anti-angiogenic factors (notably sFlt-1) are higher in twin gestations, potentially amplifying endothelial and myocardial stress (10).
Preeclampsia/eclampsia is another major obstetric correlate. A systematic review and meta-analysis demonstrated that preeclampsia and hypertensive disorders of pregnancy are markedly more prevalent in women with PPCM than in the general obstetric population, suggesting overlapping pathobiology rather than a coincidental coexistence (24). Contemporary reviews further frame PPCM and preeclampsia as partially “overlapping diseases of pregnancy,” with shared features of endothelial dysfunction, anti-angiogenic signaling, and heightened afterload factors that may worsen myocardial performance during the peripartum period (25). More recent meta-analytic data continue to support an association between hypertensive disorders of pregnancy and PPCM and highlight their impact on LV function and outcomes (22).
Gestational hypertension even without overt preeclampsia has also been identified as a risk factor in pooled analyses of PPCM cohorts (23). Mechanistically, sustained afterload elevation and vascular dysfunction may contribute to myocardial decompensation during a period of already maximal hemodynamic burden. Overall, these obstetric factors reinforce the clinical need for heightened vigilance and a low threshold for cardiac evaluation (including echocardiography) in symptomatic peripartum patients with multiple gestation or hypertensive pregnancy disorders.
4.3 Environmental and Socioeconomic Factors
Environmental and socioeconomic determinants have long been implicated in the pathogenesis and regional variability of PPCM. The strikingly higher incidence observed in certain regions of sub-Saharan Africa has prompted investigation into nutritional status, micronutrient deficiencies, and healthcare access as potential contributors (8).
Malnutrition has historically been proposed as a risk modifier, particularly in regions with high PPCM prevalence. Chronic protein-calorie deficiency may impair myocardial reserve and exacerbate susceptibility to pregnancy-induced hemodynamic stress. Although direct causal evidence remains limited, epidemiological observations from endemic regions suggest that nutritional vulnerability may contribute to disease clustering (26).
Among micronutrients, selenium deficiency has received particular attention. Early studies from northern Nigeria reported lower serum selenium levels in women with PPCM compared with controls, raising the hypothesis that oxidative stress related to selenium deficiency could contribute to myocardial dysfunction (27). Selenium plays a critical role in antioxidant enzyme systems, including glutathione peroxidase; deficiency may therefore enhance oxidative injury in the context of pregnancy-related metabolic stress. However, subsequent data have been heterogeneous, and selenium supplementation has not yet been established as standard preventive therapy.
Limited prenatal care represents another significant factor. Delayed recognition of hypertensive disorders, anemia, or early HF symptoms may contribute to more advanced disease at presentation. In low-resource settings, barriers to prenatal surveillance and echocardiographic evaluation can lead to underdiagnosis or delayed treatment (1). Moreover, socioeconomic constraints may influence postpartum follow-up, medication adherence, and access to advanced heart failure therapies, thereby affecting outcomes.
Importantly, environmental and socioeconomic factors likely interact with biological susceptibility rather than acting independently. Regions with higher PPCM incidence often demonstrate overlapping burdens of hypertensive pregnancy disorders, nutritional deficiencies, and limited healthcare infrastructure. This convergence reinforces the concept that PPCM arises from the intersection of myocardial vulnerability, angiogenic stress, and contextual health determinants.
Collectively, these observations highlight that improving prenatal care access, addressing nutritional deficiencies, and strengthening health systems may represent modifiable avenues to reduce disease burden in high-risk regions. The major maternal, obstetric, genetic, and environmental risk factors and their proposed mechanistic links are summarized in Table 1.
| Category | Specific Factor | Proposed Mechanism | Clinical Implication |
| Maternal | Advanced maternal age (>30–35 years) | Reduced myocardial reserve, increased vascular stress | Higher incidence and severity |
| Multiparity | Repeated hemodynamic and hormonal stress | Increased susceptibility | |
| African ancestry | Genetic predisposition, higher hypertension prevalence | More severe phenotype, lower recovery | |
| Family history of cardiomyopathy | Underlying genetic substrate (e.g., TTN variants) | Higher risk of persistent LV dysfunction | |
| Obstetric | Preeclampsia | Elevated sFlt-1, endothelial dysfunction | Severe presentation, worse outcomes |
| Multiple gestation | Increased placental anti-angiogenic burden | Increased PPCM risk | |
| Gestational hypertension | Increased afterload | LV stress and decompensation | |
| Genetic | TTN truncating variants | Sarcomeric instability | Lower recovery rates |
| DCM-related gene variants | Structural myocardial vulnerability | Chronic cardiomyopathy phenotype | |
| Environmental / Socioeconomic | Selenium deficiency | Enhanced oxidative stress | Regional clustering |
| Limited prenatal care | Delayed diagnosis and treatment | Increased mortality |
Table 1. Major Risk Factors Associated with Peripartum Cardiomyopathy and Their Proposed Mechanistic Links
Abbreviations: PPCM, peripartum cardiomyopathy; LV, left ventricle; DCM, dilated cardiomyopathy; TTN, titin gene; sFlt-1, soluble fms-like tyrosine kinase-1.
PPCM is increasingly understood as a multifactorial disorder arising from the convergence of pregnancy-specific vascular stress and underlying myocardial susceptibility. Rather than representing a single-pathway disease, PPCM reflects the interaction between anti-angiogenic signaling, oxidative stress, inflammatory activation, prolactin cleavage, genetic predisposition, and the hemodynamic load of late gestation. These mechanisms collectively impair endothelial integrity, disrupt microvascular homeostasis, and promote maladaptive myocardial remodeling, ultimately leading to left ventricular systolic dysfunction. The integration of these interrelated pathways and their progression toward divergent clinical outcomes is illustrated in Figure 1.
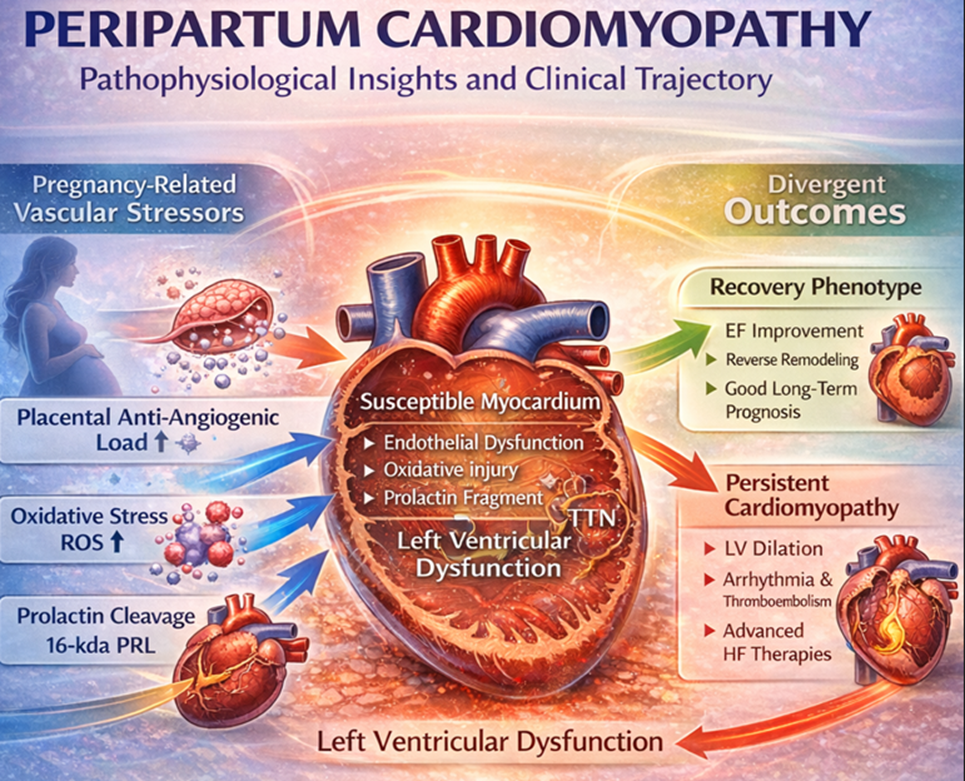
Figure 1: Schematic representation of the proposed multifactorial pathogenesis of peripartum cardiomyopathy (PPCM). Pregnancy-related vascular stressors, including placental anti-angiogenic load (elevated sFlt-1), oxidative stress, prolactin cleavage into the 16-kDa fragment, inflammatory activation, and hemodynamic overload, interact with an underlying susceptible myocardium, which may include genetic predisposition (e.g., TTN truncating variants). These converging pathways promote endothelial dysfunction, microvascular injury, oxidative damage, and maladaptive remodeling, culminating in left ventricular systolic dysfunction. The clinical trajectory diverges into two principal phenotypes: a recovery phenotype characterized by reverse remodeling and improvement in ejection fraction, and a persistent cardiomyopathy phenotype marked by continued LV dilation, arrhythmic and thromboembolic risk, and potential need for advanced heart failure therapies.
5.1 Prolactin Cleavage Hypothesis
One of the most influential mechanistic frameworks in PPCM is the prolactin cleavage hypothesis, which links pregnancy-associated oxidative stress to the generation of a biologically active, anti-angiogenic prolactin fragment that damages the cardiac microvasculature (28). In experimental models, heightened oxidative stress (including reduced cardiomyocyte antioxidant defenses) upregulates and activates proteases such as cathepsin D, promoting cleavage of full-length 23-kDa prolactin into a 16-kDa prolactin (16K PRL) fragment also referred to as a vasoinhibin-like fragment with potent vascular toxicity (28).
The 16-kDa prolactin fragment exerts anti-angiogenic and pro-apoptotic effects, with the endothelium emerging as a key early target (28,29). Mechanistically, 16K PRL induces endothelial dysfunction and promotes release of endothelial-derived signals that secondarily impair cardiomyocyte metabolism and survival. A central downstream mediator described in this pathway is microRNA-146a, which is induced in endothelial cells by 16K PRL and can be packaged into exosomes, thereby propagating maladaptive signaling to cardiomyocytes (10,29). These observations provide a molecular bridge between a circulating pregnancy hormone derivative and myocardial dysfunction.
From a vascular standpoint, the prolactin cleavage pathway offers a coherent explanation for microvascular injury in PPCM. Anti-angiogenic signaling and endothelial apoptosis can lead to capillary rarefaction, impaired myocardial perfusion, and microcirculatory dysfunction, creating a substrate for global LV systolic impairment even in the absence of epicardial coronary disease (10,28). In this model, PPCM is not solely a cardiomyocyte-centric disorder but a disease in which endothelial and microvascular dysfunction is upstream and potentially causal.
Clinically, this hypothesis has shaped the concept of mechanism-based therapy (e.g., prolactin suppression), but even without therapeutic extrapolation, it remains a cornerstone for interpreting PPCM as a syndrome driven by oxidative stress → prolactin cleavage → endothelial/microvascular injury → LV dysfunction (10,28,29).
5.2 Angiogenic Imbalance
A second, highly compelling pathophysiologic framework in PPCM is the angiogenic imbalance hypothesis, which proposes that late pregnancy is characterized by a physiologic shift toward an anti-angiogenic state, and that excessive or poorly compensated anti-angiogenic signaling can precipitate myocardial dysfunction in susceptible women (30). In this model, PPCM is conceptualized as, at least in part, a vascular/microvascular disease, where impaired angiogenic signaling compromises myocardial capillary integrity and perfusion, culminating in global LV systolic dysfunction (30).
A central mediator is soluble fms-like tyrosine kinase-1 (sFlt-1), a circulating decoy receptor that binds and neutralizes VEGF and PlGF, thereby suppressing pro-angiogenic signaling (31). sFlt-1 levels rise in late gestation and fall rapidly after delivery, strongly implicating the placenta as the dominant source of this anti-angiogenic factor (31). Importantly, sFlt-1 is markedly elevated in preeclampsia and tends to be higher with greater placental mass (e.g., multiple gestation), providing a biologically coherent explanation for the epidemiologic overlap between hypertensive pregnancy disorders and PPCM (30,31).
Human and translational data support clinical relevance of this pathway. In a landmark study, women with PPCM demonstrated abnormally elevated circulating sFlt-1, and experimental exposure to sFlt-1 produced cardiac dysfunction in murine models, particularly when cardiac angiogenic reserve was impaired (30). In the multicenter IPAC cohort, circulating sFlt-1 (and other vascular mediators) showed associations with symptom severity and adverse clinical events, reinforcing the concept that angiogenic signaling may influence phenotype and outcomes, even if single time-point measurements do not fully capture the dynamic biology of the peripartum period (32). Complementary work in recovered PPCM patients also suggested a persisting “angiogenic signature,” raising the possibility that residual vascular vulnerability may contribute to relapse risk in subsequent pregnancies (33).
Collectively, these data support a mechanistic chain linking placental anti-angiogenic output (sFlt-1) to systemic endothelial dysfunction and impaired myocardial microvascular homeostasis, thereby providing a plausible bridge between pregnancy-specific biology and cardiomyopathy (30–33).
5.3 Oxidative Stress and Inflammation
Oxidative stress represents a central upstream trigger in several mechanistic models of PPCM. Late pregnancy is characterized by heightened metabolic demand and increased generation of reactive oxygen species (ROS). In susceptible individuals, inadequate antioxidant defense may result in excessive oxidative signaling within cardiomyocytes and endothelial cells (27). Experimental data demonstrate that impairment of cardiomyocyte protective pathways particularly STAT3 signaling can enhance oxidative stress and sensitize the myocardium to injury in the peripartum setting (27).
ROS excess is not merely a biochemical epiphenomenon. Oxidative stress promotes protease activation, mitochondrial dysfunction, and disruption of nitric oxide signaling, all of which contribute to microvascular instability and myocardial contractile impairment (27,34). Importantly, oxidative stress is mechanistically linked to the prolactin cleavage pathway discussed earlier, creating a pathophysiologic bridge between hormonal, vascular, and inflammatory cascades.
Parallel to oxidative stress, inflammatory activation has been documented in PPCM. Elevated circulating cytokines including tumor necrosis factor-α (TNF-α), interleukin-6 (IL-6), and interferon-γ have been reported in affected patients compared with healthy postpartum controls (34,35). Although inflammation is not unique to PPCM and may accompany advanced heart failure of various etiologies, the peripartum immune milieu may amplify maladaptive myocardial responses.
At the cellular level, oxidative and inflammatory signaling converge on pathways leading to myocardial apoptosis. Experimental models demonstrate increased cardiomyocyte apoptosis in PPCM, mediated in part by oxidative stress–dependent signaling and microvascular dysfunction (27,36). Apoptotic cell loss contributes to impaired contractile function and adverse remodeling, particularly when compensatory angiogenic responses are insufficient.
Taken together, oxidative stress and inflammatory activation are not isolated phenomena but interdependent processes that amplify endothelial injury, microvascular compromise, and cardiomyocyte loss. In contemporary conceptual models, PPCM emerges from the intersection of angiogenic imbalance, oxidative stress, and inflammatory signaling, culminating in global systolic dysfunction.
5.4 Genetic Susceptibility
Genetic susceptibility is now recognized as a major contributor to PPCM, supporting the concept that pregnancy can act as a potent physiologic “stress test” that unmasks latent cardiomyopathy in predisposed women. The strongest evidence comes from studies demonstrating a substantial burden of pathogenic variants overlapping with dilated cardiomyopathy (DCM), particularly in genes involved in sarcomeric structure, cytoskeletal integrity, and protein quality control (13,37).
Titin (TTN) truncating variants
Among implicated genes, titin (TTN) truncating variants (TTNtv) represent the most frequent genetic finding. In a landmark sequencing study, women with PPCM showed a TTNtv burden comparable to that seen in idiopathic DCM, reinforcing the idea of shared genetic architecture (13). Importantly, TTNtv carriers may exhibit more persistent LV dysfunction and less complete recovery, although genotype–phenotype correlations can vary between cohorts and are influenced by clinical context and timing of assessment (13,37).
Overlap with dilated cardiomyopathy genes
Beyond TTN, variants in additional DCM-associated genes (e.g., DSP, FLNC, BAG3, VCL, among others) have been reported in PPCM cohorts, further supporting a shared genetic substrate (37). This overlap reframes PPCM from a purely pregnancy-induced entity to a syndrome that, in a meaningful subset of patients, reflects pregnancy-triggered expression of an underlying cardiomyopathy genotype (13,37).
Familial clustering and clinical implications
Familial clustering of PPCM and co-occurrence of PPCM/DCM within families have been described, consistent with inherited susceptibility (37). On this basis, contemporary expert commentary increasingly argues that genetic testing should be considered in women with PPCM, particularly those with severe presentations, persistent LV dysfunction, recurrence, or a relevant family history both for patient counseling and cascade screening of relatives (38). While genetic testing is not required for diagnosis, it is becoming increasingly relevant for long-term risk stratification and reproductive counseling.
5.5 Autoimmune and Viral Hypotheses
Beyond angiogenic and oxidative mechanisms, autoimmune and viral hypotheses have long been proposed to explain a subset of PPCM cases. These models are largely rooted in observations of inflammatory infiltrates, viral genomes in myocardial tissue, and circulating autoantibodies in affected women. However, the strength of evidence varies, and causality remains debated.
Myocarditis Association
Endomyocardial biopsy studies have reported histologic features consistent with myocarditis in a subset of patients with PPCM (39). Viral genomes particularly parvovirus B19 and human herpesvirus 6 have been detected in some myocardial samples, suggesting that viral infection may act as a trigger in susceptible individuals (40). However, viral genome detection lacks specificity and is not unique to PPCM, limiting its etiologic conclusiveness.
Cardiac magnetic resonance imaging studies have demonstrated inflammatory patterns, including myocardial edema and late gadolinium enhancement, in selected PPCM cohorts (41). Nevertheless, these findings are not universal and often do not conform to classic acute viral myocarditis patterns.
Autoantibodies
Elevated circulating cardiac autoantibodies, including those targeting β1-adrenergic receptors, have been identified in women with PPCM (42). Such antibodies may interfere with adrenergic signaling and contribute to myocardial dysfunction. However, similar autoantibody profiles are observed in other forms of dilated cardiomyopathy, and their presence does not establish primary autoimmune causation.
Taken together, viral and autoimmune mechanisms may contribute to myocardial injury in selected patients, but current evidence supports a multifactorial disease model rather than classification of PPCM as a primary inflammatory cardiomyopathy.
5.6 Hemodynamic Stress of Pregnancy
Pregnancy imposes a predictable but substantial hemodynamic load on the maternal cardiovascular system. In healthy pregnancies, these adaptations are usually well tolerated; in predisposed women, however, they may function as the final “stress test” that exposes limited cardiac reserve and contributes to PPCM expression and progression (43,44).
Volume overload is a central feature. Maternal plasma volume expands progressively across gestation (often on the order of ~40–50%), increasing venous return and ventricular preload (44,45). This is accompanied by parallel changes in renal sodium/water handling and neurohormonal signaling that maintain the expanded circulating volume state.
In parallel, cardiac output rises markedly, driven by increases in both stroke volume and heart rate. Cardiac output typically increases early and remains elevated through mid–late pregnancy, reflecting the combined effects of reduced systemic vascular resistance and increased metabolic demand (43–45). These changes peak around the late second to third trimester and then shift rapidly postpartum, when autotransfusion from uterine involution and mobilization of extracellular fluid can transiently increase preload further (43,44).
Under normal conditions, the LV accommodates these demands through physiologic remodeling mild chamber enlargement and/or increased wall thickness with preserved systolic function. In PPCM-susceptible women, the hypothesis is that this adaptive remodeling fails (or becomes maladaptive), leading to disproportionate dilation, rising wall stress, and progressive systolic impairment especially when superimposed on angiogenic imbalance, oxidative stress, and/or genetic vulnerability (43,44). Thus, hemodynamic stress is best understood not as a sole cause of PPCM, but as a powerful amplifier that interacts with pregnancy-specific molecular pathways. The principal mechanistic pathways implicated in PPCM and their cellular and clinical consequences are integrated in Table 2.
| Mechanism | Key Mediator | Cellular Effect | Clinical Consequence |
|---|---|---|---|
| Prolactin cleavage pathway | 16-kDa prolactin fragment | Endothelial apoptosis, miR-146a activation | Microvascular dysfunction |
| Angiogenic imbalance | Elevated sFlt-1 | VEGF inhibition, capillary rarefaction | Global LV systolic dysfunction |
| Oxidative stress | Reactive oxygen species (ROS), reduced STAT3 | Mitochondrial injury, apoptosis | Contractile impairment |
| Inflammatory activation | TNF-α, IL-6 | Myocyte injury, remodeling | Delayed recovery |
| Genetic susceptibility | TTN, DSP, FLNC, etc. | Sarcomeric and cytoskeletal dysfunction | Persistent LV dysfunction |
| Hemodynamic stress of pregnancy | Increased preload and cardiac output | Wall stress, maladaptive remodeling | Decompensation in predisposed myocardium |
Table 2. Integrated Pathophysiological Mechanisms in Peripartum Cardiomyopathy
Abbreviations: PPCM, peripartum cardiomyopathy; LV, left ventricle; VEGF, vascular endothelial growth factor; sFlt-1, soluble fms-like tyrosine kinase-1; ROS, reactive oxygen species; STAT3, signal transducer and activator of transcription 3; TNF-α, tumor necrosis factor-alpha; IL-6, interleukin-6; TTN, titin gene; DSP, desmoplakin; FLNC, filamin C; miR-146a, microRNA-146a.
6.1 Symptoms
The clinical presentation of PPCM most commonly mirrors new-onset HF developing in late pregnancy or the early postpartum period, and symptoms are frequently misattributed to “normal” pregnancy-related discomfort unless they are progressive or severe (9,10).
Dyspnea is the most frequent complaint, ranging from exertional shortness of breath to dyspnea at rest as congestion worsens (9,10). Many patients also report orthopnea, reflecting pulmonary venous congestion and elevated left-sided filling pressures; this may manifest as the need for multiple pillows or inability to lie flat (9,10). Peripheral edema is common and can be challenging to interpret in pregnancy, but disproportionate swelling especially if rapidly progressive or accompanied by respiratory symptoms should raise suspicion for cardiac decompensation rather than physiologic edema alone (9,10). Fatigue is also prominent and often out of proportion to gestational expectations, particularly when associated with reduced exercise tolerance or presyncope (9,10).
Clinically, the key is the pattern: symptoms that are new, worsening, or clearly disproportionate for gestational stage especially in the postpartum period should prompt immediate cardiovascular evaluation and echocardiography (9,10).
6.2 Signs
On physical examination, PPCM typically presents with findings of congestive HF, and the most important clue is objective evidence of volume overload rather than “normal pregnancy physiology” (9,10).
Pulmonary congestion may be suggested by tachypnea, hypoxemia, and bibasilar crackles/rales, and in more advanced cases, signs of frank pulmonary edema can be present (9,10). Peripheral signs of congestion such as elevated jugular venous pressure, hepatomegaly, and rapid weight gain may coexist, especially postpartum when intravascular volume shifts can be abrupt (9,10).
An S3 gallop is a classic sign of increased ventricular filling pressures and impaired systolic function; when present in a symptomatic peripartum patient, it should be treated as a red flag rather than a benign “pregnancy finding” (9,10). Additional findings can include tachycardia, cool extremities, narrow pulse pressure, and hypotension in severe decompensation.
Cardiomegaly may be appreciated clinically (displaced apical impulse) and is often supported by imaging (e.g., chest radiography showing an enlarged cardiac silhouette and pulmonary vascular congestion), though definitive structural assessment should rely on echocardiography (9,10). Notably, cardiomegaly is neither necessary nor sufficient for diagnosis, but when coupled with congestion it strengthens suspicion for PPCM.
6.3 Severe Presentations
Although many patients present with “typical” HF symptoms, PPCM can also declare itself through life-threatening complications, particularly in the early postpartum period when abrupt volume shifts and neurohormonal changes may unmask limited cardiac reserve (9,10,46).
Cardiogenic shock is the most dramatic presentation and reflects profound LV systolic failure with inadequate end-organ perfusion. Clinically, this may manifest as hypotension, cool extremities, oliguria, altered mental status, and rising lactate. In contemporary guidance documents, PPCM with shock is treated as a time-critical emergency requiring rapid escalation to inotropes/vasopressors and when needed mechanical circulatory support (e.g., ECMO or temporary LV support), ideally in experienced centers (46).
Arrhythmias can occur across the disease spectrum and include atrial fibrillation/flutter (AF), nonsustained or sustained ventricular tachycardia (VT), and in rare cases sudden cardiac arrest. Arrhythmic risk is generally higher in women with severely reduced LVEF, marked ventricular dilation, or ongoing myocardial injury, and it influences monitoring intensity and device decision-making during recovery (4,46). Because LV function may improve substantially with optimized therapy, many expert pathways emphasize individualized timing for ICD consideration and the potential bridging role of wearable defibrillators in selected high-risk patients (4,46).
Thromboembolism is a particularly important severe complication in PPCM, driven by the combination of postpartum hypercoagulability, low-flow states with severe LV dysfunction, and potential LV thrombus formation. Both arterial and venous thromboembolic events have been reported, including stroke and systemic embolization (47). Contemporary reviews emphasize maintaining a low threshold to evaluate for LV thrombus (especially with markedly reduced LVEF) and to consider anticoagulation when risk is high, balancing bleeding risk in the peripartum setting (4,47).
Overall, these severe presentations are not “edge cases” they are the complications we’re trying to prevent with early recognition, prompt echocardiography, and aggressive HF management (9,10,46).
Laboratory evaluation in PPCM primarily supports HF diagnosis, risk stratification, and mechanistic phenotyping. Natriuretic peptides (BNP and NT-proBNP) are typically elevated and are particularly useful in distinguishing pathological HF from physiological dyspnea and edema of pregnancy. Higher baseline NT-proBNP levels have been associated with reduced likelihood of LV recovery and worse outcomes (49,51). Cardiac troponin may be mildly elevated, reflecting myocardial injury; importantly, troponin T positivity has been associated with persistent LV systolic dysfunction in PPCM cohorts, suggesting prognostic value in selected patients (50). Nevertheless, troponin lacks disease specificity and should prompt evaluation for alternative diagnoses such as myocarditis or ischemia when markedly elevated. Although prolactin cleavage is central to pathophysiological models, routine serum prolactin levels are not clinically useful, as standard assays do not measure the pathogenic 16-kDa prolactin fragment (28). Inflammatory markers may be elevated but generally correlate with HF severity rather than providing diagnostic specificity (35,36). Emerging biomarkers include microRNAs such as miR-146a, implicated in endothelial–cardiomyocyte signaling (29), and angiogenic mediators such as sFlt-1 and relaxin-2, which have been associated with myocardial dysfunction and recovery patterns (30–32). Currently, natriuretic peptides and troponin remain the most clinically actionable biomarkers, while angiogenic and microRNA profiles represent promising but still investigational tools (48).
8.1 Echocardiography
TTE is the cornerstone imaging modality in PPCM because it simultaneously establishes the diagnosis, quantifies severity, and helps anticipate complications. Typical findings include variable LV dilatation with reduced LVEF and global hypokinesia, although LV enlargement is not mandatory and some patients present with only mild chamber dilatation despite marked systolic impairment (9,10). In contemporary prospective data (IPAC), baseline echocardiography particularly the degree of LV systolic dysfunction and LV size strongly predicted likelihood of recovery, underscoring the prognostic importance of careful quantification (52). Echocardiography should also evaluate RV involvement, which is not rare and has been associated with worse clinical status and outcomes in PPCM cohorts; therefore, routine assessment of RV size and function (e.g., TAPSE, RV fractional area change, tissue Doppler S′) is clinically meaningful (53). Finally, echo must actively screen for LV thrombus, especially in patients with severely reduced LVEF or marked LV dilatation, given the peripartum hypercoagulable milieu and the non-trivial embolic risk; contrast-enhanced echo or CMR can be considered when image quality is limited or suspicion remains high (10,54).
8.2 Cardiac Magnetic Resonance
CMR is a valuable adjunct in PPCM when echocardiography is inconclusive, when myocarditis/Takotsubo is in the differential diagnosis, or when advanced phenotyping is desired. CMR can detect myocardial edema (typically via T2-based techniques and/or T2 mapping), which when present supports an acute injury/inflammatory component, while also helping to contextualize symptoms and troponin signals without assuming PPCM is “primary myocarditis” (55,59). LGE provides a noninvasive readout of focal fibrosis/necrosis; importantly, LGE appears uncommon in many PPCM cohorts, suggesting that extensive irreversible focal myocardial injury is not a universal feature of the disease (56). When LGE is present, patterns are generally non-ischemic (e.g., mid-wall/subepicardial) rather than infarct-like, and some contemporary datasets indicate that LGE positivity may correlate with worse outcomes or incomplete recovery, making it potentially useful for risk stratification in selected patients (57,58). Beyond edema/LGE, modern CMR enables tissue characterization with native T1/T2 mapping and extracellular volume (ECV) assessment, allowing detection of diffuse myocardial abnormalities even when conventional imaging looks borderline; recent work has explored the diagnostic/prognostic value of such multiparametric CMR profiling in acute PPCM (58).
8.3 Advanced Imaging
Beyond conventional LVEF assessment, myocardial strain imaging particularly 2D speckle-tracking–derived GLS can detect myocardial dysfunction earlier and more sensitively than LVEF in PPCM, and it adds meaningful prognostic information when evaluating recovery. Several cohorts show that worse GLS at presentation is associated with a lower likelihood of subsequent LV functional recovery, even after accounting for baseline LVEF, supporting GLS as a complementary marker of myocardial impairment rather than a redundant metric (60). Strain may also remain abnormal despite apparent normalization of LVEF, suggesting “subclinical” residual dysfunction that could be relevant for counseling, follow-up intensity, and subsequent pregnancy risk discussions (61). For assessment of myocardial recovery, advanced imaging is most useful when applied longitudinally: serial echocardiography (often at ~6 weeks, 3–6 months, and 12 months depending on severity) should track LVEF, LV dimensions, and where available GLS to better characterize the trajectory of remodeling and recovery (52). Recent work has also moved toward integrating clinical variables with imaging parameters into practical prediction tools for LV recovery, highlighting the growing role of imaging beyond diagnosis toward risk stratification and individualized follow-up planning (62).
9.1 Acute Heart Failure Treatment
Acute management of PPCM follows standard principles for HFrEF ejection fraction, with modifications based on pregnancy status. Intravenous loop diuretics are indicated for pulmonary and systemic congestion, with cautious titration during pregnancy to avoid excessive preload reduction and compromised uteroplacental perfusion (46,63). Vasodilator therapy can be used when blood pressure permits; hydralazine and nitrates are appropriate during pregnancy to reduce afterload, whereas renin–angiotensin system inhibitors are contraindicated before delivery (63). Beta-blockers, particularly β1-selective agents such as metoprolol, are introduced once hemodynamic stability is achieved and play a key role in reverse remodeling and arrhythmia prevention (46,63). ACE inhibitors and ARBs are contraindicated during pregnancy due to fetotoxicity, but postpartum initiation of ACE inhibitors is recommended in women with persistent LV dysfunction as part of guideline-directed medical therapy; this approach is supported by contemporary PPCM reviews and heart failure guidelines (3,4,10).
9.2 Pregnancy-Safe Therapies
In pregnant patients with PPCM who require pharmacologic stabilization, therapy is centered on agents with the best-established maternal–fetal safety profiles while avoiding fetotoxic RAAS blockade. For afterload reduction and symptomatic improvement, hydralazine and nitrates (e.g., isosorbide dinitrate/mononitrate) are widely used pregnancy-compatible options, particularly when blood pressure is adequate and congestion is being treated concurrently; this combination is commonly recommended as a practical alternative to ACE inhibitors/ARBs during pregnancy (64,65). Beta-1 selective blockers (most often metoprolol) can be used once the patient is hemodynamically stable to support reverse remodeling and reduce arrhythmic risk; among beta-blockers, β1-selective agents are generally preferred, while atenolol is typically avoided given stronger associations with fetal growth restriction in prior literature (64–66). Because beta-blockers as a class can be associated with small-for-gestational-age risk and neonatal bradycardia/hypoglycemia, obstetric collaboration and fetal growth surveillance are appropriate when prolonged therapy is required (66). Overall, hydralazine–nitrate afterload reduction plus a β1-selective blocker titrated carefully forms the backbone of “pregnancy-safe” HF pharmacotherapy until delivery allows transition to standard guideline-directed regimens.
9.3 Anticoagulation
Anticoagulation in PPCM is driven by the “perfect storm” of postpartum hypercoagulability, severe LV systolic dysfunction with low-flow states, and a non-trivial risk of LV thrombus and systemic embolism. Clear indications include documented LV thrombus, atrial fibrillation/flutter, prior thromboembolism, or another standard indication for therapeutic anticoagulation; beyond these, many experts also consider prophylactic/therapeutic anticoagulation in women with severely reduced LVEF, even if no thrombus is seen, because thrombi can be missed on non-contrast echo and embolic events may be catastrophic (47,67). The commonly cited LVEF thresholds differ by society: summaries of guidance note that the AHA suggests considering anticoagulation when LVEF is <30>
9.4 Bromocriptine Therapy
Bromocriptine (a dopamine-D2 agonist) is the most widely discussed disease-specific therapy in PPCM because it targets the prolactin-cleavage pathway: oxidative stress can promote generation of the toxic 16-kDa prolactin fragment, which drives endothelial dysfunction and microvascular injury; blocking prolactin release is therefore proposed to reduce downstream vascular–myocardial damage (28). Clinical evidence began with a proof-of-concept pilot study in acute severe PPCM suggesting improved LV recovery when bromocriptine was added to standard HF therapy (68). Subsequent randomized data comparing short vs longer bromocriptine regimens (on top of standard therapy) reported high rates of LV recovery and low morbidity/mortality, though trials have been relatively small and heterogeneity in background therapy and disease severity limits certainty about hard endpoints (69). A key practical point is safety: bromocriptine has been associated with thrombotic events in postpartum settings, and PPCM itself carries heightened thromboembolic risk due to hypercoagulability and low-flow states. For this reason, contemporary expert statements recommend that bromocriptine should be accompanied by anticoagulation (at least prophylactic-dose heparin, with escalation based on LV function/thrombus/AF and overall risk) to mitigate thrombosis risk (4).
9.5 Mechanical Circulatory Support
In fulminant PPCM complicated by cardiogenic shock or refractory hypoxemia, temporary mechanical circulatory support (MCS) can be lifesaving as a bridge to recovery, durable LVAD, or transplantation. Device selection is typically guided by shock phenotype (left-, right-, or biventricular failure), severity of hypoxemia, and the expected time to recovery. IABP may be considered in selected patients with predominantly LV failure and preserved right-sided function, but its hemodynamic augmentation is modest and it is increasingly viewed as an adjunct or a temporizing step rather than definitive support in severe shock. Impella provides active LV unloading and can be used as a bridge to myocardial recovery or to escalation (e.g., durable LVAD) in PPCM; published PPCM-focused series and reviews describe successful stabilization and bridging with microaxial pumps in severe LV dysfunction (70). VA-ECMO is preferred when there is profound cardiogenic shock with end-organ hypoperfusion and/or combined cardiopulmonary failure; registry-level data in PPCM suggest meaningful survival and a substantial rate of successful weaning, supporting ECMO as a viable bridge strategy in carefully selected patients (71). When recovery does not occur or when repeated decompensation persists, escalation to durable LVAD (and, rarely, transplantation) becomes appropriate; contemporary cohorts of PPCM patients requiring advanced therapies underline that durable support can be an effective bridge-to-transplant or bridge-to-decision, but also highlight the importance of early referral to experienced centers (46,72).
9.6 Heart Transplantation
Heart transplantation (HT) is a definitive therapy for women with PPCM who develop end-stage HF refractory to optimal medical therapy and appropriate mechanical circulatory support. Transplantation is generally considered when severe LV dysfunction persists despite maximal treatment, when patients remain dependent on durable support, or when progressive end-organ dysfunction develops (73).
Contemporary registry data from the United Network for Organ Sharing (UNOS) demonstrate that PPCM accounts for a small but consistent proportion of heart transplants in young women (73,74). Earlier analyses suggested that PPCM recipients may experience higher early post-transplant morbidity, including rejection and sensitization, compared with other non-ischemic cardiomyopathies (74). However, more recent nationwide analyses indicate that long-term survival after transplantation for PPCM has improved substantially in the modern era, with 5-year survival rates exceeding 65% and approaching outcomes observed in other cardiomyopathy populations when adjusted for baseline severity (73).
Overall, although most women with PPCM recover partially or completely, heart transplantation remains an effective and lifesaving option for the minority with irreversible advanced HF.
PPCM can deteriorate quickly, and its major complications cluster around pump failure, electrical instability, thrombosis, and incomplete recovery. Cardiogenic shock represents the most acute end of the spectrum and requires immediate escalation (inotropes/vasopressors, rapid consideration of temporary mechanical circulatory support, and referral to experienced centers), because delayed support worsens end-organ injury and survival (4,46). Ventricular arrhythmias may occur in the setting of severe LV dysfunction and myocardial instability; they range from non-sustained VT to sustained VT/VF, and management often includes aggressive GDMT optimization, correction of triggers, and individualized consideration of temporary protection (e.g., wearable defibrillator) while awaiting potential recovery (3,4,46). Sudden cardiac death risk is highest in those with markedly reduced LVEF and malignant ventricular arrhythmias; a key nuance in PPCM is that recovery can be substantial, so permanent ICD decisions are typically deferred until recovery trajectory is clearer unless secondary prevention indications exist (3,4,46). Thromboembolism is a particularly important PPCM complication because the postpartum period is intrinsically hypercoagulable and severe LV dysfunction creates low-flow conditions; LV thrombus and systemic embolism (including stroke) are therefore real threats, especially with very low LVEF and/or LV dilation, and this risk underpins guideline discussions about anticoagulation thresholds and careful thrombus surveillance (3,4). Finally, persistent LV dysfunction (failure to recover) is the complication that “makes everything else worse”: it amplifies arrhythmic and thrombotic risk, increases rehospitalization, and drives progression to advanced therapies; prospective North American data show that baseline severity (very low LVEF and larger LV dimensions) strongly predicts incomplete recovery at follow-up (52).
Left ventricular recovery in PPCM is highly heterogeneous, but when improvement occurs it most commonly unfolds within the first 3–6 months after diagnosis. Prospective North American data from the IPAC cohort demonstrated that most women who ultimately recover exhibit substantial LVEF improvement within six months, with slower incremental gains up to 12 months (26,52). Early trajectory matters: meaningful improvement during the first 2–3 months strongly predicts complete recovery at one year, whereas minimal early change often signals persistent dysfunction (26,52). Although late recovery beyond 12 months has been reported, it is uncommon; therefore, structured imaging follow-up during the first year is critical for risk stratification.
Recovery rates vary across cohorts and definitions. Complete recovery is generally defined as LVEF normalization (≥50–55%), while partial recovery refers to persistent mild-to-moderate systolic dysfunction. Contemporary data suggest that approximately 50–70% of women achieve full recovery within 6–12 months in high-resource settings (26,52). However, regional disparities are pronounced. African cohorts have historically reported lower recovery rates and higher residual dysfunction, likely reflecting delayed presentation and limited access to advanced therapies (20,75). Importantly, normalization of LVEF does not necessarily equate to complete myocardial recovery. Persistent abnormalities in global longitudinal strain have been documented even in women with restored EF, indicating subtle residual myocardial injury (61). This nuance is clinically relevant when counseling patients regarding long-term risk and subsequent pregnancy.
Baseline disease severity remains the most powerful predictor of outcome. Very low LVEF at presentation particularly <30>
Despite therapeutic advances, approximately 30–50% of women have persistent LV systolic dysfunction at one year (52,75). Persistent dysfunction carries important long-term implications, including increased risk of heart failure progression, ventricular arrhythmias, thromboembolism, and need for advanced therapies (4,52). Even in women with apparent EF normalization, relapse risk in subsequent pregnancy is not negligible, and it is markedly higher in those with residual LV impairment (77). Thus, recovery should be interpreted along a continuum rather than as a binary endpoint.
Mortality in PPCM demonstrates substantial geographic variability. In high-income settings, contemporary 1-year mortality is generally below 5–10% (52,75). In contrast, mortality in certain sub-Saharan African cohorts has historically exceeded 10–15%, underscoring the impact of delayed diagnosis and limited access to advanced HF therapies (20,75). Long-term survival is closely tied to recovery status: women who achieve sustained normalization of LV function often have outcomes approaching those of age-matched populations, whereas those with chronic systolic dysfunction remain at increased risk for progressive HF and sudden cardiac death (26,52). Encouragingly, improvements in guideline-directed medical therapy, risk stratification, mechanical circulatory support strategies, and transplantation outcomes have contributed to better survival in recent decades (3,26,73).
The central clinical reality is this: PPCM is a bifurcating disease. Early recovery predicts an excellent long-term trajectory. Persistent dysfunction predicts chronic cardiomyopathy physiology with lifelong implications. Recognizing which path a patient is on early and objectively is the key determinant of prognosis.
Subsequent pregnancy after PPCM remains one of the most clinically challenging and emotionally charged aspects of long-term management. The central determinant of risk is left ventricular (LV) recovery status prior to conception. Recurrence of heart failure or deterioration in LV function has been consistently documented, and the magnitude of risk is strongly tied to baseline myocardial reserve at the time of the new pregnancy (77).
The risk of recurrence varies across cohorts but is clearly non-negligible. In women with persistent LV dysfunction prior to a subsequent pregnancy, relapse rates are high and maternal morbidity and mortality increase substantially (77). Even in women whose LVEF normalized after the index PPCM episode, recurrence of LV dysfunction has been reported in approximately 20–30% of cases, although outcomes are generally more favorable than in those with residual dysfunction (77,78). Importantly, EF normalization does not guarantee complete myocardial recovery; subtle structural or strain abnormalities may persist and may partially explain relapse risk (61). Thus, prior “recovery” should be interpreted cautiously and not equated with zero risk.
Impact of prior LV recovery status is the single most powerful prognostic variable. Women with persistent LV dysfunction (particularly LVEF <50>
Counseling strategies must therefore be individualized and grounded in objective cardiac assessment. Women with persistent LV dysfunction should be strongly advised against future pregnancy due to significant maternal risk (2,77). For women with normalized LV function, counseling should include transparent discussion of relapse risk, the possibility of irreversible deterioration, and the need for intensive surveillance. Shared decision-making is essential, ideally within a multidisciplinary cardio-obstetrics team. Preconception evaluation should include comprehensive echocardiography (including strain where available), biomarker assessment, and optimization of guideline-directed medical therapy before any medication adjustments are made for pregnancy (2,3,4).
Contraception counseling is not optional; it is a core component of PPCM follow-up. Effective contraception is particularly critical in women with persistent LV dysfunction. Estrogen-containing contraceptives may increase thromboembolic risk and are generally avoided in women with significant LV impairment. Long-acting reversible contraception such as intrauterine devices (IUDs) or subdermal progestin implants are typically preferred due to high efficacy and favorable cardiovascular safety profiles (2,79). Permanent sterilization may be discussed in women with severe persistent cardiomyopathy in whom pregnancy poses unacceptable risk. Importantly, contraceptive planning should begin early in the postpartum period to prevent unintended high-risk pregnancies.
If pregnancy occurs after PPCM, close monitoring is mandatory. Women with prior PPCM should be managed in specialized centers with coordinated cardiology and high-risk obstetrics care (3,4). Baseline echocardiography early in pregnancy should be followed by serial imaging commonly once per trimester and in the early postpartum period with additional assessments if symptoms emerge (2). Natriuretic peptides may assist in distinguishing physiologic dyspnea from early decompensation. Prompt initiation or adjustment of pregnancy-compatible HF therapy is essential at the first sign of deterioration. Postpartum monitoring is equally critical, as hemodynamic shifts and neurohormonal changes may precipitate late decompensation.
The practical takeaway is stark but empowering: subsequent pregnancy after PPCM is not uniformly contraindicated, but it is never routine. Pre-pregnancy LV function determines risk. Persistent dysfunction makes pregnancy high risk. Apparent recovery lowers but does not eliminate risk. Precision counseling, reliable contraception, and structured multidisciplinary surveillance are the tools that transform uncertainty into controlled risk management.
Risk stratification in PPCM hinges on early identification of patients who are likely to recover versus those who will follow a chronic cardiomyopathy trajectory. Among all variables studied, baseline LVEF remains the most powerful and reproducible prognostic marker. Prospective data from the IPAC study demonstrated that women presenting with LVEF <30>
Left ventricular end-diastolic diameter (LVEDD) adds structural context to systolic impairment. Increased LVEDD at presentation particularly ≥6.0 cm has been associated with lower probability of myocardial recovery (52). Larger LV size likely reflects more advanced remodeling and higher wall stress, which in turn reduces the likelihood of complete reverse remodeling. Contemporary predictive models derived from multinational registries integrate LV dimensions alongside LVEF to refine risk estimation (62). Importantly, LV dilatation does not need to be extreme to carry prognostic weight; even moderate enlargement in combination with low EF compounds risk.
Right ventricular (RV) dysfunction further identifies a more severe phenotype. CMR and echocardiographic studies demonstrate that RV involvement is not uncommon in PPCM and is associated with worse clinical status and reduced recovery rates (53). RV dysfunction likely reflects more diffuse myocardial injury and greater hemodynamic compromise. From a pathophysiologic perspective, biventricular involvement signals that the disease process extends beyond isolated LV contractile impairment and may portend a more protracted course.
Biomarkers provide complementary prognostic information. Elevated NT-proBNP levels at diagnosis correlate with disease severity and have been associated with lower likelihood of LV recovery and reduced event-free survival (49,51). Troponin positivity, even when modest, has been linked to persistent LV dysfunction in PPCM cohorts, suggesting that measurable myocardial injury at presentation carries prognostic implications (50). Angiogenic markers such as soluble Flt-1 and relaxin-2 have been associated with clinical outcomes in mechanistic studies, although their role in routine risk stratification remains investigational (32). Emerging data also suggest that inflammatory markers and oxidative stress–related mediators may correlate with severity, but they lack sufficient specificity for clinical decision algorithms (48).
Genetic markers represent an evolving frontier in risk stratification. Truncating variants in TTN and other DCM–associated genes are present in a meaningful subset of women with PPCM and appear to be associated with lower recovery rates and more persistent dysfunction (13,37). Contemporary genetic analyses suggest that pathogenic variants confer a phenotype resembling non-ischemic DCM, with pregnancy functioning as a physiological trigger rather than the sole cause (37). Identification of a pathogenic variant may therefore influence long-term follow-up intensity, family screening, and counseling regarding subsequent pregnancy risk. While genetic testing is not required for diagnosis, it is increasingly relevant in patients with severe presentation, incomplete recovery, or positive family history (37,38).
Taken together, effective risk stratification in PPCM integrates functional severity (baseline LVEF), structural remodeling (LVEDD), ventricular coupling (RV function), biochemical signals (natriuretic peptides and troponin), and genetic substrate. No single marker is sufficient alone; rather, risk emerges from the convergence of myocardial reserve, remodeling burden, and biological susceptibility. Early, structured, and multimodal assessment transforms PPCM from an unpredictable entity into a disease in which trajectory can be estimated and managed proactively. Key prognostic markers and high-risk indicators used in clinical risk stratification are summarized in Table 3.
| Parameter | High-Risk Indicator | Prognostic Implication |
|---|---|---|
| Baseline LVEF | <30> | Low likelihood of full recovery |
| LVEDD | ≥6.0 cm | Persistent remodeling and dysfunction |
| Right ventricular function | RV dysfunction present | Increased mortality and adverse events |
| NT-proBNP | Markedly elevated | Reduced recovery probability |
| Troponin | Positive at presentation | Persistent LV systolic dysfunction |
| Genetic profile | TTN truncating variant | Chronic DCM-like phenotype |
| Early recovery trajectory | Minimal EF improvement within 2–3 months | Poor 12-month outcome |
| Residual GLS abnormality | Abnormal strain despite normal EF | Subclinical myocardial vulnerability |
Table 3. Prognostic Markers and Risk Stratification Parameters in PPCM
Abbreviations: PPCM, peripartum cardiomyopathy; LVEF, left ventricular ejection fraction; LVEDD, left ventricular end-diastolic diameter; RV, right ventricle; NT-proBNP, N-terminal pro–B-type natriuretic peptide; EF, ejection fraction; GLS, global longitudinal strain; TTN, titin gene; DCM, dilated cardiomyopathy.
14.1 African Cohorts
PPCM demonstrates marked geographic and racial variability, with African and African-descended populations consistently exhibiting higher incidence and more severe clinical phenotypes. U.S. population-based analyses have shown that women of African ancestry present with lower baseline LVEF and experience higher rates of persistent LV dysfunction compared with other racial groups (11,18). Cohorts from sub-Saharan Africa further reveal elevated mortality and lower recovery rates, often associated with delayed presentation, higher prevalence of hypertensive disorders of pregnancy, anemia, and limited access to advanced heart failure therapies (5,20).
Importantly, the African PPCM phenotype appears to reflect an interaction between biological susceptibility and structural health determinants. Socioeconomic factors, healthcare infrastructure, and postpartum follow-up accessibility significantly influence outcomes. Therefore, risk stratification in these cohorts must extend beyond echocardiographic severity to include system-level determinants of care delivery (5,20).
14.2 TTN Mutation Carriers
Genetic susceptibility plays a substantial role in a meaningful subset of PPCM patients, with TTN truncating variants (TTNtv) representing the most frequently identified pathogenic mutations. Large sequencing studies have demonstrated that the burden of TTNtv in PPCM is comparable to that observed in dilated cardiomyopathy (DCM), supporting the concept that pregnancy may act as a physiological stressor unmasking latent genetic cardiomyopathy (13).
Expanded genotype–phenotype analyses suggest that carriers of TTNtv and other DCM-associated variants may exhibit lower rates of complete LV recovery and a higher likelihood of persistent systolic dysfunction (37). Although recovery is still possible in mutation carriers, the trajectory often resembles non-ischemic DCM rather than a purely pregnancy-limited syndrome. These findings have practical implications: genetic testing should be considered in patients with severe presentation, incomplete recovery, or family history of cardiomyopathy, both for individualized risk stratification and cascade screening (37,38).
14.3 Severe Early-Onset PPCM
Although traditionally defined as occurring in late pregnancy or early postpartum, PPCM may present earlier in gestation in selected patients. Early-onset cases often represent a more aggressive phenotype and require careful differentiation from unmasked dilated cardiomyopathy, myocarditis, or hypertensive heart disease (4,9,19).
In some early presentations, the hemodynamic stress of pregnancy interacts with heightened angiogenic imbalance or genetic predisposition, resulting in rapid deterioration of myocardial function. These patients frequently present with more severe LV dysfunction and may require earlier escalation of heart failure therapy (4,46). Because the diagnostic boundary between “true PPCM” and pregnancy-unmasked cardiomyopathy can be blurred in this context, systematic exclusion of alternative etiologies is critical.
14.4 PPCM with Persistent LV Dysfunction
Persistent LV systolic dysfunction beyond 6–12 months defines a high-risk PPCM subgroup with long-term implications. Prospective data indicate that women with incomplete recovery face increased risk of heart failure progression, ventricular arrhythmias, thromboembolic events, and need for advanced therapies (52). Persistent dysfunction transforms PPCM from an acute pregnancy-associated event into a chronic cardiomyopathy phenotype.
Management in this population requires long-term continuation of guideline-directed medical therapy, structured imaging surveillance, and individualized decisions regarding device therapy or advanced heart failure referral (4,46,73). Importantly, subsequent pregnancy carries substantial maternal risk in women with residual LV dysfunction and is generally discouraged (2,77). Effective and reliable contraception should therefore be addressed early and proactively in this subgroup.
Collectively, these special populations underscore that PPCM is not a uniform entity. African ancestry, genetic substrate, early aggressive presentation, and persistent LV dysfunction each represent distinct phenotypic modifiers that influence recovery trajectory, recurrence risk, and long-term prognosis. Distinct clinical phenotypes and special PPCM subgroups with their biological context and prognostic implications are summarized in Table 4.
15. Controversies and Knowledge Gaps
Despite major advances in mechanistic understanding and contemporary HF care, PPCM still has several unresolved “decision points” where practice varies substantially between centers and regions. The most debated issue remains whether bromocriptine should be used universally or selectively. While prolactin blockade is mechanistically attractive and is supported by small randomized studies plus observational datasets, the evidence base still struggles with limited sample sizes, heterogeneity in disease severity, variable background therapy, and inconsistent reporting of hard endpoints. Recent meta-analyses suggest bromocriptine added to standard care is associated with greater LVEF improvement and possibly better survival, but the certainty of evidence remains constrained by study design and residual confounding, keeping universal adoption controversial and pushing many clinicians toward a “high-risk phenotype–focused” approach rather than routine use for all PPCM patients (80,81). A related gap is defining the safest, most effective anticoagulation strategy when bromocriptine is used, given the postpartum prothrombotic milieu and historical concerns about thrombotic complications.
Another major uncertainty is the optimal duration of HF therapy once LV function recovers. Many patients demonstrate apparent normalization of LVEF within 6–12 months, but relapse can occur, and subclinical myocardial dysfunction (e.g., abnormal GLS despite normal LVEF) has been described. There is no universally accepted “stop rule” for GDMT in recovered PPCM, and prospective randomized withdrawal data are lacking. Current practice is therefore pragmatic: continue therapy longer in those with severe initial presentation, delayed/partial recovery, residual dilation, abnormal strain, or genetic predisposition yet the field still lacks validated criteria for safe de-escalation.
Device therapy is where PPCM’s reversibility collides with sudden death prevention. The timing of ICD implantation is controversial because many patients especially early in the course may recover enough to no longer meet standard primary-prevention thresholds. Observational evidence suggests that ICD therapy is used in PPCM, but outcomes and complication profiles are not well defined compared with other nonischemic cardiomyopathies, and “early ICD” risks over-treatment in a condition with meaningful recovery potential (82). Consequently, many centers delay definitive ICD decisions until LV recovery trajectory is clearer, typically after a period of optimized GDMT, but the exact timing threshold (3 months vs 6 months vs longer in PPCM specifically) remains unsettled and is a major knowledge gap.
Wearable cardioverter-defibrillators (WCDs) are often proposed as a bridge during this “recovery window,” but their role in PPCM is still debated. WCD rationale is intuitive provide temporary protection while awaiting improvement yet PPCM-specific data are limited and largely observational, and event rates vary by cohort severity and selection. Contemporary reviews and guideline-adjacent discussions support WCD use in temporarily high-risk patients who are not yet candidates for permanent ICD, but PPCM-focused prospective studies defining who truly benefits (and for how long) are still lacking (83). This leaves clinicians balancing theoretical protection against cost, adherence, and uncertain absolute benefit in lower-risk phenotypes.
Finally, genetic screening recommendations are evolving rapidly and remain inconsistent across practice settings. Sequencing studies demonstrate that a meaningful subset of PPCM shares a genetic architecture with dilated cardiomyopathy particularly TTN truncating variants supporting the concept that pregnancy can unmask latent genetic cardiomyopathy. Many experts now argue that genetic testing should be offered at least to women with severe presentation, incomplete recovery, recurrence, or relevant family history, because results may influence long-term surveillance, cascade screening, and counseling regarding subsequent pregnancy risk (37,38). However, uncertainties persist: which gene panels are optimal, how to interpret variants of uncertain significance in PPCM, how genetic results should concretely change management, and how to deliver equitable access to counseling and testing worldwide.
Overall, PPCM is a condition where reversibility is common enough to complicate “standard HF rules,” but risk is real enough that delaying decisions can be dangerous. The biggest gaps are not philosophical they are practical: better prospective trials for bromocriptine strategies, standardized criteria for GDMT duration and withdrawal, PPCM-specific arrhythmic risk models to guide ICD vs WCD decisions, and consensus pathways for genetic testing and downstream management.
16. International Guidelines and Consensus Statements
International guidance on PPCM largely derives from broader heart failure (HF) guidelines supplemented by pregnancy-specific consensus statements. Because PPCM lies at the intersection of advanced HF physiology and pregnancy-related hemodynamics, contemporary recommendations emphasize integration of standard HFrEF principles with maternal–fetal safety considerations (4,63).
With respect to HF management, guideline-directed medical therapy (GDMT) remains the backbone of treatment once delivery has occurred. ACE inhibitors (or ARBs when ACE inhibitors are not tolerated), beta-blockers, mineralocorticoid receptor antagonists, and diuretics are recommended in women with persistent LV systolic dysfunction postpartum, in line with contemporary HFrEF guidance (4). During pregnancy, however, renin–angiotensin system inhibitors and mineralocorticoid receptor antagonists are contraindicated due to fetotoxicity. Therefore, pregnancy-compatible regimens rely on loop diuretics for congestion, hydralazine–nitrate combinations for afterload reduction, and beta-1 selective beta-blockers once hemodynamic stability is achieved (2,63). In cases of cardiogenic shock, rapid escalation following advanced HF protocols including inotropes and mechanical circulatory support should be implemented in experienced centers (46).
Pregnancy-specific modifications are a central theme in guideline documents. The 2018 European Society of Cardiology (ESC) Guidelines on cardiovascular disease during pregnancy classify women with persistent LV dysfunction after PPCM as high-risk for maternal complications in future pregnancies and recommend strong counseling against subsequent gestation in those with incomplete recovery (2). Risk stratification using LVEF and clinical stability is emphasized before conception, and multidisciplinary cardio-obstetrics care is advised throughout pregnancy and delivery (2). Anticoagulation should be considered in women with severely reduced LVEF because of the combined prothrombotic postpartum state and low-flow ventricular physiology (2,4).
Postpartum follow-up protocols are explicitly addressed in expert consensus statements. Serial echocardiography is recommended to monitor LV recovery, typically at 3–6 months and again at 12 months, with continued surveillance in those with persistent dysfunction (4,46). Women who achieve apparent recovery require ongoing evaluation given the risk of relapse and late deterioration. Guideline discussions also emphasize structured counseling regarding contraception and future pregnancy risk as an essential component of longitudinal care (2).
Recommendations from the European Society of Cardiology particularly the Heart Failure Association (HFA) Study Group on PPCM highlight the importance of early diagnosis, standardized imaging, consideration of bromocriptine in selected high-risk cases (with concomitant anticoagulation), and referral to specialized centers when advanced therapies are required (4,46). The ESC framework underscores that PPCM management should not be siloed within obstetrics or cardiology alone; rather, it demands coordinated, multidisciplinary decision-making from diagnosis through long-term follow-up.
Collectively, international guidelines agree on core principles early recognition, pregnancy-adapted HF therapy, structured imaging surveillance, and individualized counseling but also acknowledge persistent evidence gaps, particularly regarding optimal duration of therapy, device timing, and genetic testing strategies. As prospective data expand, future updates are expected to refine these recommendations toward more phenotype-driven, precision-based care.
17. Future Directions
The future of PPCM management is likely to move beyond uniform HF algorithms toward phenotype-driven and biologically informed strategies. As mechanistic understanding deepens, precision medicine approaches are emerging as a logical next step. Contemporary position statements emphasize that PPCM is not a single-pathway disease but rather a convergence of angiogenic imbalance, oxidative stress, inflammation, and genetic susceptibility (4). Integrating clinical severity (LVEF, LV dimensions), biomarker profiles, and genetic background may allow identification of subgroups with distinct recovery trajectories and therapeutic responsiveness. The long-term goal is not merely to treat LV dysfunction, but to anticipate which biological axis predominates in a given patient (4).
Targeted modulation of the anti-angiogenic pathway represents one of the most promising translational avenues. The discovery that excess soluble fms-like tyrosine kinase-1 (sFlt-1) and related angiogenic imbalance can precipitate myocardial dysfunction provides a coherent mechanistic bridge between placental biology and cardiomyopathy (30). While disease-specific therapies such as prolactin blockade have been explored, definitive evidence that pathway-targeted interventions improve hard outcomes remains limited, and larger trials are needed to define which phenotypes benefit most (4,69).
Gene-based risk assessment is another rapidly expanding frontier. Large sequencing efforts demonstrate that a meaningful subset of PPCM patients carry truncating variants in TTN or other dilated cardiomyopathy–associated genes, supporting the concept that pregnancy can unmask latent genetic cardiomyopathy rather than create de novo disease in all cases (37). In the future, genotype-informed counseling may guide intensity of surveillance, duration of heart failure therapy, and risk discussions regarding subsequent pregnancy, but standardization of testing strategies and interpretation frameworks remains an important gap (4,37).
Large randomized clinical trials remain an urgent need. Many current management decisions including bromocriptine use, duration of GDMT after recovery, timing of ICD implantation, and anticoagulation thresholds are based on relatively small randomized studies, observational cohorts, or expert consensus (4,69). Adequately powered multicenter randomized trials are essential to determine whether disease-specific interventions meaningfully alter endpoints such as mortality, transplantation, arrhythmic events, and recurrent dysfunction (4).
Global PPCM registries represent the structural backbone for this next phase. The ESC EURObservational Research Programme registry has already provided valuable insights into phenotypic variability, regional disparities, and recovery patterns (5). Expansion of multinational registries with standardized imaging protocols, harmonized outcome definitions, and integration of biomarkers and genetics will enable robust prediction models and facilitate embedded pragmatic trials (4,88). Moreover, global registries can illuminate disparities in care and outcomes, particularly in under-resourced regions where PPCM burden is highest (5).
PPCM has evolved from an obscure obstetric complication into a mechanistically grounded and clinically heterogeneous cardiomyopathy. It is now understood as the intersection of angiogenic imbalance, oxidative stress, genetic susceptibility, and pregnancy-related hemodynamic stress. This shift in understanding reframes PPCM not as a transient postpartum anomaly, but as a dynamic myocardial disorder with variable reversibility and meaningful long-term consequences.
Clinically, early recognition and structured risk stratification are decisive. Baseline ventricular function, remodeling burden, and recovery trajectory define prognosis. Many women experience substantial improvement, yet a significant subset develops persistent systolic dysfunction with lifelong implications. Identifying these divergent paths early is central to optimal management.
Multidisciplinary care is essential. Coordinated collaboration between cardiology and maternal–fetal medicine, careful counseling regarding subsequent pregnancy and contraception, and disciplined postpartum follow-up are fundamental components of care.
Despite progress, key uncertainties remain, particularly regarding disease-specific therapies, duration of heart failure treatment after recovery, arrhythmic risk stratification, and the role of genetic testing. Advancing toward precision, phenotype-guided care supported by large collaborative studies represents the next frontier in PPCM management.
Contributorship: All of the authors contributed planning, conduct, and reporting of the work. All authors had full access to all data in the study and take responsibility for the integrity of the data and the accuracy of the data analysis.
Funding: No financial funding was received for this study.
Competing interests: All of the authors have no conflict of interest.
Artificial Intelligence Disclosure: The authors confirm that no artificial intelligence or AI-assisted tools were used for interpreting the referenced article or for generating scientific content. Limited assistance was obtained solely for language editing and grammatical refinement, without any involvement in data interpretation, analysis, or conceptual input.
Dear Editorial Team, Clinical Medical Reviews and Reports. My experience with the journal was highly positive. The peer-review process was rigorous, constructive, and completed in a timely manner. The reviewers provided valuable comments that helped improve the quality and clarity of our manuscript. The editorial office was professional, responsive, and supportive throughout all stages of the publication process. Communication was clear and efficient, and any questions were addressed promptly. Overall, I found the journal to maintain high scientific standards and an excellent publication workflow. I would be pleased to consider submitting future work to this journal. Best wishes from, Elena Popa.

It was my pleasure to submit my testimonial concerning the Reviewer Board of our Scientific Journal “Brain and Neurological Disorders”. The Reviewers focused on some modifications and their contribution was helpful. The ladies of our Editorial Office were also supported my efforts. It was my honor to have such a co-operation and I am looking forward for more collaboration.

Dear Grace Pierce, Editorial Coordinator of Journal of Clinical Research and Reports, Thank you for the speedy and efficient peer review process. I appreciate the fact that your peer reviewers do not take months to respond like with some other journals. I would also like to thank the editorial office for responding quickly to my questions. It is an excellent journal. I plan to submit more manuscripts in the future. Best wishes from, Robert W. McGee

Dear Grace Pierce, Editorial Coordinator of Journal of Clinical Research and Reports, Working with you and your team on our recent publication in JCRR has been a truly wonderful and enjoyable experience. The responses were prompt, and the reviewers were patient, constructive, and highly professional. One reviewer in particular gave me the feeling that a professor was carefully reading and commenting on my coursework, which was deeply touching. The entire process was straightforward and hassle‑free, with no tedious online forms to complete. I highly recommend this journal. Best wishes from, DR Aibing Rao, Head of R&D

I Appreciate the Opportunity to Share my Experience with the Journal of Clinical Research and Reports. The peer review process was timely and constructive, and the feedback provided helped improve the quality of our manuscript. The editorial office was professional, responsive, and supportive throughout the process, ensuring smooth communication and efficient handling of the submission. Overall, it was a positive experience collaborating with your team.

Dear Mercy Grace, Editorial Coordinator of Obstetrics Gynecology and Reproductive Sciences, We would like to express our gratitude for your help at all stages of publishing and editing the article. The editors of the magazine answer all the necessary questions and help at every stage. We will definitely continue to cooperate and publish other works in the Obstetrics Gynecology and Reproductive Sciences! Best wishes from, Alla Konstantinovna Politova,

Dear Maria Emerson, Editorial Coordinator of International Journal of Clinical Case Reports and Reviews, What distinguishes International Journal of Clinical Case Report and Review is not only the scientific rigor of its publications, but the intellectual climate in which research is evaluated. The submission process is refreshingly free of unnecessary formal barriers and bureaucratic rituals that often complicate academic publishing without adding real value. The peer-review system is demanding yet constructive, guided by genuine scientific dialogue rather than hierarchical or authoritarian attitudes. Reviewers act as collaborators in improving the manuscript, not as gatekeepers imposing arbitrary standards. This journal offers a rare balance: high methodological standards combined with a respectful, transparent, and supportive editorial approach. In an era where publishing can feel more burdensome than research itself, this platform restores the original purpose of peer review — to refine ideas, not to obstruct them Prof. Perlat Kapisyzi, FCCP PULMONOLOGIST AND THORACIC IMAGING.

Dear Reader: We have published several articles in the Auctores Publishing, LLC, journal, Clinical Medical Reviews and Reports in recent years (CMRR). This is an ‘open access’ journal and the following are our observations. From the initial invitation to submit an article, to the final edits of galley proofs, we have found CMRR personnel to be professional, responsive, rapid and thorough. This entire process begins with Catherine Mitchell, Editorial Coordinator. She is simply outstanding, and, I believe, unparalleled in her capacity. I cannot imagine a more responsive and dedicated Editorial Coordinator. As I read the dates and timing of her correspondence with us, it seems that she never sleeps. I hope Auctores Publishing, LLC, appreciates her efforts as much as these authors do. Thank you to Auctores Publishing, LLC, to the Editorial Staff/Board, and to Catherine Mitchell from a grateful author(s).

Dear Maria Emerson, Editorial Coordinator of - Journal of Clinical Research and Reports. ''I am pleased to provide this testimonial following the publication of our recent case report in this journal. The peer review process was rigorous, constructive, thorough, and conducted in a timely manner. The reviewers’ comments were thoughtful, detailed, and highly constructive, contributing substantially to the refinement, clarity, and scientific robustness of our manuscript. The process was conducted with professionalism and academic integrity throughout. The support provided by the editorial office was exemplary. Communication was consistently prompt, clear, and courteous at all stages of the submission and publication process. The editorial team demonstrated a high level of organization and responsiveness, ensuring that all queries were addressed efficiently and that the process remained transparent and well-coordinated. The overall quality of the journal is reflected in its strong editorial standards, commitment to scientific excellence, and dedication to publishing clinically meaningful research. It has been a privilege to publish our work in this journal, and we would welcome the opportunity to contribute further in the future.'' Best wishes from, Dr. Efstratios Trogkanis, Cardiologist.

Dear Grace Pierce, Editorial Coordinator of the journal IJCCR, I had a very positive experience with Auctores - Journal throughout the publication process. The Editorial Team was highly responsive, professional, and supportive at every stage. I would like to extend my sincere thanks to the Editor: Grace Pierce, for her guidance and assistance. The peer-review process was smooth and constructive, helping improve the quality of my work. I would gladly recommend Auctores Journal to fellow researchers and authors. Dr. SABITA SINHA, Medical Oncologist, MD (Electro Homeopathy).

Dear Mayra Duenas, Editorial Coordinator of the journal IJCCR, I write here a little on my experience as an author submitting to the International Journal of Clinical Case Reports and Reviews (IJCCR). This was my first submission to IJCCR and my manuscript was inherently an outsider’s effort. It attempted to broadly identify and then make some sense of life’s under-appreciated mysteries. I initially had responded to a request for possible submissions. I then contacted IJCCR with a tentative topic for a manuscript. They quickly got back with an approval for the submission, but with a particular requirement that it be medically relevant. I then put together a manuscript and submitted it. After the usual back-and-forth over forms and formality, the manuscript was sent off for reviews. Within 2 weeks I got back 4 reviews which were both helpful and also surprising. Surprising in that the topic was somewhat foreign to medical literature. My subsequent updates in response to the reviewer comments went smoothly and in short order I had a series of proofs to evaluate. All in all, the whole publication process seemed outstanding. It was both helpful in terms of the paper’s content and also in terms of its efficient and friendly communications. Thank you all very much. Sincerely, Ted Christopher, Rochester, NY.

International Journal of Clinical Case Reports and Reviews is a high quality journal that has a clear and concise submission process. The peer review process was comprehensive and constructive. Support from the editorial office was excellent, since the administrative staff were responsive. The journal provides a fast and timely publication timeline.

Dear Cecilia Lilly, Editorial Coordinator, Endocrinology and Disorders, Thank you so much for your quick response regarding reviewing and all process till publishing our manuscript entitled: Prevalence of Pre-Diabetes and its Associated Risk Factors Among Nile College Students, Sudan. Best regards, Dr Mamoun Magzoub.

Dear Editorial Team, Clinical Cardiology and Cardiovascular Interventions. I am really grateful for the peers review; their feedback gave me the opportunity to reflect on the message and impact of my work and to ameliorate the article. The editors did a great job in addition by encouraging me to continue with the process of publishing.

Dear Mayra Duenas, Editorial Coordinator of ‘International Journal of Clinical Case Reports and Reviews Herewith I confirm an optimal peer review process and a great support of the editorial office of the present journal
Dear Maria Emerson, Editorial Coordinator of ‘International Journal of Clinical Case Reports and Reviews’, I appreciate the opportunity to publish my article with your journal. The editorial office provided clear communication during the submission and review process, and I found the overall experience professional and constructive. Best regards, Elena Salvatore.

Dear Editorial Team, Journal-Clinical Cardiology and Cardiovascular Interventions, “Publishing my article with Clinical Cardiology and Cardiovascular Interventions has been a highly positive experience. The peer-review process was rigorous yet supportive, offering valuable feedback that strengthened my work. The editorial team demonstrated exceptional professionalism, prompt communication, and a genuine commitment to maintaining the highest scientific standards. I am very pleased with the publication quality and proud to be associated with such a reputable journal.” Warm regards, Dr. Mahmoud Kamal Moustafa Ahmed

Dear Editorial Team, Clinical Cardiology and Cardiovascular Interventions. It was truly a rewarding experience to work with the journal “Clinical Cardiology and Cardiovascular Interventions”. The peer review process was insightful and encouraging, helping us refine our work to a higher standard. The editorial office offered exceptional support with prompt and thoughtful communication. I highly value the journal’s role in promoting scientific advancement and am honored to be part of it. Best regards, Meng-Jou Lee, MD, Department of Anesthesiology, National Taiwan University Hospital.

Dear Maria Emerson, Editorial Coordinator, Journal of Clinical Research and Reports. Thank you for publishing our case report: "Clinical Case of Effective Fetal Stem Cells Treatment in a Patient with Autism Spectrum Disorder" within the "Journal of Clinical Research and Reports" being submitted by the team of EmCell doctors from Kyiv, Ukraine. We much appreciate a professional and transparent peer-review process from Auctores. All research Doctors are so grateful to your Editorial Office and Auctores Publishing support! I amiably wish our article publication maintained a top quality of your International Scientific Journal. My best wishes for a prosperity of the Journal of Clinical Research and Reports. Hope our scientific relationship and cooperation will remain long lasting. Thank you very much indeed. Kind regards, Dr. Andriy Sinelnyk Cell Therapy Center EmCell

I recommend without hesitation submitting relevant papers on medical decision making to the International Journal of Clinical Case Reports and Reviews. I am very grateful to the editorial staff. Maria Emerson was a pleasure to communicate with. The time from submission to publication was an extremely short 3 weeks. The editorial staff submitted the paper to three reviewers. Two of the reviewers commented positively on the value of publishing the paper. The editorial staff quickly recognized the third reviewer’s comments as an unjust attempt to reject the paper. I revised the paper as recommended by the first two reviewers.

Dear Chrystine Mejia, Editorial Coordinator, Journal of Neurodegeneration and Neurorehabilitation. “The peer review process was efficient and constructive, and the editorial office provided excellent communication and support throughout. The journal ensures scientific rigor and high editorial standards, while also offering a smooth and timely publication process. We sincerely appreciate the work of the editorial team in facilitating the dissemination of innovative approaches such as the Bonori Method.” Best regards, Dr. Matteo Bonori.

Dear Maria Emerson, Editorial Coordinator, we have deeply appreciated the professionalism demonstrated by the International Journal of Clinical Case Reports and Reviews. The reviewers have extensive knowledge of our field and have been very efficient and fast in supporting the process. I am really looking forward to further collaboration. Thanks. Best regards, Dr. Claudio Ligresti
Dear Ms. Mayra Duenas, Editorial Coordinator, International Journal of Clinical Case Reports and Reviews. “The International Journal of Clinical Case Reports and Reviews represented the “ideal house” to share with the research community a first experience with the use of the Simeox device for speech rehabilitation. High scientific reputation and attractive website communication were first determinants for the selection of this Journal, and the following submission process exceeded expectations: fast but highly professional peer review, great support by the editorial office, elegant graphic layout. Exactly what a dynamic research team - also composed by allied professionals - needs!" From, Chiara Beccaluva, PT - Italy.

Dear Clarissa Eric, Editorial Coordinator, Journal of Clinical Case Reports and Studies, Auctores Publishing LLC, USA Office: +1-(302)-520-2644. I would like to express my sincere appreciation for the efficient and professional handling of my case report by the ‘Journal of Clinical Case Reports and Studies’. The peer review process was not only fast but also highly constructive—the reviewers’ comments were clear, relevant, and greatly helped me improve the quality and clarity of my manuscript. I also received excellent support from the editorial office throughout the process. Communication was smooth and timely, and I felt well guided at every stage, from submission to publication. The overall quality and rigor of the journal are truly commendable. I am pleased to have published my work with Journal of Clinical Case Reports and Studies, and I look forward to future opportunities for collaboration. Sincerely, Aline Tollet, UCLouvain.

Dear Chrystine Mejia, Editorial Coordinator, Journal of Neurodegeneration and Neurorehabilitation, Auctores Publishing LLC, We would like to thank the editorial team for the smooth and high-quality communication leading up to the publication of our article in the Journal of Neurodegeneration and Neurorehabilitation. The reviewers have extensive knowledge in the field, and their relevant questions helped to add value to our publication. Kind regards, Dr. Ravi Shrivastava.

Dear Clarissa Eric, Editorial Coordinator, Journal of Clinical Case Reports and Studies, I would like to express my deep admiration for the exceptional professionalism demonstrated by your journal. I am thoroughly impressed by the speed of the editorial process, the substantive and insightful reviews, and the meticulous preparation of the manuscript for publication. Additionally, I greatly appreciate the courteous and immediate responses from your editorial office to all my inquiries. Best Regards, Dariusz Ziora

Dear Ashley Rosa, Editorial Coordinator, International Journal of Clinical Case Reports and Reviews, Auctores Publishing LLC. Thank you for publishing our article, Exploring Clozapine's Efficacy in Managing Aggression: A Multiple Single-Case Study in Forensic Psychiatry in the international journal of clinical case reports and reviews. We found the peer review process very professional and efficient. The comments were constructive, and the whole process was efficient. On behalf of the co-authors, I would like to thank you for publishing this article. With regards, Dr. Jelle R. Lettinga.

Dear Jessica Magne, Editorial Coordinator, Clinical Cardiology and Cardiovascular Interventions, Auctores Publishing LLC. The peer review process of the journal of Clinical Cardiology and Cardiovascular Interventions was excellent and fast, as was the support of the editorial office and the quality of the journal. Kind regards Walter F. Riesen Prof. Dr. Dr. h.c. Walter F. Riesen.

Dear Erin Aust, Editorial Coordinator, Journal of General Medicine and Clinical Practice. We are pleased to share our experience with the “Journal of General Medicine and Clinical Practice”, following the successful publication of our article. The peer review process was thorough and constructive, helping to improve the clarity and quality of the manuscript. We are especially thankful to Ms. Erin Aust, the Editorial Coordinator, for her prompt communication and continuous support throughout the process. Her professionalism ensured a smooth and efficient publication experience. The journal upholds high editorial standards, and we highly recommend it to fellow researchers seeking a credible platform for their work. Best wishes By, Dr. Rakhi Mishra.

Dr Hala Al Shaikh This is to acknowledge that the peer review process for the article ’ A Novel Gnrh1 Gene Mutation in Four Omani Male Siblings, Presentation and Management ’ sent to the International Journal of Clinical Case Reports and Reviews was quick and smooth. The editorial office was prompt with easy communication.

Dear Agrippa Hilda, Editorial Coordinator, Journal of Neuroscience and Neurological Surgery. The entire process including article submission, review, revision, and publication was extremely easy. The journal editor was prompt and helpful, and the reviewers contributed to the quality of the paper. Thank you so much! Eric Nussbaum, MD

Dear Ashley Rosa, Editorial Coordinator, International Journal of Clinical Case Reports and Reviews. Many thanks for publishing this manuscript after I lost confidence the editors were most helpful, more than other journals Best wishes from, Susan Anne Smith, PhD. Australian Breastfeeding Association.

Dear Maria Emerson, Editorial Coordinator, International Journal of Clinical Case Reports and Reviews, Auctores Publishing LLC. I am delighted to have published our manuscript, "Acute Colonic Pseudo-Obstruction (ACPO): A rare but serious complication following caesarean section." I want to thank the editorial team, especially Maria Emerson, for their prompt review of the manuscript, quick responses to queries, and overall support. Yours sincerely Dr. Victor Olagundoye.

Dear Jessica Magne, Editorial Coordinator, Clinical Cardiology and Cardiovascular Interventions, Auctores Publishing LLC. I appreciate the journal (JCCI) editorial office support, the entire team leads were always ready to help, not only on technical front but also on thorough process. Also, I should thank dear reviewers’ attention to detail and creative approach to teach me and bring new insights by their comments. Surely, more discussions and introduction of other hemodynamic devices would provide better prevention and management of shock states. Your efforts and dedication in presenting educational materials in this journal are commendable. Best wishes from, Farahnaz Fallahian.

Dear Ashley Rosa, Editorial Coordinator of the journal - Psychology and Mental Health Care. " The process of obtaining publication of my article in the Psychology and Mental Health Journal was positive in all areas. The peer review process resulted in a number of valuable comments, the editorial process was collaborative and timely, and the quality of this journal has been quickly noticed, resulting in alternative journals contacting me to publish with them." Warm regards, Susan Anne Smith, PhD. Australian Breastfeeding Association.

Dear Jessica, and the super professional team of the ‘Clinical Cardiology and Cardiovascular Interventions’ I am sincerely grateful to the coordinated work of the journal team for the no problem with the submission of my manuscript: “Cardiometabolic Disorders in A Pregnant Woman with Severe Preeclampsia on the Background of Morbid Obesity (Case Report).” The review process by 5 experts was fast, and the comments were professional, which made it more specific and academic, and the process of publication and presentation of the article was excellent. I recommend that my colleagues publish articles in this journal, and I am interested in further scientific cooperation. Sincerely and best wishes, Dr. Oleg Golyanovskiy.

To Dear Erin Aust – Editorial Coordinator of Journal of General Medicine and Clinical Practice! I declare that I am absolutely satisfied with your work carried out with great competence in following the manuscript during the various stages from its receipt, during the revision process to the final acceptance for publication. Thank Prof. Elvira Farina

My article, titled 'No Way Out of the Smartphone Epidemic Without Considering the Insights of Brain Research,' has been republished in the International Journal of Clinical Case Reports and Reviews. The review process was seamless and professional, with the editors being both friendly and supportive. I am deeply grateful for their efforts.

We found the peer review process quick and positive in its input. The support from the editorial officer has been very agile, always with the intention of improving the article and taking into account our subsequent corrections.

Dear Jessica Magne, with gratitude for the joint work. Fast process of receiving and processing the submitted scientific materials in “Clinical Cardiology and Cardiovascular Interventions”. High level of competence of the editors with clear and correct recommendations and ideas for enriching the article.

I thank the ‘Journal of Clinical Research and Reports’ for accepting this article for publication. This is a rigorously peer reviewed journal which is on all major global scientific data bases. I note the review process was prompt, thorough and professionally critical. It gave us an insight into a number of important scientific/statistical issues. The review prompted us to review the relevant literature again and look at the limitations of the study. The peer reviewers were open, clear in the instructions and the editorial team was very prompt in their communication. This journal certainly publishes quality research articles. I would recommend the journal for any future publications.

"I am grateful for the opportunity of contributing to [International Journal of Clinical Case Reports and Reviews] and for the rigorous review process that enhances the quality of research published in your esteemed journal. I sincerely appreciate the time and effort of your team who have dedicatedly helped me in improvising changes and modifying my manuscript. The insightful comments and constructive feedback provided have been invaluable in refining and strengthening my work".

To Dear Erin Aust, I would like to express my heartfelt appreciation for the opportunity to have my work published in this esteemed journal. The entire publication process was smooth and well-organized, and I am extremely satisfied with the final result. The Editorial Team demonstrated the utmost professionalism, providing prompt and insightful feedback throughout the review process. Their clear communication and constructive suggestions were invaluable in enhancing my manuscript, and their meticulous attention to detail and dedication to quality are truly commendable. Additionally, the support from the Editorial Office was exceptional. From the initial submission to the final publication, I was guided through every step of the process with great care and professionalism. The team's responsiveness and assistance made the entire experience both easy and stress-free. I am also deeply impressed by the quality and reputation of the journal. It is an honor to have my research featured in such a respected publication, and I am confident that it will make a meaningful contribution to the field.

I would like to express my sincere gratitude for the support and efficiency provided by the editorial office throughout the publication process of my article, “Delayed Vulvar Metastases from Rectal Carcinoma: A Case Report.” I greatly appreciate the assistance and guidance I received from your team, which made the entire process smooth and efficient. The peer review process was thorough and constructive, contributing to the overall quality of the final article. I am very grateful for the high level of professionalism and commitment shown by the editorial staff, and I look forward to maintaining a long-term collaboration with the International Journal of Clinical Case Reports and Reviews.

Dear Agrippa Hilda- Editorial Coordinator of Journal of Neuroscience and Neurological Surgery, "The peer review process was very quick and of high quality, which can also be seen in the articles in the journal. The collaboration with the editorial office was very good."

I would like to offer my testimony in the support. I have received through the peer review process and support the editorial office where they are to support young authors like me, encourage them to publish their work in your esteemed journals, and globalize and share knowledge globally. I really appreciate your journal, peer review, and editorial office.

My experience publishing in International Journal of Clinical Case Reports and Reviews was exceptional. I Come forth to Provide a Testimonial Covering the Peer Review Process and the editorial office for the Professional and Impartial Evaluation of the Manuscript.

My experience publishing in Psychology and Mental Health Care was exceptional. The peer review process was rigorous and constructive, with reviewers providing valuable insights that helped enhance the quality of our work. The editorial team was highly supportive and responsive, making the submission process smooth and efficient. The journal's commitment to high standards and academic rigor makes it a respected platform for quality research. I am grateful for the opportunity to publish in such a reputable journal.

My Testimonial Covering as fellowing: Lin-Show Chin. The peer reviewers process is quick and effective, the supports from editorial office is excellent, the quality of journal is high. I would like to collabroate with Internatioanl journal of Clinical Case Reports and Reviews.

Dealing with The Journal of Neurology and Neurological Surgery was very smooth and comprehensive. The office staff took time to address my needs and the response from editors and the office was prompt and fair. I certainly hope to publish with this journal again.Their professionalism is apparent and more than satisfactory. Susan Weiner

Dear Editorial Coordinator of the Journal of Nutrition and Food Processing! "I would like to thank the Journal of Nutrition and Food Processing for including and publishing my article. The peer review process was very quick, movement and precise. The Editorial Board has done an extremely conscientious job with much help, valuable comments and advices. I find the journal very valuable from a professional point of view, thank you very much for allowing me to be part of it and I would like to participate in the future!”

Dear Monica Gissare, - Editorial Coordinator of Nutrition and Food Processing. ¨My testimony with you is truly professional, with a positive response regarding the follow-up of the article and its review, you took into account my qualities and the importance of the topic¨.

Dear Dr. Jessica Magne, Editorial Coordinator 0f Clinical Cardiology and Cardiovascular Interventions, I hope this message finds you well. I want to express my utmost gratitude for your excellent work and for the dedication and speed in the publication process of my article titled "Navigating Innovation: Qualitative Insights on Using Technology for Health Education in Acute Coronary Syndrome Patients." I am very satisfied with the peer review process, the support from the editorial office, and the quality of the journal. I hope we can maintain our scientific relationship in the long term.

Clinical Cardiology and Cardiovascular Interventions, I would like to express my sincerest gratitude for the trust placed in our team for the publication in your journal. It has been a true pleasure to collaborate with you on this project. I am pleased to inform you that both the peer review process and the attention from the editorial coordination have been excellent. Your team has worked with dedication and professionalism to ensure that your publication meets the highest standards of quality. We are confident that this collaboration will result in mutual success, and we are eager to see the fruits of this shared effort.

The peer reviewers process is quick and effective, the supports from editorial office is excellent, the quality of journal is high. I would like to collabroate with Internatioanl journal of Clinical Case Reports and Reviews journal clinically in the future time.

Clinical Cardiology and Cardiovascular Interventions, we deeply appreciate the interest shown in our work and its publication. It has been a true pleasure to collaborate with you. The peer review process, as well as the support provided by the editorial office, have been exceptional, and the quality of the journal is very high, which was a determining factor in our decision to publish with you.

Clinical Cardiology and Cardiovascular Interventions I testity the covering of the peer review process, support from the editorial office, and quality of the journal.

Dear editorial department: On behalf of our team, I hereby certify the reliability and superiority of the International Journal of Clinical Case Reports and Reviews in the peer review process, editorial support, and journal quality. Firstly, the peer review process of the International Journal of Clinical Case Reports and Reviews is rigorous, fair, transparent, fast, and of high quality. The editorial department invites experts from relevant fields as anonymous reviewers to review all submitted manuscripts. These experts have rich academic backgrounds and experience, and can accurately evaluate the academic quality, originality, and suitability of manuscripts. The editorial department is committed to ensuring the rigor of the peer review process, while also making every effort to ensure a fast review cycle to meet the needs of authors and the academic community. Secondly, the editorial team of the International Journal of Clinical Case Reports and Reviews is composed of a group of senior scholars and professionals with rich experience and professional knowledge in related fields. The editorial department is committed to assisting authors in improving their manuscripts, ensuring their academic accuracy, clarity, and completeness. Editors actively collaborate with authors, providing useful suggestions and feedback to promote the improvement and development of the manuscript. We believe that the support of the editorial department is one of the key factors in ensuring the quality of the journal. Finally, the International Journal of Clinical Case Reports and Reviews is renowned for its high- quality articles and strict academic standards. The editorial department is committed to publishing innovative and academically valuable research results to promote the development and progress of related fields. The International Journal of Clinical Case Reports and Reviews is reasonably priced and ensures excellent service and quality ratio, allowing authors to obtain high-level academic publishing opportunities in an affordable manner. I hereby solemnly declare that the International Journal of Clinical Case Reports and Reviews has a high level of credibility and superiority in terms of peer review process, editorial support, reasonable fees, and journal quality. Sincerely, Rui Tao.

“The peer review process of JPMHC is quick and effective. Authors are benefited by good and professional reviewers with huge experience in the field of psychology and mental health. The support from the editorial office is very professional. People to contact to are friendly and happy to help and assist any query authors might have. Quality of the Journal is scientific and publishes ground-breaking research on mental health that is useful for other professionals in the field”.

Dr.Tania Muñoz, My experience as researcher and author of a review article in The Journal Clinical Cardiology and Interventions has been very enriching and stimulating. The editorial team is excellent, performs its work with absolute responsibility and delivery. They are proactive, dynamic and receptive to all proposals. Supporting at all times the vast universe of authors who choose them as an option for publication. The team of review specialists, members of the editorial board, are brilliant professionals, with remarkable performance in medical research and scientific methodology. Together they form a frontline team that consolidates the JCCI as a magnificent option for the publication and review of high-level medical articles and broad collective interest. I am honored to be able to share my review article and open to receive all your comments.

I am delighted to publish our manuscript entitled "A Perspective on Cocaine Induced Stroke - Its Mechanisms and Management" in the Journal of Neuroscience and Neurological Surgery. The peer review process, support from the editorial office, and quality of the journal are excellent. The manuscripts published are of high quality and of excellent scientific value. I recommend this journal very much to colleagues.

I would like to give my testimony in the support I have got by the peer review process and to support the editorial office where they were of asset to support young author like me to be encouraged to publish their work in your respected journal and globalize and share knowledge across the globe. I really give my great gratitude to your journal and the peer review including the editorial office.

I am very pleased to serve as EBM of the journal, I hope many years of my experience in stem cells can help the journal from one way or another. As we know, stem cells hold great potential for regenerative medicine, which are mostly used to promote the repair response of diseased, dysfunctional or injured tissue using stem cells or their derivatives. I think Stem Cell Research and Therapeutics International is a great platform to publish and share the understanding towards the biology and translational or clinical application of stem cells.

We are grateful for this opportunity to provide a glowing recommendation to the Journal of Psychiatry and Psychotherapy. We found that the editorial team were very supportive, helpful, kept us abreast of timelines and over all very professional in nature. The peer review process was rigorous, efficient and constructive that really enhanced our article submission. The experience with this journal remains one of our best ever and we look forward to providing future submissions in the near future.

I would like to express my gratitude towards you process of article review and submission. I found this to be very fair and expedient. Your follow up has been excellent. I have many publications in national and international journal and your process has been one of the best so far. Keep up the great work.

"We recently published an article entitled “Influence of beta-Cyclodextrins upon the Degradation of Carbofuran Derivatives under Alkaline Conditions" in the Journal of “Pesticides and Biofertilizers” to show that the cyclodextrins protect the carbamates increasing their half-life time in the presence of basic conditions This will be very helpful to understand carbofuran behaviour in the analytical, agro-environmental and food areas. We greatly appreciated the interaction with the editor and the editorial team; we were particularly well accompanied during the course of the revision process, since all various steps towards publication were short and without delay".

I am very glad to say that the peer review process is very successful and fast and support from the Editorial Office. Therefore, I would like to continue our scientific relationship for a long time. And I especially thank you for your kindly attention towards my article. Have a good day!

Dear Erica Kelsey, Editorial Coordinator of Cancer Research and Cellular Therapeutics Our team is very satisfied with the processing of our paper by your journal. That was fast, efficient, rigorous, but without unnecessary complications. We appreciated the very short time between the submission of the paper and its publication on line on your site.

Thank you very much for publishing my Research Article titled “Comparing Treatment Outcome Of Allergic Rhinitis Patients After Using Fluticasone Nasal Spray And Nasal Douching" in the Journal of Clinical Otorhinolaryngology. As Medical Professionals we are immensely benefited from study of various informative Articles and Papers published in this high quality Journal. I look forward to enriching my knowledge by regular study of the Journal and contribute my future work in the field of ENT through the Journal for use by the medical fraternity. The support from the Editorial office was excellent and very prompt. I also welcome the comments received from the readers of my Research Article.

International Journal of Clinical Case Reports and Reviews. I strongly recommend to consider submitting your work to this high-quality journal. The support and availability of the Editorial staff is outstanding and the review process was both efficient and rigorous.

Dear Agrippa Hilda, Journal of Neuroscience and Neurological Surgery, Editorial Coordinator, I trust this message finds you well. I want to extend my appreciation for considering my article for publication in your esteemed journal. I am pleased to provide a testimonial regarding the peer review process and the support received from your editorial office. The peer review process for my paper was carried out in a highly professional and thorough manner. The feedback and comments provided by the authors were constructive and very useful in improving the quality of the manuscript. This rigorous assessment process undoubtedly contributes to the high standards maintained by your journal.

As an author who has recently published in the journal "Brain and Neurological Disorders". I am delighted to provide a testimonial on the peer review process, editorial office support, and the overall quality of the journal. The peer review process at Brain and Neurological Disorders is rigorous and meticulous, ensuring that only high-quality, evidence-based research is published. The reviewers are experts in their fields, and their comments and suggestions were constructive and helped improve the quality of my manuscript. The review process was timely and efficient, with clear communication from the editorial office at each stage. The support from the editorial office was exceptional throughout the entire process. The editorial staff was responsive, professional, and always willing to help. They provided valuable guidance on formatting, structure, and ethical considerations, making the submission process seamless. Moreover, they kept me informed about the status of my manuscript and provided timely updates, which made the process less stressful. The journal Brain and Neurological Disorders is of the highest quality, with a strong focus on publishing cutting-edge research in the field of neurology. The articles published in this journal are well-researched, rigorously peer-reviewed, and written by experts in the field. The journal maintains high standards, ensuring that readers are provided with the most up-to-date and reliable information on brain and neurological disorders. In conclusion, I had a wonderful experience publishing in Brain and Neurological Disorders. The peer review process was thorough, the editorial office provided exceptional support, and the journal's quality is second to none. I would highly recommend this journal to any researcher working in the field of neurology and brain disorders.

Dear Hao Jiang, to Journal of Nutrition and Food Processing We greatly appreciate the efficient, professional and rapid processing of our paper by your team. If there is anything else we should do, please do not hesitate to let us know. On behalf of my co-authors, we would like to express our great appreciation to editor and reviewers.

This is an acknowledgment for peer reviewers, editorial board of Journal of Clinical Research and Reports. They show a lot of consideration for us as publishers for our research article “Evaluation of the different factors associated with side effects of COVID-19 vaccination on medical students, Mutah university, Al-Karak, Jordan”, in a very professional and easy way. This journal is one of outstanding medical journal.

Dr. Bernard Terkimbi Utoo, I am happy to publish my scientific work in Journal of Women Health Care and Issues (JWHCI). The manuscript submission was seamless and peer review process was top notch. I was amazed that 4 reviewers worked on the manuscript which made it a highly technical, standard and excellent quality paper. I appreciate the format and consideration for the APC as well as the speed of publication. It is my pleasure to continue with this scientific relationship with the esteem JWHCI.

Testimony of Journal of Clinical Otorhinolaryngology: work with your Reviews has been a educational and constructive experience. The editorial office were very helpful and supportive. It was a pleasure to contribute to your Journal.

Thank you most sincerely, with regard to the support you have given in relation to the reviewing process and the processing of my article entitled "Large Cell Neuroendocrine Carcinoma of The Prostate Gland: A Review and Update" for publication in your esteemed Journal, Journal of Cancer Research and Cellular Therapeutics". The editorial team has been very supportive.

Dr. Katarzyna Byczkowska My testimonial covering: "The peer review process is quick and effective. The support from the editorial office is very professional and friendly. Quality of the Clinical Cardiology and Cardiovascular Interventions is scientific and publishes ground-breaking research on cardiology that is useful for other professionals in the field.
Journal of Neuroscience and Neurological Surgery. I had the experience of publishing a research article recently. The whole process was simple from submission to publication. The reviewers made specific and valuable recommendations and corrections that improved the quality of my publication. I strongly recommend this Journal.

The peer-review process which consisted high quality queries on the paper. I did answer six reviewers’ questions and comments before the paper was accepted. The support from the editorial office is excellent.

We would like to thank the Journal of Thoracic Disease and Cardiothoracic Surgery because of the services they provided us for our articles. The peer-review process was done in a very excellent time manner, and the opinions of the reviewers helped us to improve our manuscript further. The editorial office had an outstanding correspondence with us and guided us in many ways. During a hard time of the pandemic that is affecting every one of us tremendously, the editorial office helped us make everything easier for publishing scientific work. Hope for a more scientific relationship with your Journal.

Journal of Clinical Research and Reports I would be very delighted to submit my testimonial regarding the reviewer board and the editorial office. The reviewer board were accurate and helpful regarding any modifications for my manuscript. And the editorial office were very helpful and supportive in contacting and monitoring with any update and offering help. It was my pleasure to contribute with your promising Journal and I am looking forward for more collaboration.

Journal of Women Health Care and Issues By the present mail, I want to say thank to you and tour colleagues for facilitating my published article. Specially thank you for the peer review process, support from the editorial office. I appreciate positively the quality of your journal.

Journal of Clinical Cardiology and Cardiovascular Intervention The submission and review process was adequate. However I think that the publication total value should have been enlightened in early fases. Thank you for all.

Clearly Auctoresonline and particularly Psychology and Mental Health Care Journal is dedicated to improving health care services for individuals and populations. The editorial boards' ability to efficiently recognize and share the global importance of health literacy with a variety of stakeholders. Auctoresonline publishing platform can be used to facilitate of optimal client-based services and should be added to health care professionals' repertoire of evidence-based health care resources.
