

Research Article | DOI: https://doi.org/10.31579/2690-4861/1161
1Consultant Plastic and Reconstructive Surgeon.
2Gynaecomastia Surgeon.
*Corresponding Author: Sotirios Foutsizoglou, Consultant Plastic and Reconstructive Surgeon.
Citation: Sotirios Foutsizoglou, Hassan Nurein, (2026), Complications and Revisions After Gynaecomastia Surgery: A Random-Effects Meta-Analysis and Lessons from a 300-Patient Single-Practice Cohort Study, International Journal of Clinical Case Reports and Reviews, 37(2); DOI:10.31579/2690-4861/1161
Copyright: © 2026, Sotirios Foutsizoglou. This is an open-access article distributed under the terms of the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original author and source are credited.
Received: 07 September 2026 | Accepted: 18 September 2026 | Published: 25 September 2026
Keywords: gynaecomastia; postoperative complications; revision surgery; reoperation; liposuction; subcutaneous mastectomy; meta-analysis; retrospective cohort study
Background: Gynaecomastia ranges from localised fibroglandular enlargement to marked ptotic hypertrophy, and reported complication and revision rates after surgical correction vary considerably.
Methods: This study comprises a random-effects re-analysis of aggregate data from a published systematic review and a retrospective cohort study. Arm-level data from 17 technique-specific subgroups comprising 7,294 patients were analysed using Freeman–Tukey random-effects pooling, subgroup analysis, meta-regression and prediction intervals. Because Simon grade was absent from the source data and inferred from the operative technique used, grade-specific estimates were indirect rather than observed. A consecutive 300-patient single-practice cohort was retrospectively assessed over a 365-day records-based observation period and compared with technique-standardised expected rates. The primary revision endpoint was any further procedure within 365 days. Further procedures were classified by the treating surgeons, without independent review, as elective refinement, residual-tissue re-excision, unplanned complication-related reoperation or true glandular recurrence.
Results: The pooled complication rate was 14.44% (95% CI, 9.04–20.73%), with a 95% prediction interval of 0.11–44.88% and substantial heterogeneity (I² = 96.9%). Complication rates differed across indirectly assigned Simon-grade groups: 14.85% for Grades I–IIa, 10.24% for Grades IIa–IIb, and 32.64% for Grades IIb–III (p < 0.001), with the highest rate observed in the skin-excision subgroup. Glandular excision alone was associated with 2.61 times the complication rate of excision with adjunctive liposuction. In the practice cohort, 11 patients (3.67%) experienced complications. The technique-standardised complication ratio was 0.30, although the observed rate remained within the prediction interval. Of 36 subsequent procedures, 32 were elective refinements, three were residual-tissue re-excisions, and one was an unplanned return to theatre. No true glandular recurrences occurred. The clinically indicated reoperation rate was 1.33%, compared with an overall revision rate of 12.00%.
Conclusions: Complication and reoperation rates should be interpreted as stratified outcomes influenced by gynaecomastia grade, operative complexity, adjunctive procedures and outcome definitions. Without such stratification, comparisons may be confounded, and the true rates of complications and clinically indicated reoperations may be misrepresented.
Gynaecomastia is benign proliferation of true glandular tissue in the male breast, distinct from lipomastia, in which enlargement is predominantly adipose [1,2]. This distinction has direct operative implications. Liposuction can reduce the fatty component and improve chest contour, but it may leave a firm fibroglandular disc untreated when used alone, contributing to residual fullness or subsequent reoperation [3]. Surgical planning must therefore address the relative contributions of gland, fat, skin excess, areolar enlargement, ptosis, and nipple–areola complex position rather than apply a single surgical technique or modality to all grades. Simon's classification remains the most widely used clinical grading system: Grade I denotes minor enlargement without skin excess; Grade IIa, moderate enlargement without skin excess; Grade IIb, moderate enlargement with minor skin excess; and Grade III, marked enlargement with substantial skin excess [1]. Rohrich's system incorporates estimated tissue volume, tissue composition, and ptosis [4], whereas Cordova and Moschella classify severity according to the relationship of the nipple–areola complex to the inframammary fold [5] (Table 1).
| System | Classification basis | Grades and definitions | Relevance to this study |
| Simon (1973) [1] | Degree of breast enlargement and presence of skin excess | I: small enlargement, no skin excess. IIa: moderate enlargement, no skin excess. IIb: moderate enlargement with minor skin excess. III: marked enlargement with substantial skin excess. | Primary system used throughout. Presence of skin excess is directly relevant to whether formal skin resection is required. |
| Rohrich (2003) [4] | Estimated tissue volume, tissue composition, and degree of ptosis | I: <250 g, no ptosis (IA predominantly glandular; IB predominantly fibrous). II: 250–500 g, no ptosis (IIA predominantly glandular; IIB predominantly fibrous). III: >500 g with grade I ptosis. IV: severe hypertrophy with grade II or III ptosis. | Incorporates tissue composition and ptosis, but the source data did not report outcomes in a way that allowed reliable mapping to this system. |
| Cordova–Moschella (2008) [5] | Position of the nipple–areola complex (NAC) relative to the inframammary fold | I: increased areolar diameter and protrusion limited to the areolar region. II: moderate hypertrophy with the NAC above the inframammary fold. III: major hypertrophy with glandular ptosis and the NAC at the fold or ≤1 cm below it. IV: major hypertrophy with skin redundancy, severe ptosis, and the NAC >1 cm below the fold. | Provides an objective guide to skin-sparing versus skin-resecting treatment but was not used in the source literature. |
Table 1: Commonly used clinical classification systems for gynaecomastia
Simon’s classification was selected for the present analysis because its central variable—skin excess—most directly determines whether treatment can remain skin-sparing or requires formal skin excision. The systems of Rohrich and of Cordova and Moschella could not be applied, because the contributing studies did not report resected tissue volume, tissue composition, degree of ptosis, or the position of the nipple–areola complex relative to the inframammary fold. Lower gynaecomastia grades are usually treated with suction-assisted contouring and limited direct glandular excision. Intermediate disease commonly requires glandular excision combined with liposuction, with selective energy-assisted skin contraction or circumareolar skin reduction/periareolar mastopexy when skin redundancy or areolar enlargement persists. Advanced ptotic disease may require a skin-reducing mastectomy with nipple–areola complex (NAC) repositioning on a vascularised pedicle or, in selected severe cases, as a free graft. Each additional operative step addresses a distinct aspect of the gynaecomastia presentation, but also alters scar placement, dead space, closure tension, NAC perfusion and sensation, and the expected complication profile [2, 6, 7]. Reported complication and reoperation rates vary several-fold. A systematic review of 94 studies found complication rates of 14.87% after aspiration, 30.64% after excision, and 11.76% after combined approaches [7]; another review reported major complication rates from 0% to 33% [8], whereas national database studies using 30-day follow-up periods reported rates of 1.9% and 4.4% [9, 10]. This variation may reflect differences in severity, operative technique, duration and completeness of follow-up, data ascertainment, or outcome definition. Technique labels can be misleadingly broad: “excision” may refer to limited removal of gland, excision combined with periareolar mastopexy, or a more extensive skin-reducing mastectomy. Likewise, “revision” may denote emergency treatment of a complication, re-excision of residual tissue, treatment of true regrowth, or elective refinement of an otherwise acceptable result. These operations and outcomes are clinically distinct but are often pooled.
This study examined complications and revisions as related but clinically distinct outcomes by combining two complementary sources of evidence. A random-effects meta-analysis of 7,294 patients generated reference estimates stratified by surgical technique, adjunctive liposuction, indirectly assigned Simon grade, and operative complexity. A 300-patient cohort from the authors’ practice was then benchmarked against those estimates and re-analysed using progressively narrower definitions of revision. The aim of the study was therefore threefold: to generate technique-, grade- and complexity-stratified reference estimates of complication risk from the available published evidence; to benchmark a consecutive single-practice cohort against those estimates using prediction intervals rather than pooled means; and to quantify the extent to which a reported revision rate is determined by the endpoint definition applied rather than by the clinical events themselves. The design was a systematic review with random-effects meta-analysis, undertaken as a secondary re-analysis of previously published aggregate arm-level data, together with an accompanying retrospective observational cohort study. Because the grade and complexity strata were inferred from technique rather than observed at patient level, the stratified estimates are presented throughout as hypothesis-generating, and the study is intended to define what can legitimately be learned from the existing evidence and what cannot, rather than to establish comparative effectiveness.
Study Design and Data Sources
This was a systematic review with random-effects meta-analysis, undertaken as a secondary re-analysis of previously published aggregate arm-level data, combined with a retrospective audit of a single-practice 300-patient cohort. The published-data analysis generated reference complication estimates and explored differences according to operative technique, use of adjunctive procedures such as liposuction, indirectly assigned Simon grade and a four-level operative complexity score. The audit benchmarked observed outcomes against these estimates, described the distribution of operative techniques and adjunctive procedures, and assessed how the definition of revision influenced interpretation. For the re-analysis, arm-level event counts and denominators for 17 technique-specific subgroups were extracted from the largest published systematic review of complications following gynaecomastia correction. Unlike reviews reporting summary percentages alone, it provided event counts and denominators for each technique subgroup across 94 studies comprising 7,294 patients [7]. Each technique subgroup was treated as the unit of analysis. No de novo study-level search, screening, or data extraction was performed, and the 94 primary studies were not independently retrieved or appraised. Because this study re-analysed aggregated arm-level data rather than undertaking de novo study-level collection, the analysis necessarily inherits the methodology, eligibility decisions, data extraction, technique classification and quality appraisal of the source review. Any error, misclassification or bias present in that review is therefore propagated into the present analysis and could not be independently verified. Within-subgroup heterogeneity and primary-study risk of bias could not be evaluated; therefore, the reported heterogeneity may underestimate the full variability across the contributing studies, and no independent risk-of-bias or certainty-of-evidence assessment, such as Grading of Recommendations Assessment, Development and Evaluation (GRADE), could be undertaken. The pooled estimates should therefore be interpreted as a formal random-effects re-analysis of aggregate data from a previous review, rather than as independent confirmation of its findings, and this study remains conditional on the validity of that review. No protocol was prospectively registered and the study was not registered with PROSPERO because it involved re-analysis of an existing published aggregate dataset. Reporting followed applicable PRISMA principles, with these departures explicitly acknowledged [11]. No contributing study reported complications directly according to Simon grade or consistently separated the individual components of combined procedures. Each technique subgroup was therefore indirectly mapped to the Simon grade and level of operative complexity with which it is conventionally associated (Table 2). This mapping represents an assumption imposed by the authors on the source data rather than a property of the data themselves: no patient in the pooled dataset had a recorded Simon grade, and no contributing study assigned one. Accordingly, all grade-stratified results reported below refer to technique strata labelled according to their assumed correspondence with Simon grade. These findings are hypothesis-generating, depend on the validity of that assumed correspondence across the contributing studies, and must not be interpreted as directly observed grade-specific complication rates.
| Technique subgroup (as reported by Innocenti A, Melita D, Dreassi E [7]) | Complexity level | No of Complications | No of Patients | Crude rate | Pooled rate (95% CI) |
| Grade I–IIa · lower complexity — 8 subgroups | |||||
| Mixed aspiration techniques | 1 | 59 | 453 | 13.02% | — |
| Traditional liposuction | 1 | 41 | 241 | 17.01% | — |
| Laser lipolysis | 1 | 6 | 71 | 8.45% | — |
| Sharp-cutting liposuction | 1 | 4 | 57 | 7.02% | — |
| Ultrasound-assisted liposuction | 1 | 2 | 31 | 6.45% | — |
| Suction-assisted liposuction | 1 | 18 | 21 | 85.71% | — |
| Pull-through + liposuction | 2 | 80 | 713 | 11.22% | — |
| Fragmentation + liposuction | 2 | 33 | 301 | 10.96% | — |
| Subtotal, Grade I–IIa | 243 | 1,888 | 12.87% | 14.85% (9.56–21.02) | |
| Grade IIa–IIb · intermediate complexity — 8 subgroups | |||||
| Cartilage shaver + liposuction | 2 | 38 | 186 | 20.43% | — |
| Endoscopically assisted glandular excision | 2 | 7 | 138 | 5.07% | — |
| Vacuum-assisted (mammotome) excision | 2 | 9 | 73 | 12.33% | — |
| Suction-assisted excision + liposuction | 2 | 4 | 36 | 11.11% | — |
| Endoscopic adenectomy + liposuction | 2 | 2 | 24 | 8.33% | — |
| Microdebrider excision | 2 | 2 | 8 | 25.00% | — |
| Transaxillary excision | 2 | 0 | 5 | 0.00% | — |
| Open excision + liposuction | 3 | 273 | 2,396 | 11.39% | — |
| Subtotal, Grade IIa–IIb | 335 | 2,866 | 11.69% | 10.24% (6.27–14.88) | |
| Grade IIb–III · highest complexity — 1 subgroup | |||||
| Open excision + formal skin reduction | 4 | 829 | 2,540 | 32.64% | — |
| Subtotal, Grade IIb–III | 829 | 2,540 | 32.64% | 32.64% (30.83–34.47) | |
| Total — all 17 subgroups | 1407 | 7,294 | 19.29% | 14.44% (9.04–20.73) | |
Table 2: Mapping of technique subgroups to operative complexity and Simon grade.
• Multiple event categories may be counted for one patient. Follow-up and reporting thresholds vary. Open excision includes different excisional approaches
• Complexity levels: 1, aspiration only; 2, gland removed by minimal-access route with or without liposuction; 3, open glandular excision with liposuction; 4, open excision encompassing formal skin excision.
• Crude rates are simple arm-level proportions. Pooled rates are random-effects estimates (Freeman–Tukey double arcsine, DerSimonian–Laird) and differ from the crude figures because pooling weights each subgroup by its precision rather than by its size; the overall crude rate of 19.29% is dominated by the single 2,540-patient open-excision subgroup, whereas the pooled estimate of 14.44% is not.
• Two strata span more than one complexity level: pull-through and fragmentation techniques sit at level 2 within the Grade I–IIa stratum, and open excision with liposuction sits at level 3 within the Grade IIa–IIb stratum. Grade attribution is indirect throughout, inferred from the technique conventionally used rather than recorded at patient level. Suction-assisted liposuction (18 of 21) is the extreme outlier excluded in sensitivity analysis.
Aspiration-only procedures were assigned to complexity level 1; minimal-access excision, with or without liposuction, to level 2; open excision with liposuction to level 3; and open excision involving formal skin reduction to level 4. In clinical practice, level 4 may encompass circumareolar skin excision or periareolar mastopexy, wider skin-reducing mastectomy, pedicled NAC repositioning, or free NAC grafting. However, these individual procedures could not be distinguished in the source dataset. The grade and complexity analyses are therefore indirect, and the highest-risk stratum should not be interpreted as a procedure-specific estimate for any individual mastopexy, skin-resection pattern, or NAC-transfer technique. The complication rate associated with this stratum reflects a heterogeneous grouping of operative techniques rather than a directly observed rate for any specific procedure or for high-grade gynaecomastia itself. The practice cohort comprised all patients coded as undergoing primary gynaecomastia surgery in the authors’ private London practice between 1 January and 30 June 2025. Nine exact duplicate entries were removed from 309 records, leaving 300 unique patients. Repeat procedures were linked by name and confirmed by date of birth. Three same-name records were verified as different patients, thereby avoiding an 8.3% inflation of the repeat-procedure numerator (Figure. 1).
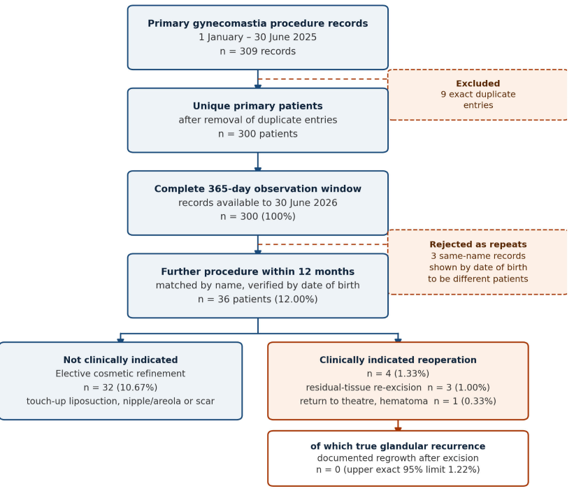
Figure 1: Practice cohort data collection. Nine exact duplicates were removed from 309 records. Three same-name records were confirmed as different patients by date of birth; without that check, the repeat-procedure numerator would have been inflated by 8.3%.
Outcomes were defined a priori and counted per patient rather than per breast. Complications included any documented haematoma, seroma, infection or cellulitis, wound dehiscence, or nipple–areola complex ischaemia, ranging from superficial epidermolysis to partial- or full-thickness necrosis. The primary revision endpoint was any further procedure within 365 days of the index operation, regardless of indication. This inclusive endpoint was chosen for external comparison because it does not depend on the operating surgeon’s judgement about indication. Further procedures were retrospectively classified as unplanned complication-related reoperation, residual-tissue re-excision, elective refinement or “touch-up”, or true glandular recurrence. Residual tissue was defined as palpable tissue remaining after the primary procedure. Recurrence required an initially satisfactory contour followed by documented enlargement. Elective refinement denoted patient-requested aesthetic surgery when the surgeon recorded no complication, residual gland, or regrowth. Clinically indicated reoperation comprised complication-related reoperation and residual-tissue re-excision; recurrence would also have qualified, but none occurred. Complications or further procedures managed elsewhere could have been missed. These secondary classifications were assigned by the operating surgeon without independent or blinded adjudication. In particular, classifying patient-requested surgery as elective refinement relies on the surgeon’s judgement that the result was satisfactory. Misclassification in favour of the practice is therefore possible, and the distinction between elective and clinically indicated procedures cannot be verified from the records. This is an acknowledged limitation of the study.
Complication rates were transformed using the Freeman–Tukey double-arcsine method, which stabilises variance and accommodates zero-event strata [12], and pooled with a DerSimonian–Laird random-effects model [13]. Estimates were back-transformed at the harmonic mean sample size [14]. Heterogeneity was assessed using Cochran's Q, τ², and I² [15]. A 95% prediction interval, calculated as t(k − 2)√(τ² + SE²), represented the true complication rate expected for an individual centre and was therefore considered more appropriate for comparison than the confidence interval around the pooled mean. Three prespecified sensitivity analyses were performed: logit pooling, exclusion of strata with fewer than 20 patients, and exclusion of the single stratum with the highest complication rate. Subgroup differences were assessed by Q-between. Meta-regression used the prespecified ordinal operative-complexity score, with residual τ² estimated on fixed weights, and small-study effects were examined by Egger regression [16].
Cohort outcomes were reported with exact Clopper–Pearson intervals [17]. Comparisons with reference estimates used exact binomial and Fisher exact tests, Katz risk ratios, and indirect standardisation for technique mix, with Holm–Bonferroni correction for multiplicity [18]. Robustness was assessed by fragility index and by the benchmark rate below which the cohort comparison would cease to be significant. Tests were two-sided with α = 0.05. Analyses were performed in Python 3.10.12 using custom scripts for exact binomial inference, Fisher’s exact tests, random-effects meta-analysis, estimation of between-study heterogeneity, calculation of prediction intervals, subgroup comparisons, meta-regression and sensitivity analyses.
Pooled Complication Rate and Heterogeneity
Across 17 technique strata and 7,294 patients, 1,407 complications were reported. The random-effects pooled complication rate was 14.44% (95% CI, 9.04%–20.73%), with extreme heterogeneity (Q = 511.4, df = 16, I² = 96.9%, τ² = 0.0225; p < 0.001). The findings were robust to sensitivity analyses: logit-transformed pooling yielded 14.95% (95% CI, 10.24%–21.30%), exclusion of strata with fewer than 20 patients yielded 15.01% (95% CI, 9.54%–21.41%), and exclusion of the extreme outlier yielded 11.79% (95% CI, 6.93%–17.59%); I² remained 96.8%–97.1% throughout (Table 3, Figure. 2).
| Analysis | Strata | Patients | Pooled rate | 95% CI | I² |
| Primary (Freeman–Tukey) | 17 | 7,294 | 14.44% | 9.04–20.73 | 96.9% |
| Logit transformation | 17 | 7,294 | 14.95% | 10.24–21.30 | 96.9% |
| Strata ≥ 20 patients | 15 | 7,262 | 15.01% | 9.54–21.41 | 97.1% |
| Extreme outlier excluded | 16 | 7,273 | 11.79% | 6.93–17.59 | 96.8% |
| 95% prediction interval | — | — | — | 0.11–44.88 | — |
Table 3: Pooled complication rate and sensitivity analyses
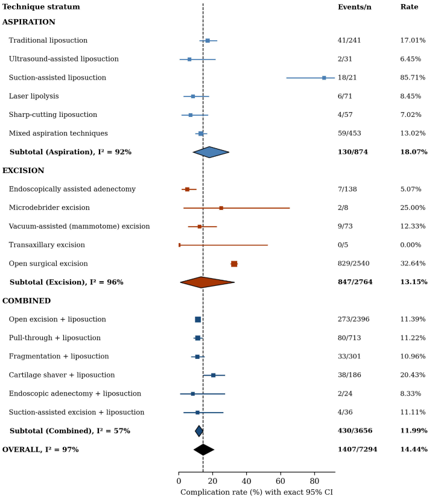
Figure 2: Forest plot of complication rates across 17 technique-specific complication strata and 7,294 patients. The random-effects pooled estimate was 14.44% (95% CI 9.04–20.73; I² = 96.9%), with technique-specific rates from 0% to 85.7%.
The 95% prediction interval extended from 0.11% to 44.88%. Complication rates were 14.85% for indirectly assigned Grade I–IIa, 10.24% for Grade IIa–IIb, and 32.64% for Grade IIb–III including skin resection (p < 0.001). Risk was U-shaped rather than linearly related to operative complexity, with the lowest rates in intermediate combined procedures.
Technique, Operative Complexity, and Adjunctive Procedures
Random-effects pooled complication rates were 18.07% (8.65–29.82) for aspiration-only techniques, 13.15% (0.92–32.96) for excision, and 11.99% (9.74–14.43) for combined excision and liposuction. The between-group test was not statistically significant (Q = 1.56, df = 2; p = 0.46), reflecting substantial within-group heterogeneity. Aggregated arm-level comparisons showed higher complication risks for excision alone than for combined excision–liposuction (crude risk ratio, 2.61; 95% CI, 2.35–2.89; p < 0.001), and for open excision than for open excision with liposuction (crude risk ratio, 2.86; 95% CI, 2.53–3.25). Although the excision-versus-combined comparisons were directionally consistent, the crude analyses used different weighting and did not account for between-stratum heterogeneity or potential case-mix differences. They should therefore be interpreted as descriptive, unadjusted associations rather than causal effects of surgical technique. When strata were regrouped according to whether liposuction was used as an adjunct to excision, single-modality procedures pooled at 16.25% (7.95–26.47), compared with 11.99% (9.74–14.43) for combined procedures (Q = 1.29; p = 0.26 by random effects). The association is clinically plausible because liposuction can debulk the adipose component, improve peripheral contouring, and reduce the extent of open dissection, but the aggregate data do not establish causality. Energy-assisted skin tightening, periareolar mastopexy, wider skin excision, and NAC grafting could not be analysed as independent adjuncts because the source review did not provide separable event denominators. A 2024 review identified limited and heterogeneous evidence for laser-, ultrasound-, radiofrequency-, and other skin-retraction adjuncts [6]. These modalities therefore remain contextual evidence rather than quantitatively pooled comparators in the present analysis.
Simon Grade and Operative Complexity
Under the indirect, technique-based grade mapping, pooled complication rates were 14.85% (9.56–21.02) for Grade I–IIa, 10.24% (6.27–14.88) for Grade IIa–IIb, and 32.64% (30.83–34.47) for Grade IIb–III, the only grade band encompassing skin-excisional surgery. Grade bands differed significantly (Q = 75.3, df = 2; p < 0.001), with the highest band carrying 2.20 times the rate of the lowest (Fig. 3a). These bands were assigned from technique and were not observed at patient level. The comparison is therefore a comparison between technique strata that have been labelled by grade, and the 32.64% figure is an inference from a single technique stratum rather than a direct analysis of patient-level grade data. Its interpretation as evidence of increased complications in high-grade gynaecomastia is therefore hypothesis-generating and requires confirmation in patient series with directly recorded grades.
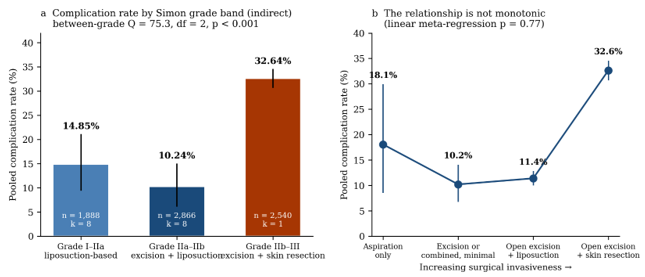
Figure 3: Risk by indirectly assigned Simon grade band (a) and increasing operative complexity (b). Grade bands differed significantly (Q = 75.3, p < 0.001), with the stratum encompassing open skin-resecting surgery at 32.64%. The complexity pattern was U-shaped (18.07%, 10.20%, 11.39%, and 32.64%), with the lowest rates in intermediate combined-technique strata. Specific mastopexy technique, skin-excision and NAC-repositioning procedures were not reported separately in the source data.
Meta-regression found no evidence of a linear trend in complication rates across the operative-complexity score. This score ranks procedures by operative extent, from 1 to 4, but is not a validated quantitative measure of clinical complexity. The analysis therefore tested for a trend across categories, rather than for an association between complication rates and independently measured clinical complexity (Table 4).
| Stratification | Patients | Events | Pooled rate (95% CI) | Test |
| Grade I–IIa | 1,888 | 243 | 14.85% (9.56–21.02) | Q = 75.3 |
| Grade IIa–IIb | 2,866 | 335 | 10.24% (6.27–14.88) | df = 2 |
| Grade IIb–III (skin reduction) | 2,540 | 829 | 32.64% (30.83–34.47) | p < 0.001 |
| Operative complexity 1 (aspiration only) | 874 | 130 | 18.07% | slope 0.014 |
| Operative complexity 2 (minimal-access excision ± liposuction) | 1,484 | 175 | 10.20% | (−0.080 to 0.109) |
| Operative complexity 3 (open excision + liposuction) | 2,396 | 273 | 11.39% | p = 0.77 |
| Operative complexity 4 (open excision + skin reduction) | 2,540 | 829 | 32.64% | R² = 45.4% |
Table 4: Pooled complication rates by indirectly assigned Simon grade band and operative-complexity level.
Grade bands differ significantly, but the relationship with operative complexity is U-shaped rather than monotonic. The excess risk is concentrated in the stratum encompassing skin reduction. The source data did not distinguish periareolar mastopexy, wider skin excision, pedicled NAC repositioning, or free NAC grafting within that subgroup. Neither the linear association (slope 0.014, 95% CI −0.080 to 0.109; p = 0.77) nor the quadratic term assessing curvature (p = 0.087) was statistically significant. Nevertheless, the observed rates across levels 1–4 were 18.07%, 10.20%, 11.39%, and 32.64%, suggesting a U-shaped pattern with higher risk at both the aspiration-only and skin-reduction ends of the spectrum (Figure. 3b). Because the published studies combined different open glandular-excision and skin-reducing techniques, the 32.64% estimate cannot be attributed to any single approach — gland excision with periareolar mastopexy, a specific skin-resection pattern, pedicled NAC repositioning, or free nipple grafting. Compared with combined techniques, excision alone had higher rates of seroma (8.32% versus 0.93; ratio 8.95), over-resection (1.30% versus 0.11%; ratio 11.90), pathological scarring (4.70% versus 1.15%; ratio 4.09), haematoma (7.71% versus 2.68%; ratio 2.87), and nipple–areola necrosis or abrasion (1.27% versus 0.44%; ratio 2.89). The pattern reversed for contour-related outcomes: contour irregularity or redundant skin was 3.7 times more frequent after combined techniques, asymmetry 7.3 times more frequent, and wound dehiscence approximately twice as frequent. Aspiration-only techniques had the highest rates of under-resection (2.86%), altered sensation (4.58%), and revision or recurrence (2.97%) (Figure. 4).
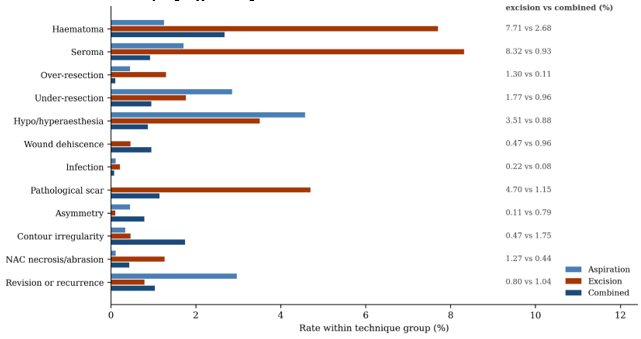
Figure 4: Comparative complication profile of aspiration, excision, and combined techniques.
Complications in the 300-Patient Practice Cohort
Bilateral gland excision was the most commonly performed primary procedure for gynaecomastia correction in our practice (143 patients, 47.67%), followed by VASER-assisted liposuction with gland excision (95, 31.67%) and gland excision and liposuction with either radiofrequency-assisted skin tightening or formal skin reduction/mastopexy, including pedicled NAC repositioning or free NAC grafting when required (42, 14.00%). Gland excision formed part of 291 procedures (97.00%; 95% CI 94.38–98.62), and 137 patients (45.67%) underwent combined excision and liposuction (Table 5).
| n | % | 95% CI | |
| Index procedure | |||
| Bilateral gland excision | 143 | 47.67 | 41.90–53.48 |
| VASER liposuction + gland excision | 95 | 31.67 | 26.44–37.26 |
| Excision and liposuction with RF tightening or skin reduction/NAC repositioning | 42 | 14.00 | 10.28–18.45 |
| Unilateral or unspecified excision | 20 | 6.67 | 4.12–10.11 |
| Gland excision as part of procedure | 291 | 97.00 | 94.38–98.62 |
| Combined excision and liposuction | 137 | 45.67 | 39.93–51.49 |
| Outcomes | |||
| Any recorded complication | 11 | 3.67 | 1.84–6.47 |
| Haematoma | 4 | 1.33 | 0.36–3.38 |
| Infection or cellulitis | 3 | 1.00 | 0.21–2.89 |
| Wound dehiscence | 3 | 1.00 | 0.21–2.89 |
| Seroma | 1 | 0.33 | 0.01–1.84 |
| Unplanned return to theatre | 1 | 0.33 | 0.01–1.84 |
Table 5: Single-practice cohort: primary gynaecomastia surgery and outcomes (n = 300)
Outcomes counted once per patient, not per breast. No patient had more than one recorded complication. Confidence intervals are exact binomial (Clopper–Pearson) intervals.
Eleven patients had a recorded complication (3.67%; 1.84–6.47): haematoma in 4 (1.33%), infection or cellulitis in 3 (1.00%), wound dehiscence in 3 (1.00%), and seroma in 1 (0.33%); no ischaemic change of the nipple–areola complex was recorded. Three haematomas were managed by in-office aspiration and one required operative evacuation. No patient had more than one recorded complication, and one patient (0.33%) required an unplanned return to theatre. Because complications could not be linked to individual components of combined procedures, no valid technique-specific complication rate could be calculated for gland excision alone, gland excision with liposuction, energy-assisted skin tightening (including helium plasma–radiofrequency devices such as Renuvion), or skin-envelope management with or without NAC repositioning or grafting.
Benchmarking Practice-Level Complications. The cohort’s 3.67% complication rate was lower than 16 of the 17 published technique-specific strata. The only lower estimate was a zero-event stratum of five transaxillary cases, and the lowest non-zero rate was 5.07% after endoscopically assisted gland excision. The cohort was significantly below every pooled reference estimate: the risk ratio was 0.25 against all techniques, 0.28 against excision, 0.31 against combined excision and liposuction, and 0.11 against the Grade IIb–III sub-group (all p < 0.001 after Holm–Bonferroni correction; Figure. 5, Table 6).
| Reference estimate | Pooled rate | Cohort risk ratio | Exact p |
| All techniques pooled | 14.44% | 0.25 | < 0.001 |
| Aspiration only | 18.07% | 0.20 | < 0.001 |
| Excision | 13.15% | 0.28 | < 0.001 |
| Combined excision + liposuction | 11.99% | 0.31 | < 0.001 |
| Grade I–IIa band | 14.85% | 0.25 | < 0.001 |
| Grade IIa–IIb band | 10.24% | 0.36 | < 0.001 |
| Grade IIb–III band | 32.64% | 0.11 | < 0.001 |
| 95% prediction interval | 0.11–44.88% | cohort inside interval | not significant |
Table 6: Practice cohort benchmarked against every meta-analytic reference estimate
All comparisons remained significant after Holm–Bonferroni correction. Although the cohort is below every point estimate, it falls within the range expected for an individual centre in this heterogeneous literature, therefore superiority cannot be claimed. Standardised complication ratio for technique mix was 0.30 (95% CI 0.15–0.54). Our practice audit and published literature differ in case mix, gynaecomastia grade, definition of outcome, study design and methodology, duration of follow-up, and how complications were identified and recorded. The apparent advantage observed in the 300-patient cohort may therefore reflect these methodological and case-mix differences rather than a true difference in surgical outcome.
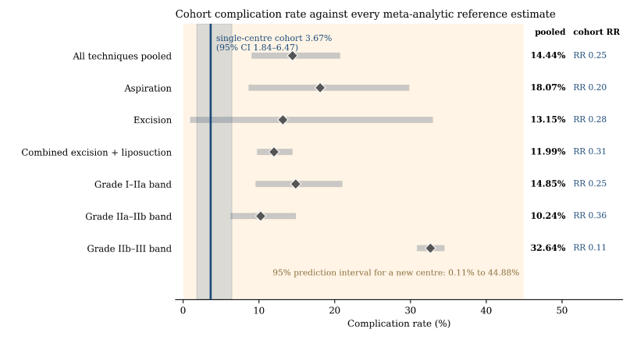
Figure 5: The practice cohort complication rate of 3.67% compared with each meta-analytic reference estimate. It was significantly below all seven pooled point estimates (all p < 0.001; risk ratios 0.11–0.36) but remained within the 95% prediction interval of 0.11–44.88%, so the data do not establish superiority.
Indirect standardisation was applied because the practice cohort was weighted towards excision. Using raw arm-level rates, 63.30 complications were expected among 291 classifiable patients compared
with 11 observed, giving a standardised complication ratio of 0.17. Using the more conservative random-effects estimates, 36.68 were expected, yielding a ratio of 0.30 (95% CI 0.15–0.54; exact p < 0.001; Figure. 6a).
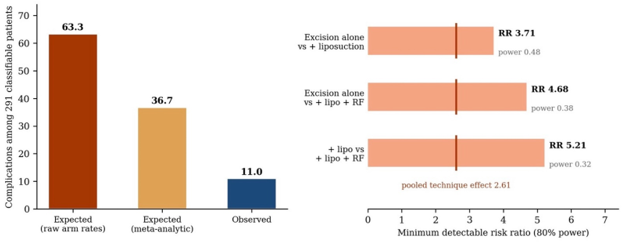
Figure 6: Indirect standardisation and detectability analysis. (a) Technique-standardised benchmarking of the practice cohort: 11 complications were observed versus 63.3 expected from raw arm-level rates and 36.7 from random-effects estimates, giving standardised complication ratios of 0.17 and 0.30. (b) Detectability analysis: minimum detectable risk ratios for planned technique comparisons were 3.71–5.21, exceeding the pooled excision-versus-combined risk ratio of 2.61, indicating limited power to test technique-level effects.
Despite these favourable point comparisons, the cohort estimate lay within the 95% prediction interval of 0.11%–44.88% and was therefore compatible with the range of outcomes expected across comparable centres. The result may reasonably be regarded as favourable within the context of a practice audit, but it does not establish statistical superiority over the published evidence base. In particular, the low observed complication rate cannot be attributed to surgeon skill, the techniques employed, or other characteristics of the practice, because it remains consistent with ordinary between-centre variation in a highly heterogeneous literature. A single-practice series cannot, by design, establish the superiority of a technique or practice, and no such claim is made here.
Revisions and Subsequent Procedures in the Practice Cohort
The primary revision endpoint—any further procedure within 365 days—was met by 36 of 300 patients (12.00%; 8.55–16.22). Under the secondary, surgeon-assigned sub-classification, 32 of these were recorded as elective refinements (10.67%; 7.41–14.72), 3 as residual-tissue re-excisions (1.00%; 0.21–2.89), and 1 as an unplanned complication-related return to theatre (0.33%). No true glandular recurrence was documented (exact upper 95% limit 1.22%). The composite clinically indicated reoperation rate — residual-tissue re-excision, complication-related return to theatre, or true recurrence — was therefore 4 of 300 (1.33%; 0.36–3.38), and elective refinements accounted for 88.9% of patients who returned for further treatment (Fisher exact p < 0.001). The same records consequently yield revision estimates of 12.00%, 10.67%, 1.33%, 1.00%, 0.33%, or 0.00%, depending on how revision is defined (Figure. 7).
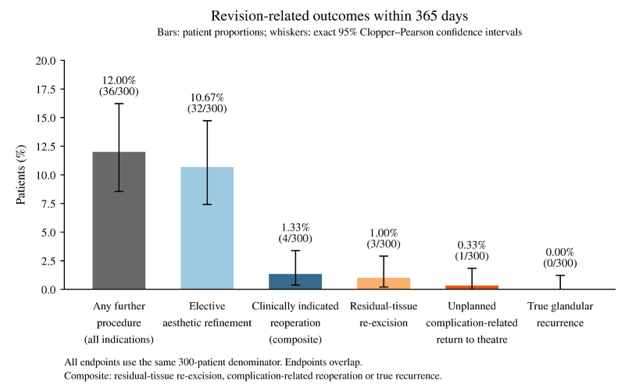
Figure 7: 300 practice patients under six definitions of revision, producing rates from 12.00% to 0.00%. Elective refinements accounted for 88.9% of patients returning for further treatment (Fisher exact p < 0.001); no true glandular recurrence was documented within 365 days. The variation in revision rates reflects differences in endpoint definition rather than differences in the underlying clinical events.
Robustness and Limitations of the Cohort Findings
The practice complication rate remained significantly lower than benchmarks exceeding 6.45%; the corresponding thresholds were 3.43% for haematoma and 1.25% for recurrence. The comparison of complication rates had a fragility index of 14 - an additional 14 unrecorded events would have been required for the comparison with the 11.76% combined-technique benchmark to lose statistical significance. Even doubling the recorded number of complications to 22 of 300 yielded a rate of 7.33% (95% CI, 4.65–10.89%; p = 0.015). By contrast, the clinically indicated reoperation estimate had a fragility index of 1, the four observed cases already lying close to the upper limit of the published range (1.4%; Fig. 8). Thus, whereas the complication comparison appears robust, the 1.33% reoperation estimate is sensitive to minimal changes in event detection or classification—for example, an unrecorded reoperation performed elsewhere or reclassification of one refinement as clinically indicated. It should therefore be interpreted cautiously and not regarded as a practice benchmark.
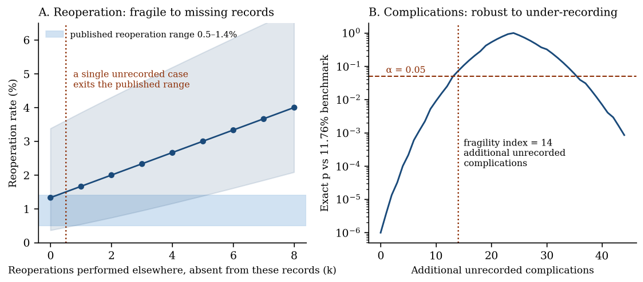
Figure 8: Robustness of the cohort benchmarks. The complication comparison had a fragility index of 14 and remained statistically significant even after doubling the recorded event count (7.33%, p = 0.015). By contrast, the clinically indicated reoperation estimate was highly fragile (fragility index 1): a single additional externally managed or reclassified case would move the estimate beyond the published range. Single-centre complication and reoperation estimates may therefore be biased in opposite directions.
Procedures and complications were reported independently, preventing individual adverse events from being linked to specific techniques or adjuncts. The cohort therefore could not directly compare glandular excision alone with excision plus liposuction, periareolar mastopexy, formal skin reduction, or other adjunctive procedures. Moreover, the low event rate limited statistical power even if patient-level linkage had been available. The minimum detectable risk ratios were 3.71 for excision alone versus excision with liposuction, 4.68 for comparison with the
radiofrequency stratum, and 5.21 between the two liposuction-containing strata, all exceeding the pooled arm-level risk ratio of 2.61. Detecting an effect of that magnitude between the two liposuction-containing strata would require approximately 278 patients per group (Figure. 6b).
Patient-Reported Outcomes
No contributing study reported validated patient-reported outcomes stratified by Simon grade, and none was collected in the practice cohort (Figure. 9).
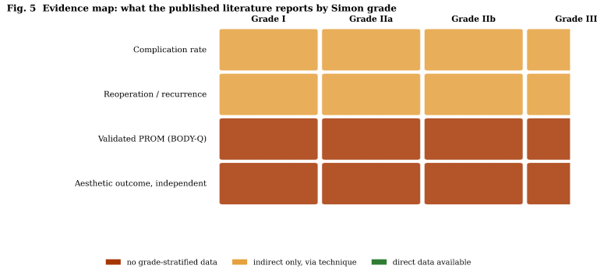
Figure 9: Reported outcomes by Simon grade. Complication data are available indirectly through technique, whereas direct grade-stratified complication data and validated patient-reported outcomes by grade are absent.
Existing reviews identify widespread use of non-validated and inconsistent satisfaction measures [19, 20]. The BODY-Q Chest Module is validated for this population [21]. Published studies have reported favourable postoperative chest and psychological scores [22], an association between revision surgery and poorer chest satisfaction [23], and greater satisfaction after endoscopic transaxillary access than after conventional approaches [24]. These findings suggest a plausible relationship between grade, revision burden, and patient experience, but the available evidence does not permit that relationship to be quantified.
By integrating a random-effects meta-analysis with an audit of 300 consecutive patients treated in a single practice, this study examines associations among Simon grade, operative complexity, adjunctive procedures, complications and reoperations in gynaecomastia surgery. The pooled complication rate was 14.44%, but extreme heterogeneity (I² = 96.9%) precluded its use as a universal benchmark.
Stratified analyses identified the greatest morbidity in the indirectly assigned Grade IIb–III group, which encompassed skin-resecting procedures. Intermediate combined procedures had lower complication rates than both aspiration-only approaches and the most extensive operations. At the aggregate treatment-group level, excision alone was associated with a higher complication rate than excision with adjunctive liposuction, although the complication profile shifted from wound- and scar-related morbidity towards contour irregularity and asymmetry. The practice cohort had a favourable technique-standardised complication ratio but remained within the meta-analytic prediction interval. Thirty-six of the 300 patients (12.00%) underwent a further procedure within 365 days, and this inclusive figure is the appropriate one for comparison with other series. Of these 36, the operating surgeons classified 32 as elective refinements rather than clinically indicated reoperations. Depending on the endpoint applied, the same records yield 12.00% for any further procedure, 1.33% for clinically indicated reoperation, 0.33% for unplanned return to theatre and 0% for true glandular recurrence. This variation illustrates the extent to which revision rates depend on endpoint definition. The 95% prediction interval is essential when interpreting practice-level complication rates. Although the cohort's 3.67% rate was below every pooled point estimate and its technique-standardised complication ratio was 0.30, it remained within the 0.11–44.88% range expected for an individual centre. A confidence interval quantifies uncertainty around the pooled mean. It does not describe the range of results plausibly expected in another practice. The prediction interval is therefore the more relevant comparator, although its extraordinary width also highlights the limitations of the evidence base. The meta-analytic synthesis relied on aggregated technique-specific groups from a single systematic review, meaning that within-group heterogeneity, primary-study risk of bias and study-level publication bias could not be assessed reliably. The prediction interval consequently reflects both genuine clinical variation and inconsistencies in outcome definitions, follow-up periods and reporting thresholds. The cohort is therefore consistent with the favourable end of the range reported in current practice, but it does not establish superiority. Indirect analyses suggested that gynaecomastia grade and operative extent were associated with both the frequency and type of complication, although the relationship did not follow a simple linear increase with complexity. The Grade IIb–III group, which encompassed formal skin-excisional techniques, had a pooled complication rate of 32.64%—more than twice the rate in the Grade I–IIa group and more than three times that in the Grade IIa–IIb group. By contrast, minimal-access excision and open gland excision combined with liposuction occupied the lower portion of the observed U-shaped pattern. Greater morbidity at the upper end is clinically plausible because skin reduction may involve additional undermining, dead space, closure tension, longer scars and potential compromise of nipple–areola complex (NAC) perfusion or sensation. Nevertheless, the grade-based analysis was indirect. Simon grade was inferred from the technique conventionally used rather than recorded at patient level, and the high-grade estimate was derived from a single large open-excision group. The findings therefore support the broader conclusion that procedures requiring skin reduction carry greater morbidity, but they do not quantify the independent risk associated with gland excision and periareolar mastopexy, any specific skin-resection pattern, pedicled NAC repositioning or free NAC grafting. Adjunctive procedures should be interpreted according to the problem they are intended to address rather than regarded as uniformly risk-increasing additions. In the aggregate treatment-group data, excision alone was associated with 2.61 times the overall complication rate of excision combined with adjunctive liposuction. It was also associated with higher rates of seroma, haematoma, abnormal scarring, over-resection and NAC compromise. Liposuction-containing approaches, however, were associated with more contour irregularity and asymmetry, demonstrating that adjunctive treatment changes the complication profile rather than increasing the overall risk. At the lower end of the treatment spectrum, aspiration-only techniques had the highest rates of under-resection and revision or recurrence, consistent with the limited ability of suction alone to remove a fibroglandular disc [3]. These findings support the use of adjunctive liposuction as a potentially tissue-sparing contouring adjunct, while recognising that this non-randomised aggregate comparison cannot establish causation. The clearest lessons from the 300-patient cohort concern the classification of subsequent procedures. Of the 36 patients who underwent a further procedure within 365 days, 32 were recorded as elective refinements, three underwent re-excision for residual tissue and one returned to theatre because of a complication. No true glandular recurrence was documented. A broad “revision” label can therefore conflate patient-requested optimisation, incomplete initial excision, complication-related reoperation and breast tissue regrowth—events with fundamentally different causes, clinical implications and potential preventability. However, simply adopting a narrower definition is not sufficient. Because the sub-classification was assigned by the operating surgeon without independent review, and because the elective-refinement category requires the surgeon to judge as satisfactory a result that the patient has sought further surgery to change, a narrow reoperation rate derived in this way is itself a definitional artefact and is systematically liable to understate clinically meaningful dissatisfaction. Nothing in the present data can establish that any individual refinement was genuinely elective. The defensible position is to report the inclusive rate as the headline figure, to report the sub-classification alongside it with its criteria stated, and to have the categories assigned prospectively by an assessor independent of the operating surgeon. Although the limitations of unstratified comparisons are well recognised, this analysis quantitatively demonstrates, within the same dataset, the magnitude of endpoint dependence: revision rates ranged from 12.00% to 0.00% solely according to the definition applied. Within this framework, residual tissue is considered an endpoint of index-procedure completeness, whereas recurrence requires new glandular growth following an initially satisfactory result. The absence of documented recurrence should be regarded as an early observation rather than evidence of long-term durability. Follow-up was limited to 365 days, which is insufficient to assess recurrence in a condition in which regrowth is typically described over several years; treatment received elsewhere may have been missed; and late recurrence after gynaecomastia surgery has been reported [25]. A 0% recurrence rate at one year therefore reflects the follow-up period rather than the durability of the operation, and the exact upper 95% confidence limit of 1.22% should be interpreted accordingly. Similarly, the clinically indicated reoperation rate of 1.33% was based on only four events and was fragile to a single additional case, whereas the overall complication comparison was substantially more robust. The distinction between residual tissue and true recurrence is based primarily on clinical history rather than a validated measurement threshold. Residual tissue is palpable during the early postoperative period and is characteristically described by the patient as having persisted since surgery. True recurrence requires an interval of satisfactory chest contour followed by documented enlargement of the retroareolar disc. Its appearance should prompt investigation for potential precipitating factors, including drug exposure or endocrine disease [26]. Findings reported as recurrence have frequently been attributed to incomplete removal or postoperative scar formation rather than genuine regrowth, and the incidence of recurrence remains uncertain [27]. In practice this distinction is frequently not clear-cut. It depends on the patient’s recollection of whether the chest was ever satisfactory and on an unblinded clinical assessment by the operating surgeon, neither of which is verifiable from a retrospective record, and no imaging or histological standard was applied in the present cohort. When the postoperative interval is short, or the patient history is uncertain, residual tissue and early recurrence may be difficult to distinguish both conceptually and clinically. The observed three-to-zero split between residual tissue and recurrence should therefore be regarded as provisional and as a further illustration of the endpoint dependence that underpins the central argument of this article.
No quantitative definition of adequate glandular resection has been established. The literature provides neither a residual-mass threshold expressed in grams nor a validated imaging criterion. Instead, adequacy is often described in terms of retained retroareolar thickness, an endpoint that remains contested. Conventional teaching favours subtotal excision to reduce the risk of contour depression, with one series recommending preservation of a 3–5-mm retroareolar disc [28]. By contrast, a single-surgeon series of 567 patients advocated complete glandular removal with layered closure of the subareolar dead space and reported no revisions for recurrence, contour depression or persistent nipple prominence [27]. That series warrants the same critical appraisal that has been applied to the present cohort. It is a retrospective, uncontrolled single-surgeon series subject to the same selection, data collection and reporting biases. Outcomes were assessed by the operating surgeon without independent review or validated patient-reported measures, and the reported absence of revisions is itself a surgeon-assessed endpoint of the kind this article argues should be interpreted cautiously. The proposition that complete glandular removal is both achievable and necessary should therefore be regarded as a clearly described technical approach supported by low-level evidence rather than as established evidence. It is cited here as one side of an unresolved technical debate, not as its resolution. These approaches represent fundamentally different operative endpoints. Tissue intentionally preserved under the first approach may be regarded as residual tissue under the second. Neither necessarily implies histological completeness, because microscopic hormonally responsive ductal tissue may remain after subcutaneous mastectomy. “Complete excision” should therefore be understood as a clinical rather than pathological endpoint [27]. In the absence of a validated alternative, this study adopts a pragmatic operational definition rather than implying histological clearance. For the present study, complete excision was defined as the absence of a palpable retroareolar disc at routine follow-up, with the areolar platform lying flush with the surrounding chest wall on inspection and palpation. This definition was adopted for internal consistency but is unvalidated, assessor-dependent, and unblinded, and it is not equivalent to histological clearance. It therefore permits interpretation of residual-tissue rates within this series but limits comparison with studies using retained-thickness or imaging-based criteria. Until a consistent, preferably measurement-based definition is adopted, comparisons of residual-tissue rates across series will remain unreliable.
Unlike residual retroareolar tissue, for which no agreed quantitative threshold exists, nipple–areola complex dimensions can be compared with published reference values. Normative male NAC dimensions were established prospectively in 158 men aged 18–90 years, with mean areolar and nipple diameters of 26.6 mm and 6.9 mm, respectively. Inter-nipple distance, sternal-notch–to-nipple distance and their ratios varied with body mass index but not ethnicity [29]. Areolar enlargement and persistent nipple prominence are common presenting concerns in gynaecomastia and important sources of dissatisfaction after otherwise successful surgery [27]. Reporting preoperative and postoperative areolar dimensions would provide an objective measure of aesthetic change and allow what is described as persistent “puffy nipple” deformity prompting many refinement requests to be documented quantitatively rather than subjectively. These normative values were not, however, applied prospectively in the present practice: areolar and nipple dimensions were not measured before or after surgery in this cohort, and no anthropometric criterion was used either to plan the operation or to adjudicate the refinement requests reported here. Their adoption is therefore proposed as a recommendation for future practice and not offered as a description of the present series. This distinction also explains why “under-resection” may be an unsatisfactory label for the most common indication for further glandular surgery. The term implies a technical shortfall. When a surgeon has deliberately preserved a retroareolar disc in accordance with accepted teaching and the patient subsequently requests its removal, however, the event may represent a mismatch between operative intent and patient expectation rather than an error of execution. Patients seeking gynaecomastia correction may explicitly request complete excision, an expectation reinforced by information shared within patient communities. This observation rests on a single surgical series [27] and on the authors’ own secondary-referral experience. No systematic study has established the role of preoperative expectations in gynaecomastia surgery. It should therefore be regarded as a hypothesis requiring formal investigation with validated expectation measures rather than as established evidence. A technically satisfactory result may consequently still be considered inadequate by the patient. This effect may be amplified in secondary practice, where patients presenting after surgery elsewhere are disproportionately those for whom retained tissue proved unacceptable. Recording the indication for every further procedure—elective refinement, residual tissue following incomplete excision, complication-related reoperation, or documented recurrence—is therefore more than a matter of terminology. It is essential for distinguishing technical failure from mismatches in consent or expectation setting and for determining whether a reported revision rate reflects surgical performance or differences in patient acceptance of retained retroareolar tissue. Recent evidence further highlights the importance of documenting the specific components of each procedure. Studies of circumareolar skin excision suggest that periareolar approaches can address skin redundancy and areolar enlargement while limiting visible scarring, although outcomes remain dependent on operative technique and closure tension [30]. In a 2025 retrospective comparison of 118 patients with Grade IIb–III gynaecomastia, the addition of radiofrequency energy to power-assisted liposuction produced greater objective improvement in chest contour and NAC position and reduction in nipple–areola complex (NAC) area than liposuction alone; however, the non-randomised design did not establish superiority in complication or reoperation rates [31]. A separate Grade IIb series combining circumareolar mastectomy, an interlocking periareolar suture, inframammary-fold release, and waterjet-assisted liposuction reported a complication rate of 7.7% together with favourable BODY-Q outcomes [32]. In patients with marked skin redundancy and ptosis, particularly severe or post-weight-loss cases, high-grade series continue to employ formal skin-reduction techniques and, in selected patients, free NAC grafting [33]. Collectively, these findings support a tailored, multimodal approach while underscoring why broad procedural labels such as “excision”, “mastopexy”, and “skin tightening” should not be treated as equivalent in comparative outcome studies. The audit also identified important limitations in practice-level data collection. Its retrospective, single-practice design lacked independent outcome review and patient-level covariates including body mass index, smoking status, Simon grade, skin quality, ptosis, and comorbidity, precluding risk adjustment beyond technique mix. The favourable standardised complication ratio may therefore partly reflect an unmeasured lower-risk case mix. Outcomes recorded within the treating practice were also susceptible to observer and reporting bias, while complications or reoperations managed elsewhere may have been missed. In addition, individual complications could not be reliably linked to specific operative components, preventing direct technique-level comparisons. Conversely, regular outpatient follow-up may have increased detection of minor wound-related events, making under-detection alone an unlikely explanation for the low complication rate. The observed results may therefore reflect genuine practice performance, favourable case mix, or both. This uncertainty should inform interpretation of the 1.00% infection or cellulitis rate, and comparisons that lost significance after multiple-testing adjustment should not be overinterpreted. With only 11 recorded complications, the cohort had very limited statistical power to detect clinically meaningful differences among operative techniques, The estimated minimum detectable risk ratios (3.71–5.21) exceeded the pooled excision-versus-combined risk ratio of 2.61. Under the assumptions of the power calculations, the cohort would therefore not have achieved the target power to detect an association of this magnitude, even had patient-level linkage been available. These limitations preclude reliable conclusions about comparative safety. The priority for future research is prospective multicentre data collection linking gynaecomastia grade, patient risk factors, operative complexity and individual procedure components to the type, timing, severity, management and outcome of subsequent complications, while distinguishing clinically indicated reoperations from elective aesthetic refinements. Such work would require substantial resources, sustained coordination, agreed grading and event definitions, appropriate consent and data governance, independent outcome adjudication, and follow-up extending beyond one year to assess late recurrence. A staged approach, beginning with consensus definitions and a feasibility study involving a small number of committed centres, may be more achievable than immediately establishing a large multicentre registry.
The absence of validated patient-reported outcomes is a major limitation: complications and reoperations capture harms but inadequately describe the intended benefits in appearance, confidence and psychosocial wellbeing. This also limits interpretation of elective refinements, for which surgeon classification cannot substitute for direct patient assessment. Future studies should prospectively collect the BODY-Q Chest Module and report results by gynaecomastia grade and operative components. The meta-analysis and practice audit support eight reporting domains (Table 7): Simon grade distribution; specific operative components; explicit complication thresholds; separate reporting of elective refinement, residual tissue, true recurrence and unplanned reoperation, with clear distinguishing criteria; a specified follow-up window, including procedures managed outside the treating centre; patient-level denominators; validated patient-reported outcomes; and benchmarking against prediction intervals alongside pooled estimates.
| Reporting domain | Minimum information to report | Purpose |
| Simon grade | Number and proportion of patients in each Simon grade, recorded at patient level. | Allows outcomes to be interpreted according to severity and skin excess. |
| Operative components and steps | Exact technique(s) used in each operation | Rather than using broad labels such as “excision”, studies should record the exact operative components used in each patient, including gland excision alone, gland excision + liposuction, formal skin excision, any other adjunct. |
| Explicit complication thresholds | Definitions and severity thresholds for haematoma, seroma, infection or cellulitis, wound dehiscence, NAC compromise and other events. | Reduces distortion from inconsistent coding and variable reporting thresholds. |
| Separate categories for further procedures | Elective refinement, residual-tissue re-excision, true recurrence and unplanned reoperation should be reported separately, with criteria used to distinguish them. | Prevents a broad revision label from conflating aesthetic optimisation, incomplete excision, complication management and regrowth. |
| Defined ascertainment period | Duration and method of follow-up, including how complications or reoperations managed elsewhere were captured. | Improves comparability between studies with different follow-up periods and degrees of external event capture. |
| Patient-level denominator | Denominators should be reported per patient. | Avoids inflation or misclassification when outcomes are counted per breast, per operation or per record instead of per patient. |
| Validated patient-reported outcomes | Prospective collection of validated measures, preferably the BODY-Q Chest Module, stratified by grade and operative components. | Captures chest appearance, confidence and psychosocial benefit not reflected by complication or reoperation rates alone. |
| Benchmarking against prediction intervals | Compare practice-level outcomes with prediction intervals as well as pooled means or point estimates. | Reflects expected variation between centres and avoids overclaiming superiority in highly heterogeneous evidence. |
Table 7: Minimum reporting set for future gynaecomastia surgery outcome studies
The proposed framework supplements PRISMA, STROBE and Clavien–Dindo with gynaecomastia-specific reporting items to improve clinical comparability. It addresses four barriers identified in this analysis: missing patient-level grade; aggregation of distinct operative components under single technique labels; inconsistent definitions of revision; and benchmarking against pooled estimates without considering prediction intervals. Derived solely from the present analysis, the framework has not undergone formal consensus development. A Delphi process involving surgeons, biostatisticians and patients, followed by testing against existing datasets, would be needed before recommending global adoption.
Strengths include the large pooled dataset (7,294 patients across 17 technique strata from 94 primary studies), prediction intervals for practice-level benchmarking, and prespecified sensitivity, technique-mix standardisation, detectability and fragility analyses. Benchmarking did not establish superiority. The cohort was consecutive and unselected, duplicate records were reconciled, and a source tabulation discrepancy was disclosed. Reporting six revision-related outcome rates from the same dataset demonstrates the influence of endpoint definition (Fig. 7).
Limitations include reliance on one previous systematic review without independent verification of its search, extraction, classification or appraisal; heterogeneity estimates representing a lower bound; and no additional risk-of-bias or certainty-of-evidence assessment. Grade and operative complexity were inferred from technique, making grade-stratified findings hypothesis-generating. The retrospective, single-practice cohort lacked independent outcome review, patient-level covariates and validated patient-reported outcomes. Revision classification relied on unblinded surgeon judgement, follow-up was limited to 365 days, and the clinically indicated reoperation estimate rested on four events. Technique comparisons were substantially underpowered. The cohort therefore illustrates how stratification and endpoint definitions alter reported rates, without establishing superiority of the practice or its techniques.
Implications
Clinical counselling should consider the initial gynaecomastia presentation and planned operative components, including the higher complication rates observed in the skin-excision subgroup. The likelihood of further procedures should be discussed separately from complications, distinguishing elective refinement from clinically indicated reoperation. The intended extent of glandular excision, including preservation of retroareolar tissue, should be agreed and documented before surgery. These findings do not establish a preferred technique. Future research should prospectively link recorded Simon grade and individual operative components to outcomes, incorporate the BODY-Q Chest Module, independently review indications for further procedures, and extend follow-up substantially beyond one year. The present stratified estimates remain hypothesis-generating; consensus outcome definitions are an immediate priority for meaningful comparisons. Quality assessment and guideline development should account for case mix, operative complexity and endpoint definitions. Unstratified rates may disadvantage practices treating more complex or referred cases or comprehensively recording elective refinements. Comparative use of revision rates requires prespecified definitions, patient-level denominators and benchmarking against prediction intervals alongside pooled estimates.
Complication rates varied across operative techniques and indirectly assigned gynaecomastia grades, with the highest rate in the skin-excision stratum and no clear linear relationship with operative complexity. Adjunctive liposuction was associated with lower aggregate complication rates than excision alone. However, reliance on aggregate data from one previous review and inference of grade from technique make the grade-specific findings hypothesis-generating.
In the 300-patient cohort, 12.00% underwent a further procedure, while 1.33% underwent surgeon-classified clinically indicated reoperation; no true glandular recurrence was documented within 365 days. Most further procedures were classified as elective refinements. These findings illustrate how endpoint selection affects reported rates, but the retrospective design, limited follow-up, absent patient-reported outcomes and lack of independent review limit interpretation. The cohort’s complication rate remained within the meta-analytic prediction interval and did not establish superiority of the practice or its techniques. Meaningful comparisons require recorded disease grade, clearly specified operative components and consistent definitions distinguishing elective refinement, residual-tissue re-excision, complication-related reoperation and true recurrence. Prospective patient-level reporting, validated patient-reported outcomes and benchmarking against prediction intervals are priorities for improving the evidence base.
Funding: No external funding was received for this work.
Conflict of Interest: The authors declare that they have no conflicts of interest to disclose.
Statement of Human and Animal Rights All procedures performed in this study involving human participants were in accordance with the ethical standards of the institutional research committee and with the 1964 Helsinki Declaration and its later amendments or comparable ethical standards. The cohort component was a retrospective review of routinely collected practice records, pseudonymised before analysis, and did not require institutional review board approval. It involved no change to patient care, no additional intervention and no identifiable data, and under applicable national research-governance criteria such work is classified as service evaluation or clinical audit rather than research requiring research ethics committee review. The authors confirm that this position is consistent with the journal’s policy for retrospective studies of routinely collected data, and documentation can be supplied to the Editors on request. The evidence-synthesis component used published aggregate data only. This article does not contain any studies with animals performed by any of the authors.
Informed Consent For this type of retrospective study, formal informed consent is not required. Written informed consent for publication of any clinical images was obtained from the patients concerned.
Data Availability: The aggregate arm-level data re-analysed in this study are published in full in the source systematic review [7]. The derived analytic dataset, the pooled and stratified estimates, and the analysis code are available from the corresponding author on reasonable request. The practice cohort consists of pseudonymised individual patient records that cannot be shared in full; data underlying all reported cohort results are available from the authors on reasonable request, subject to applicable data-protection requirements.
Protocol and Registration No protocol was prospectively registered for this work, and the review was not registered with PROSPERO. The meta-analytic component re-analyses an existing published aggregate dataset rather than undertaking a new primary literature search, and the cohort component was a retrospective service evaluation; neither meets the criteria for prospective registration. The analytical plan for both components—including the outcome definitions, the technique-to-grade mapping, the prespecified sensitivity analyses and the standardisation approach—was fixed before analysis and is reported in full in the Materials and Methods.
Acknowledgements: None.
“I would like to express my sincere gratitude to Ms. Sarah Jacobs, Editorial Coordinator of the IJCCR, for her excellent collaboration and exceptional support throughout the entire process, from article submission and peer review to financial matters and successful publication. Everything went very quickly and smoothly. I would also like to thank the reviewers, whose comments were helpful and contributed to an even better article. I wholeheartedly recommend this deservedly renowned journal to my colleagues for publication.” Best regards, Andreas Schapowal.

Dear Editorial Team, Clinical Medical Reviews and Reports. My experience with the journal was highly positive. The peer-review process was rigorous, constructive, and completed in a timely manner. The reviewers provided valuable comments that helped improve the quality and clarity of our manuscript. The editorial office was professional, responsive, and supportive throughout all stages of the publication process. Communication was clear and efficient, and any questions were addressed promptly. Overall, I found the journal to maintain high scientific standards and an excellent publication workflow. I would be pleased to consider submitting future work to this journal. Best wishes from, Elena Popa.

It was my pleasure to submit my testimonial concerning the Reviewer Board of our Scientific Journal “Brain and Neurological Disorders”. The Reviewers focused on some modifications and their contribution was helpful. The ladies of our Editorial Office were also supported my efforts. It was my honor to have such a co-operation and I am looking forward for more collaboration.

Dear Grace Pierce, Editorial Coordinator of Journal of Clinical Research and Reports, Thank you for the speedy and efficient peer review process. I appreciate the fact that your peer reviewers do not take months to respond like with some other journals. I would also like to thank the editorial office for responding quickly to my questions. It is an excellent journal. I plan to submit more manuscripts in the future. Best wishes from, Robert W. McGee

Dear Grace Pierce, Editorial Coordinator of Journal of Clinical Research and Reports, Working with you and your team on our recent publication in JCRR has been a truly wonderful and enjoyable experience. The responses were prompt, and the reviewers were patient, constructive, and highly professional. One reviewer in particular gave me the feeling that a professor was carefully reading and commenting on my coursework, which was deeply touching. The entire process was straightforward and hassle‑free, with no tedious online forms to complete. I highly recommend this journal. Best wishes from, DR Aibing Rao, Head of R&D

I Appreciate the Opportunity to Share my Experience with the Journal of Clinical Research and Reports. The peer review process was timely and constructive, and the feedback provided helped improve the quality of our manuscript. The editorial office was professional, responsive, and supportive throughout the process, ensuring smooth communication and efficient handling of the submission. Overall, it was a positive experience collaborating with your team.

Dear Mercy Grace, Editorial Coordinator of Obstetrics Gynecology and Reproductive Sciences, We would like to express our gratitude for your help at all stages of publishing and editing the article. The editors of the magazine answer all the necessary questions and help at every stage. We will definitely continue to cooperate and publish other works in the Obstetrics Gynecology and Reproductive Sciences! Best wishes from, Alla Konstantinovna Politova,

Dear Maria Emerson, Editorial Coordinator of International Journal of Clinical Case Reports and Reviews, What distinguishes International Journal of Clinical Case Report and Review is not only the scientific rigor of its publications, but the intellectual climate in which research is evaluated. The submission process is refreshingly free of unnecessary formal barriers and bureaucratic rituals that often complicate academic publishing without adding real value. The peer-review system is demanding yet constructive, guided by genuine scientific dialogue rather than hierarchical or authoritarian attitudes. Reviewers act as collaborators in improving the manuscript, not as gatekeepers imposing arbitrary standards. This journal offers a rare balance: high methodological standards combined with a respectful, transparent, and supportive editorial approach. In an era where publishing can feel more burdensome than research itself, this platform restores the original purpose of peer review — to refine ideas, not to obstruct them Prof. Perlat Kapisyzi, FCCP PULMONOLOGIST AND THORACIC IMAGING.

Dear Reader: We have published several articles in the Auctores Publishing, LLC, journal, Clinical Medical Reviews and Reports in recent years (CMRR). This is an ‘open access’ journal and the following are our observations. From the initial invitation to submit an article, to the final edits of galley proofs, we have found CMRR personnel to be professional, responsive, rapid and thorough. This entire process begins with Catherine Mitchell, Editorial Coordinator. She is simply outstanding, and, I believe, unparalleled in her capacity. I cannot imagine a more responsive and dedicated Editorial Coordinator. As I read the dates and timing of her correspondence with us, it seems that she never sleeps. I hope Auctores Publishing, LLC, appreciates her efforts as much as these authors do. Thank you to Auctores Publishing, LLC, to the Editorial Staff/Board, and to Catherine Mitchell from a grateful author(s).

Dear Maria Emerson, Editorial Coordinator of - Journal of Clinical Research and Reports. ''I am pleased to provide this testimonial following the publication of our recent case report in this journal. The peer review process was rigorous, constructive, thorough, and conducted in a timely manner. The reviewers’ comments were thoughtful, detailed, and highly constructive, contributing substantially to the refinement, clarity, and scientific robustness of our manuscript. The process was conducted with professionalism and academic integrity throughout. The support provided by the editorial office was exemplary. Communication was consistently prompt, clear, and courteous at all stages of the submission and publication process. The editorial team demonstrated a high level of organization and responsiveness, ensuring that all queries were addressed efficiently and that the process remained transparent and well-coordinated. The overall quality of the journal is reflected in its strong editorial standards, commitment to scientific excellence, and dedication to publishing clinically meaningful research. It has been a privilege to publish our work in this journal, and we would welcome the opportunity to contribute further in the future.'' Best wishes from, Dr. Efstratios Trogkanis, Cardiologist.

Dear Grace Pierce, Editorial Coordinator of the journal IJCCR, I had a very positive experience with Auctores - Journal throughout the publication process. The Editorial Team was highly responsive, professional, and supportive at every stage. I would like to extend my sincere thanks to the Editor: Grace Pierce, for her guidance and assistance. The peer-review process was smooth and constructive, helping improve the quality of my work. I would gladly recommend Auctores Journal to fellow researchers and authors. Dr. SABITA SINHA, Medical Oncologist, MD (Electro Homeopathy).

Dear Mayra Duenas, Editorial Coordinator of the journal IJCCR, I write here a little on my experience as an author submitting to the International Journal of Clinical Case Reports and Reviews (IJCCR). This was my first submission to IJCCR and my manuscript was inherently an outsider’s effort. It attempted to broadly identify and then make some sense of life’s under-appreciated mysteries. I initially had responded to a request for possible submissions. I then contacted IJCCR with a tentative topic for a manuscript. They quickly got back with an approval for the submission, but with a particular requirement that it be medically relevant. I then put together a manuscript and submitted it. After the usual back-and-forth over forms and formality, the manuscript was sent off for reviews. Within 2 weeks I got back 4 reviews which were both helpful and also surprising. Surprising in that the topic was somewhat foreign to medical literature. My subsequent updates in response to the reviewer comments went smoothly and in short order I had a series of proofs to evaluate. All in all, the whole publication process seemed outstanding. It was both helpful in terms of the paper’s content and also in terms of its efficient and friendly communications. Thank you all very much. Sincerely, Ted Christopher, Rochester, NY.

International Journal of Clinical Case Reports and Reviews is a high quality journal that has a clear and concise submission process. The peer review process was comprehensive and constructive. Support from the editorial office was excellent, since the administrative staff were responsive. The journal provides a fast and timely publication timeline.

Dear Cecilia Lilly, Editorial Coordinator, Endocrinology and Disorders, Thank you so much for your quick response regarding reviewing and all process till publishing our manuscript entitled: Prevalence of Pre-Diabetes and its Associated Risk Factors Among Nile College Students, Sudan. Best regards, Dr Mamoun Magzoub.

Dear Editorial Team, Clinical Cardiology and Cardiovascular Interventions. I am really grateful for the peers review; their feedback gave me the opportunity to reflect on the message and impact of my work and to ameliorate the article. The editors did a great job in addition by encouraging me to continue with the process of publishing.

Dear Mayra Duenas, Editorial Coordinator of ‘International Journal of Clinical Case Reports and Reviews Herewith I confirm an optimal peer review process and a great support of the editorial office of the present journal
Dear Maria Emerson, Editorial Coordinator of ‘International Journal of Clinical Case Reports and Reviews’, I appreciate the opportunity to publish my article with your journal. The editorial office provided clear communication during the submission and review process, and I found the overall experience professional and constructive. Best regards, Elena Salvatore.

Dear Editorial Team, Journal-Clinical Cardiology and Cardiovascular Interventions, “Publishing my article with Clinical Cardiology and Cardiovascular Interventions has been a highly positive experience. The peer-review process was rigorous yet supportive, offering valuable feedback that strengthened my work. The editorial team demonstrated exceptional professionalism, prompt communication, and a genuine commitment to maintaining the highest scientific standards. I am very pleased with the publication quality and proud to be associated with such a reputable journal.” Warm regards, Dr. Mahmoud Kamal Moustafa Ahmed

Dear Editorial Team, Clinical Cardiology and Cardiovascular Interventions. It was truly a rewarding experience to work with the journal “Clinical Cardiology and Cardiovascular Interventions”. The peer review process was insightful and encouraging, helping us refine our work to a higher standard. The editorial office offered exceptional support with prompt and thoughtful communication. I highly value the journal’s role in promoting scientific advancement and am honored to be part of it. Best regards, Meng-Jou Lee, MD, Department of Anesthesiology, National Taiwan University Hospital.

Dear Maria Emerson, Editorial Coordinator, Journal of Clinical Research and Reports. Thank you for publishing our case report: "Clinical Case of Effective Fetal Stem Cells Treatment in a Patient with Autism Spectrum Disorder" within the "Journal of Clinical Research and Reports" being submitted by the team of EmCell doctors from Kyiv, Ukraine. We much appreciate a professional and transparent peer-review process from Auctores. All research Doctors are so grateful to your Editorial Office and Auctores Publishing support! I amiably wish our article publication maintained a top quality of your International Scientific Journal. My best wishes for a prosperity of the Journal of Clinical Research and Reports. Hope our scientific relationship and cooperation will remain long lasting. Thank you very much indeed. Kind regards, Dr. Andriy Sinelnyk Cell Therapy Center EmCell

I recommend without hesitation submitting relevant papers on medical decision making to the International Journal of Clinical Case Reports and Reviews. I am very grateful to the editorial staff. Maria Emerson was a pleasure to communicate with. The time from submission to publication was an extremely short 3 weeks. The editorial staff submitted the paper to three reviewers. Two of the reviewers commented positively on the value of publishing the paper. The editorial staff quickly recognized the third reviewer’s comments as an unjust attempt to reject the paper. I revised the paper as recommended by the first two reviewers.

Dear Chrystine Mejia, Editorial Coordinator, Journal of Neurodegeneration and Neurorehabilitation. “The peer review process was efficient and constructive, and the editorial office provided excellent communication and support throughout. The journal ensures scientific rigor and high editorial standards, while also offering a smooth and timely publication process. We sincerely appreciate the work of the editorial team in facilitating the dissemination of innovative approaches such as the Bonori Method.” Best regards, Dr. Matteo Bonori.

Dear Maria Emerson, Editorial Coordinator, we have deeply appreciated the professionalism demonstrated by the International Journal of Clinical Case Reports and Reviews. The reviewers have extensive knowledge of our field and have been very efficient and fast in supporting the process. I am really looking forward to further collaboration. Thanks. Best regards, Dr. Claudio Ligresti
Dear Ms. Mayra Duenas, Editorial Coordinator, International Journal of Clinical Case Reports and Reviews. “The International Journal of Clinical Case Reports and Reviews represented the “ideal house” to share with the research community a first experience with the use of the Simeox device for speech rehabilitation. High scientific reputation and attractive website communication were first determinants for the selection of this Journal, and the following submission process exceeded expectations: fast but highly professional peer review, great support by the editorial office, elegant graphic layout. Exactly what a dynamic research team - also composed by allied professionals - needs!" From, Chiara Beccaluva, PT - Italy.

Dear Clarissa Eric, Editorial Coordinator, Journal of Clinical Case Reports and Studies, Auctores Publishing LLC, USA Office: +1-(302)-520-2644. I would like to express my sincere appreciation for the efficient and professional handling of my case report by the ‘Journal of Clinical Case Reports and Studies’. The peer review process was not only fast but also highly constructive—the reviewers’ comments were clear, relevant, and greatly helped me improve the quality and clarity of my manuscript. I also received excellent support from the editorial office throughout the process. Communication was smooth and timely, and I felt well guided at every stage, from submission to publication. The overall quality and rigor of the journal are truly commendable. I am pleased to have published my work with Journal of Clinical Case Reports and Studies, and I look forward to future opportunities for collaboration. Sincerely, Aline Tollet, UCLouvain.

Dear Chrystine Mejia, Editorial Coordinator, Journal of Neurodegeneration and Neurorehabilitation, Auctores Publishing LLC, We would like to thank the editorial team for the smooth and high-quality communication leading up to the publication of our article in the Journal of Neurodegeneration and Neurorehabilitation. The reviewers have extensive knowledge in the field, and their relevant questions helped to add value to our publication. Kind regards, Dr. Ravi Shrivastava.

Dear Clarissa Eric, Editorial Coordinator, Journal of Clinical Case Reports and Studies, I would like to express my deep admiration for the exceptional professionalism demonstrated by your journal. I am thoroughly impressed by the speed of the editorial process, the substantive and insightful reviews, and the meticulous preparation of the manuscript for publication. Additionally, I greatly appreciate the courteous and immediate responses from your editorial office to all my inquiries. Best Regards, Dariusz Ziora

Dear Ashley Rosa, Editorial Coordinator, International Journal of Clinical Case Reports and Reviews, Auctores Publishing LLC. Thank you for publishing our article, Exploring Clozapine's Efficacy in Managing Aggression: A Multiple Single-Case Study in Forensic Psychiatry in the international journal of clinical case reports and reviews. We found the peer review process very professional and efficient. The comments were constructive, and the whole process was efficient. On behalf of the co-authors, I would like to thank you for publishing this article. With regards, Dr. Jelle R. Lettinga.

Dear Jessica Magne, Editorial Coordinator, Clinical Cardiology and Cardiovascular Interventions, Auctores Publishing LLC. The peer review process of the journal of Clinical Cardiology and Cardiovascular Interventions was excellent and fast, as was the support of the editorial office and the quality of the journal. Kind regards Walter F. Riesen Prof. Dr. Dr. h.c. Walter F. Riesen.

Dear Erin Aust, Editorial Coordinator, Journal of General Medicine and Clinical Practice. We are pleased to share our experience with the “Journal of General Medicine and Clinical Practice”, following the successful publication of our article. The peer review process was thorough and constructive, helping to improve the clarity and quality of the manuscript. We are especially thankful to Ms. Erin Aust, the Editorial Coordinator, for her prompt communication and continuous support throughout the process. Her professionalism ensured a smooth and efficient publication experience. The journal upholds high editorial standards, and we highly recommend it to fellow researchers seeking a credible platform for their work. Best wishes By, Dr. Rakhi Mishra.

Dr Hala Al Shaikh This is to acknowledge that the peer review process for the article ’ A Novel Gnrh1 Gene Mutation in Four Omani Male Siblings, Presentation and Management ’ sent to the International Journal of Clinical Case Reports and Reviews was quick and smooth. The editorial office was prompt with easy communication.

Dear Agrippa Hilda, Editorial Coordinator, Journal of Neuroscience and Neurological Surgery. The entire process including article submission, review, revision, and publication was extremely easy. The journal editor was prompt and helpful, and the reviewers contributed to the quality of the paper. Thank you so much! Eric Nussbaum, MD

Dear Ashley Rosa, Editorial Coordinator, International Journal of Clinical Case Reports and Reviews. Many thanks for publishing this manuscript after I lost confidence the editors were most helpful, more than other journals Best wishes from, Susan Anne Smith, PhD. Australian Breastfeeding Association.

Dear Maria Emerson, Editorial Coordinator, International Journal of Clinical Case Reports and Reviews, Auctores Publishing LLC. I am delighted to have published our manuscript, "Acute Colonic Pseudo-Obstruction (ACPO): A rare but serious complication following caesarean section." I want to thank the editorial team, especially Maria Emerson, for their prompt review of the manuscript, quick responses to queries, and overall support. Yours sincerely Dr. Victor Olagundoye.

Dear Jessica Magne, Editorial Coordinator, Clinical Cardiology and Cardiovascular Interventions, Auctores Publishing LLC. I appreciate the journal (JCCI) editorial office support, the entire team leads were always ready to help, not only on technical front but also on thorough process. Also, I should thank dear reviewers’ attention to detail and creative approach to teach me and bring new insights by their comments. Surely, more discussions and introduction of other hemodynamic devices would provide better prevention and management of shock states. Your efforts and dedication in presenting educational materials in this journal are commendable. Best wishes from, Farahnaz Fallahian.

Dear Ashley Rosa, Editorial Coordinator of the journal - Psychology and Mental Health Care. " The process of obtaining publication of my article in the Psychology and Mental Health Journal was positive in all areas. The peer review process resulted in a number of valuable comments, the editorial process was collaborative and timely, and the quality of this journal has been quickly noticed, resulting in alternative journals contacting me to publish with them." Warm regards, Susan Anne Smith, PhD. Australian Breastfeeding Association.

Dear Jessica, and the super professional team of the ‘Clinical Cardiology and Cardiovascular Interventions’ I am sincerely grateful to the coordinated work of the journal team for the no problem with the submission of my manuscript: “Cardiometabolic Disorders in A Pregnant Woman with Severe Preeclampsia on the Background of Morbid Obesity (Case Report).” The review process by 5 experts was fast, and the comments were professional, which made it more specific and academic, and the process of publication and presentation of the article was excellent. I recommend that my colleagues publish articles in this journal, and I am interested in further scientific cooperation. Sincerely and best wishes, Dr. Oleg Golyanovskiy.

To Dear Erin Aust – Editorial Coordinator of Journal of General Medicine and Clinical Practice! I declare that I am absolutely satisfied with your work carried out with great competence in following the manuscript during the various stages from its receipt, during the revision process to the final acceptance for publication. Thank Prof. Elvira Farina

My article, titled 'No Way Out of the Smartphone Epidemic Without Considering the Insights of Brain Research,' has been republished in the International Journal of Clinical Case Reports and Reviews. The review process was seamless and professional, with the editors being both friendly and supportive. I am deeply grateful for their efforts.

We found the peer review process quick and positive in its input. The support from the editorial officer has been very agile, always with the intention of improving the article and taking into account our subsequent corrections.

Dear Jessica Magne, with gratitude for the joint work. Fast process of receiving and processing the submitted scientific materials in “Clinical Cardiology and Cardiovascular Interventions”. High level of competence of the editors with clear and correct recommendations and ideas for enriching the article.

I thank the ‘Journal of Clinical Research and Reports’ for accepting this article for publication. This is a rigorously peer reviewed journal which is on all major global scientific data bases. I note the review process was prompt, thorough and professionally critical. It gave us an insight into a number of important scientific/statistical issues. The review prompted us to review the relevant literature again and look at the limitations of the study. The peer reviewers were open, clear in the instructions and the editorial team was very prompt in their communication. This journal certainly publishes quality research articles. I would recommend the journal for any future publications.

"I am grateful for the opportunity of contributing to [International Journal of Clinical Case Reports and Reviews] and for the rigorous review process that enhances the quality of research published in your esteemed journal. I sincerely appreciate the time and effort of your team who have dedicatedly helped me in improvising changes and modifying my manuscript. The insightful comments and constructive feedback provided have been invaluable in refining and strengthening my work".

To Dear Erin Aust, I would like to express my heartfelt appreciation for the opportunity to have my work published in this esteemed journal. The entire publication process was smooth and well-organized, and I am extremely satisfied with the final result. The Editorial Team demonstrated the utmost professionalism, providing prompt and insightful feedback throughout the review process. Their clear communication and constructive suggestions were invaluable in enhancing my manuscript, and their meticulous attention to detail and dedication to quality are truly commendable. Additionally, the support from the Editorial Office was exceptional. From the initial submission to the final publication, I was guided through every step of the process with great care and professionalism. The team's responsiveness and assistance made the entire experience both easy and stress-free. I am also deeply impressed by the quality and reputation of the journal. It is an honor to have my research featured in such a respected publication, and I am confident that it will make a meaningful contribution to the field.

I would like to express my sincere gratitude for the support and efficiency provided by the editorial office throughout the publication process of my article, “Delayed Vulvar Metastases from Rectal Carcinoma: A Case Report.” I greatly appreciate the assistance and guidance I received from your team, which made the entire process smooth and efficient. The peer review process was thorough and constructive, contributing to the overall quality of the final article. I am very grateful for the high level of professionalism and commitment shown by the editorial staff, and I look forward to maintaining a long-term collaboration with the International Journal of Clinical Case Reports and Reviews.

Dear Agrippa Hilda- Editorial Coordinator of Journal of Neuroscience and Neurological Surgery, "The peer review process was very quick and of high quality, which can also be seen in the articles in the journal. The collaboration with the editorial office was very good."

I would like to offer my testimony in the support. I have received through the peer review process and support the editorial office where they are to support young authors like me, encourage them to publish their work in your esteemed journals, and globalize and share knowledge globally. I really appreciate your journal, peer review, and editorial office.

My experience publishing in International Journal of Clinical Case Reports and Reviews was exceptional. I Come forth to Provide a Testimonial Covering the Peer Review Process and the editorial office for the Professional and Impartial Evaluation of the Manuscript.

My experience publishing in Psychology and Mental Health Care was exceptional. The peer review process was rigorous and constructive, with reviewers providing valuable insights that helped enhance the quality of our work. The editorial team was highly supportive and responsive, making the submission process smooth and efficient. The journal's commitment to high standards and academic rigor makes it a respected platform for quality research. I am grateful for the opportunity to publish in such a reputable journal.

My Testimonial Covering as fellowing: Lin-Show Chin. The peer reviewers process is quick and effective, the supports from editorial office is excellent, the quality of journal is high. I would like to collabroate with Internatioanl journal of Clinical Case Reports and Reviews.

Dealing with The Journal of Neurology and Neurological Surgery was very smooth and comprehensive. The office staff took time to address my needs and the response from editors and the office was prompt and fair. I certainly hope to publish with this journal again.Their professionalism is apparent and more than satisfactory. Susan Weiner

Dear Editorial Coordinator of the Journal of Nutrition and Food Processing! "I would like to thank the Journal of Nutrition and Food Processing for including and publishing my article. The peer review process was very quick, movement and precise. The Editorial Board has done an extremely conscientious job with much help, valuable comments and advices. I find the journal very valuable from a professional point of view, thank you very much for allowing me to be part of it and I would like to participate in the future!”

Dear Monica Gissare, - Editorial Coordinator of Nutrition and Food Processing. ¨My testimony with you is truly professional, with a positive response regarding the follow-up of the article and its review, you took into account my qualities and the importance of the topic¨.

Dear Dr. Jessica Magne, Editorial Coordinator 0f Clinical Cardiology and Cardiovascular Interventions, I hope this message finds you well. I want to express my utmost gratitude for your excellent work and for the dedication and speed in the publication process of my article titled "Navigating Innovation: Qualitative Insights on Using Technology for Health Education in Acute Coronary Syndrome Patients." I am very satisfied with the peer review process, the support from the editorial office, and the quality of the journal. I hope we can maintain our scientific relationship in the long term.

Clinical Cardiology and Cardiovascular Interventions, I would like to express my sincerest gratitude for the trust placed in our team for the publication in your journal. It has been a true pleasure to collaborate with you on this project. I am pleased to inform you that both the peer review process and the attention from the editorial coordination have been excellent. Your team has worked with dedication and professionalism to ensure that your publication meets the highest standards of quality. We are confident that this collaboration will result in mutual success, and we are eager to see the fruits of this shared effort.

The peer reviewers process is quick and effective, the supports from editorial office is excellent, the quality of journal is high. I would like to collabroate with Internatioanl journal of Clinical Case Reports and Reviews journal clinically in the future time.

Clinical Cardiology and Cardiovascular Interventions, we deeply appreciate the interest shown in our work and its publication. It has been a true pleasure to collaborate with you. The peer review process, as well as the support provided by the editorial office, have been exceptional, and the quality of the journal is very high, which was a determining factor in our decision to publish with you.

Clinical Cardiology and Cardiovascular Interventions I testity the covering of the peer review process, support from the editorial office, and quality of the journal.

Dear editorial department: On behalf of our team, I hereby certify the reliability and superiority of the International Journal of Clinical Case Reports and Reviews in the peer review process, editorial support, and journal quality. Firstly, the peer review process of the International Journal of Clinical Case Reports and Reviews is rigorous, fair, transparent, fast, and of high quality. The editorial department invites experts from relevant fields as anonymous reviewers to review all submitted manuscripts. These experts have rich academic backgrounds and experience, and can accurately evaluate the academic quality, originality, and suitability of manuscripts. The editorial department is committed to ensuring the rigor of the peer review process, while also making every effort to ensure a fast review cycle to meet the needs of authors and the academic community. Secondly, the editorial team of the International Journal of Clinical Case Reports and Reviews is composed of a group of senior scholars and professionals with rich experience and professional knowledge in related fields. The editorial department is committed to assisting authors in improving their manuscripts, ensuring their academic accuracy, clarity, and completeness. Editors actively collaborate with authors, providing useful suggestions and feedback to promote the improvement and development of the manuscript. We believe that the support of the editorial department is one of the key factors in ensuring the quality of the journal. Finally, the International Journal of Clinical Case Reports and Reviews is renowned for its high- quality articles and strict academic standards. The editorial department is committed to publishing innovative and academically valuable research results to promote the development and progress of related fields. The International Journal of Clinical Case Reports and Reviews is reasonably priced and ensures excellent service and quality ratio, allowing authors to obtain high-level academic publishing opportunities in an affordable manner. I hereby solemnly declare that the International Journal of Clinical Case Reports and Reviews has a high level of credibility and superiority in terms of peer review process, editorial support, reasonable fees, and journal quality. Sincerely, Rui Tao.

“The peer review process of JPMHC is quick and effective. Authors are benefited by good and professional reviewers with huge experience in the field of psychology and mental health. The support from the editorial office is very professional. People to contact to are friendly and happy to help and assist any query authors might have. Quality of the Journal is scientific and publishes ground-breaking research on mental health that is useful for other professionals in the field”.

Dr.Tania Muñoz, My experience as researcher and author of a review article in The Journal Clinical Cardiology and Interventions has been very enriching and stimulating. The editorial team is excellent, performs its work with absolute responsibility and delivery. They are proactive, dynamic and receptive to all proposals. Supporting at all times the vast universe of authors who choose them as an option for publication. The team of review specialists, members of the editorial board, are brilliant professionals, with remarkable performance in medical research and scientific methodology. Together they form a frontline team that consolidates the JCCI as a magnificent option for the publication and review of high-level medical articles and broad collective interest. I am honored to be able to share my review article and open to receive all your comments.

I am delighted to publish our manuscript entitled "A Perspective on Cocaine Induced Stroke - Its Mechanisms and Management" in the Journal of Neuroscience and Neurological Surgery. The peer review process, support from the editorial office, and quality of the journal are excellent. The manuscripts published are of high quality and of excellent scientific value. I recommend this journal very much to colleagues.

I would like to give my testimony in the support I have got by the peer review process and to support the editorial office where they were of asset to support young author like me to be encouraged to publish their work in your respected journal and globalize and share knowledge across the globe. I really give my great gratitude to your journal and the peer review including the editorial office.

I am very pleased to serve as EBM of the journal, I hope many years of my experience in stem cells can help the journal from one way or another. As we know, stem cells hold great potential for regenerative medicine, which are mostly used to promote the repair response of diseased, dysfunctional or injured tissue using stem cells or their derivatives. I think Stem Cell Research and Therapeutics International is a great platform to publish and share the understanding towards the biology and translational or clinical application of stem cells.

We are grateful for this opportunity to provide a glowing recommendation to the Journal of Psychiatry and Psychotherapy. We found that the editorial team were very supportive, helpful, kept us abreast of timelines and over all very professional in nature. The peer review process was rigorous, efficient and constructive that really enhanced our article submission. The experience with this journal remains one of our best ever and we look forward to providing future submissions in the near future.

I would like to express my gratitude towards you process of article review and submission. I found this to be very fair and expedient. Your follow up has been excellent. I have many publications in national and international journal and your process has been one of the best so far. Keep up the great work.

"We recently published an article entitled “Influence of beta-Cyclodextrins upon the Degradation of Carbofuran Derivatives under Alkaline Conditions" in the Journal of “Pesticides and Biofertilizers” to show that the cyclodextrins protect the carbamates increasing their half-life time in the presence of basic conditions This will be very helpful to understand carbofuran behaviour in the analytical, agro-environmental and food areas. We greatly appreciated the interaction with the editor and the editorial team; we were particularly well accompanied during the course of the revision process, since all various steps towards publication were short and without delay".

I am very glad to say that the peer review process is very successful and fast and support from the Editorial Office. Therefore, I would like to continue our scientific relationship for a long time. And I especially thank you for your kindly attention towards my article. Have a good day!

Dear Erica Kelsey, Editorial Coordinator of Cancer Research and Cellular Therapeutics Our team is very satisfied with the processing of our paper by your journal. That was fast, efficient, rigorous, but without unnecessary complications. We appreciated the very short time between the submission of the paper and its publication on line on your site.

Thank you very much for publishing my Research Article titled “Comparing Treatment Outcome Of Allergic Rhinitis Patients After Using Fluticasone Nasal Spray And Nasal Douching" in the Journal of Clinical Otorhinolaryngology. As Medical Professionals we are immensely benefited from study of various informative Articles and Papers published in this high quality Journal. I look forward to enriching my knowledge by regular study of the Journal and contribute my future work in the field of ENT through the Journal for use by the medical fraternity. The support from the Editorial office was excellent and very prompt. I also welcome the comments received from the readers of my Research Article.

International Journal of Clinical Case Reports and Reviews. I strongly recommend to consider submitting your work to this high-quality journal. The support and availability of the Editorial staff is outstanding and the review process was both efficient and rigorous.

Dear Agrippa Hilda, Journal of Neuroscience and Neurological Surgery, Editorial Coordinator, I trust this message finds you well. I want to extend my appreciation for considering my article for publication in your esteemed journal. I am pleased to provide a testimonial regarding the peer review process and the support received from your editorial office. The peer review process for my paper was carried out in a highly professional and thorough manner. The feedback and comments provided by the authors were constructive and very useful in improving the quality of the manuscript. This rigorous assessment process undoubtedly contributes to the high standards maintained by your journal.

As an author who has recently published in the journal "Brain and Neurological Disorders". I am delighted to provide a testimonial on the peer review process, editorial office support, and the overall quality of the journal. The peer review process at Brain and Neurological Disorders is rigorous and meticulous, ensuring that only high-quality, evidence-based research is published. The reviewers are experts in their fields, and their comments and suggestions were constructive and helped improve the quality of my manuscript. The review process was timely and efficient, with clear communication from the editorial office at each stage. The support from the editorial office was exceptional throughout the entire process. The editorial staff was responsive, professional, and always willing to help. They provided valuable guidance on formatting, structure, and ethical considerations, making the submission process seamless. Moreover, they kept me informed about the status of my manuscript and provided timely updates, which made the process less stressful. The journal Brain and Neurological Disorders is of the highest quality, with a strong focus on publishing cutting-edge research in the field of neurology. The articles published in this journal are well-researched, rigorously peer-reviewed, and written by experts in the field. The journal maintains high standards, ensuring that readers are provided with the most up-to-date and reliable information on brain and neurological disorders. In conclusion, I had a wonderful experience publishing in Brain and Neurological Disorders. The peer review process was thorough, the editorial office provided exceptional support, and the journal's quality is second to none. I would highly recommend this journal to any researcher working in the field of neurology and brain disorders.

Dear Hao Jiang, to Journal of Nutrition and Food Processing We greatly appreciate the efficient, professional and rapid processing of our paper by your team. If there is anything else we should do, please do not hesitate to let us know. On behalf of my co-authors, we would like to express our great appreciation to editor and reviewers.

This is an acknowledgment for peer reviewers, editorial board of Journal of Clinical Research and Reports. They show a lot of consideration for us as publishers for our research article “Evaluation of the different factors associated with side effects of COVID-19 vaccination on medical students, Mutah university, Al-Karak, Jordan”, in a very professional and easy way. This journal is one of outstanding medical journal.

Dr. Bernard Terkimbi Utoo, I am happy to publish my scientific work in Journal of Women Health Care and Issues (JWHCI). The manuscript submission was seamless and peer review process was top notch. I was amazed that 4 reviewers worked on the manuscript which made it a highly technical, standard and excellent quality paper. I appreciate the format and consideration for the APC as well as the speed of publication. It is my pleasure to continue with this scientific relationship with the esteem JWHCI.

Testimony of Journal of Clinical Otorhinolaryngology: work with your Reviews has been a educational and constructive experience. The editorial office were very helpful and supportive. It was a pleasure to contribute to your Journal.

Thank you most sincerely, with regard to the support you have given in relation to the reviewing process and the processing of my article entitled "Large Cell Neuroendocrine Carcinoma of The Prostate Gland: A Review and Update" for publication in your esteemed Journal, Journal of Cancer Research and Cellular Therapeutics". The editorial team has been very supportive.

Dr. Katarzyna Byczkowska My testimonial covering: "The peer review process is quick and effective. The support from the editorial office is very professional and friendly. Quality of the Clinical Cardiology and Cardiovascular Interventions is scientific and publishes ground-breaking research on cardiology that is useful for other professionals in the field.
Journal of Neuroscience and Neurological Surgery. I had the experience of publishing a research article recently. The whole process was simple from submission to publication. The reviewers made specific and valuable recommendations and corrections that improved the quality of my publication. I strongly recommend this Journal.

The peer-review process which consisted high quality queries on the paper. I did answer six reviewers’ questions and comments before the paper was accepted. The support from the editorial office is excellent.

We would like to thank the Journal of Thoracic Disease and Cardiothoracic Surgery because of the services they provided us for our articles. The peer-review process was done in a very excellent time manner, and the opinions of the reviewers helped us to improve our manuscript further. The editorial office had an outstanding correspondence with us and guided us in many ways. During a hard time of the pandemic that is affecting every one of us tremendously, the editorial office helped us make everything easier for publishing scientific work. Hope for a more scientific relationship with your Journal.

Journal of Clinical Research and Reports I would be very delighted to submit my testimonial regarding the reviewer board and the editorial office. The reviewer board were accurate and helpful regarding any modifications for my manuscript. And the editorial office were very helpful and supportive in contacting and monitoring with any update and offering help. It was my pleasure to contribute with your promising Journal and I am looking forward for more collaboration.

Journal of Women Health Care and Issues By the present mail, I want to say thank to you and tour colleagues for facilitating my published article. Specially thank you for the peer review process, support from the editorial office. I appreciate positively the quality of your journal.

Journal of Clinical Cardiology and Cardiovascular Intervention The submission and review process was adequate. However I think that the publication total value should have been enlightened in early fases. Thank you for all.

Clearly Auctoresonline and particularly Psychology and Mental Health Care Journal is dedicated to improving health care services for individuals and populations. The editorial boards' ability to efficiently recognize and share the global importance of health literacy with a variety of stakeholders. Auctoresonline publishing platform can be used to facilitate of optimal client-based services and should be added to health care professionals' repertoire of evidence-based health care resources.
